
 E-submission

Search
- Page Path
- HOME > Search
Original Articles
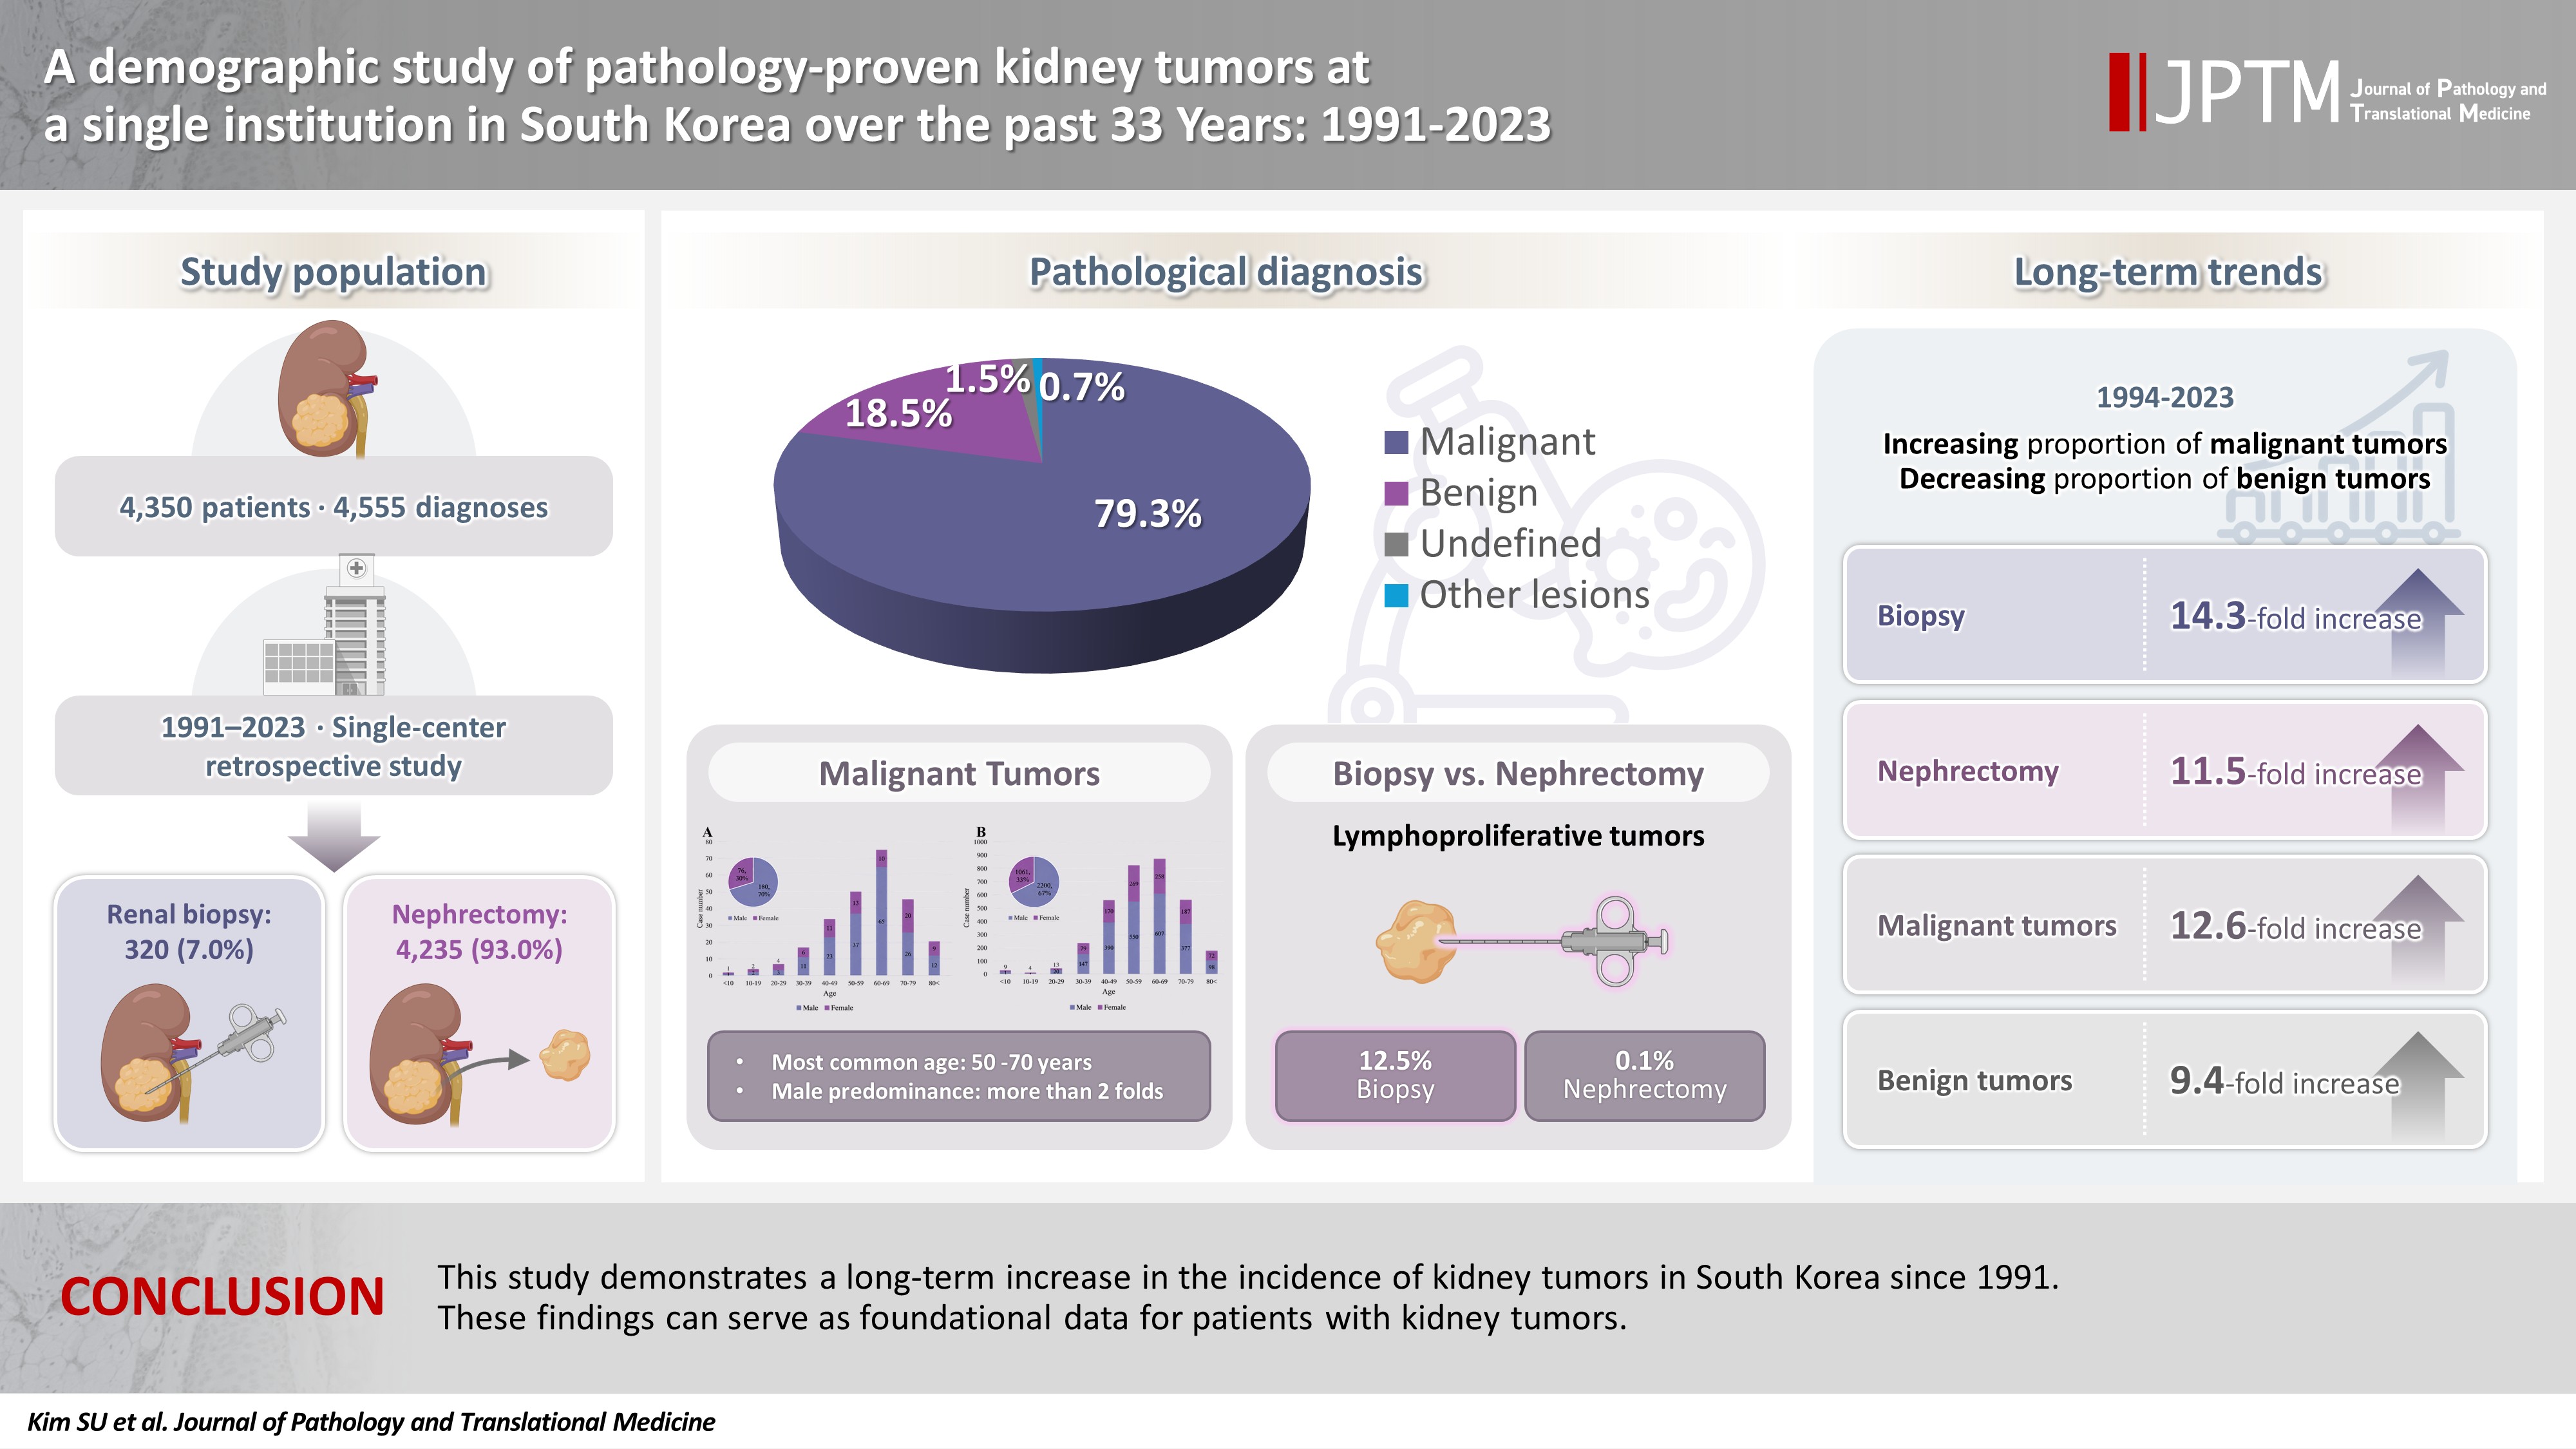
- A demographic study of pathology-proven kidney tumors at a single institution in South Korea over the past 33 years: 1991–2023
- Seon Ung Kim, Hyejin Noh, Jiyeon Kim, Yeong Jin Choi
- J Pathol Transl Med. 2026;60(6):657-669. Published online November 13, 2026
- DOI: https://doi.org/10.4132/jptm.2026.10.19
- 586 View
- 5 Download
-
 Abstract
 PDF
- Background
While the incidence of kidney tumors is increasing, long-term demographic analyses based on pathological diagnoses remain insufficient. This study aimed to investigate demographic changes regarding pathology-proven kidney tumors over the past 33 years. Methods: We retrospectively analyzed 4,555 cases from 4,350 patients who underwent renal biopsy or nephrectomy for suspected kidney tumors at Seoul St. Mary’s Hospital from 1991 to 2023. Results: The average age was 58 years, and the male-to-female ratio was 1.7:1. Among 4,555 cases, 7.0% were biopsies and 93.0% were nephrectomies. Tumors were classified into four diagnostic categories: malignant (79.3%), benign (18.5%), undefined (1.5%), and other lesions (0.7%). Over 33 years, biopsies increased 14.3-fold and nephrectomies 11.5-fold, while malignant tumors increased 12.6-fold and benign tumors 9.4-fold. Over time, the proportion of malignant tumors increased (p < .001), while benign tumors decreased (p < .001). As age increased, the proportion of malignant tumors increased (p = .013), while benign tumors showed a decreasing trend (p = .070). Malignant tumors showed a male predominance, while benign tumors showed a female predominance. The frequency of malignant tumors was similar at approximately 80% in biopsy and nephrectomy. However, benign tumors were more common in nephrectomy (19.1%) than in biopsy (10.9%) (p < .001), and unclassified tumors (4.1%) were more common in biopsies (p < .001). Renal cell carcinoma was most common (61.5% of total cases, 77.6% of malignant tumors). Lymphoproliferative tumors were diagnosed more frequently by biopsy (12.5%) than nephrectomy (0.1%) (p < .001). Conclusions: This study demonstrates a long-term increase in the incidence of renal tumors in South Korea. These findings can serve as foundational data for patients with kidney tumors.
- Utility of LymphoTrack for clonality testing in formalinfixed, paraffin-embedded tissue: integrated panel- and specimen-level comparison with fragment analysis
- Ki-Chang Lee, Hyun-A Kim, Jiwon Koh, Jeong Mo Bae, Cheol Lee, Seung Geun Song, Yoon Kyung Jeon
- Received September 2, 2026 Accepted October 2, 2026 Published online November 13, 2026
- DOI: https://doi.org/10.4132/jptm.2026.10.02 [Epub ahead of print]
- 306 View
- 5 Download
-
Abstract
PDF
 Supplementary Material
- Background
Next-generation sequencing–based clonality assays provide sequence-level resolution but remain vulnerable to panel-specific failure in formalin-fixed, paraffin-embedded (FFPE) tissue. We evaluated LymphoTrack performance and integrated multi-panel interpretation. Methods: Seventeen FFPE specimens from 16 patients underwent 51 immunoglobulin heavy-chain (IGH) and 12 T-cell receptor (TCR) panel runs. Results were classified as Positive, Negative, or Fail and compared with lineage-level fragment-analysis interpretations. Panels targeting each lineage were integrated into specimen-level interpretations. Quality-control metrics associated with panel failure were explored. Results: Among 51 IGH panel runs, 37 (72.5%) were concordant, four (7.8%) discordant, and 10 (19.6%) Fail; all Fail results occurred in FR1 or FR2. IGH specimen-level agreement was 16/17 (94.1%; 95% confidence interval [CI], 73.0% to 99.0%). LymphoTrack classified four IGH specimens as monoclonal and 13 as polyclonal, including six based on incomplete panel coverage. One such specimen (FR1/FR2 Fail and FR3 Negative) was discordant with monoclonal fragment analysis. TCR specimen-level agreement was 5/6 (83.3%; 95% CI, 43.6% to 97.0%). In the discordant TCR specimen, T-cell receptor gamma (TRG) fragment analysis was oligoclonal, whereas both LymphoTrack TRG and T-cell receptor beta were Positive. A post–polymerase chain reaction library concentration threshold of ≤4.5 ng/μL identified all Fail panels but had limited specificity (58.5%) and precision (31.3%). Conclusions: LymphoTrack showed high specimen-level agreement with fragment analysis despite panel-specific technical vulnerability in FFPE tissue. Partial panel failure had asymmetric implications: a Positive panel preserved a monoclonal interpretation, whereas polyclonal results with incomplete panel coverage remained vulnerable to discordance. Reporting incomplete panel coverage may help communicate this limitation.
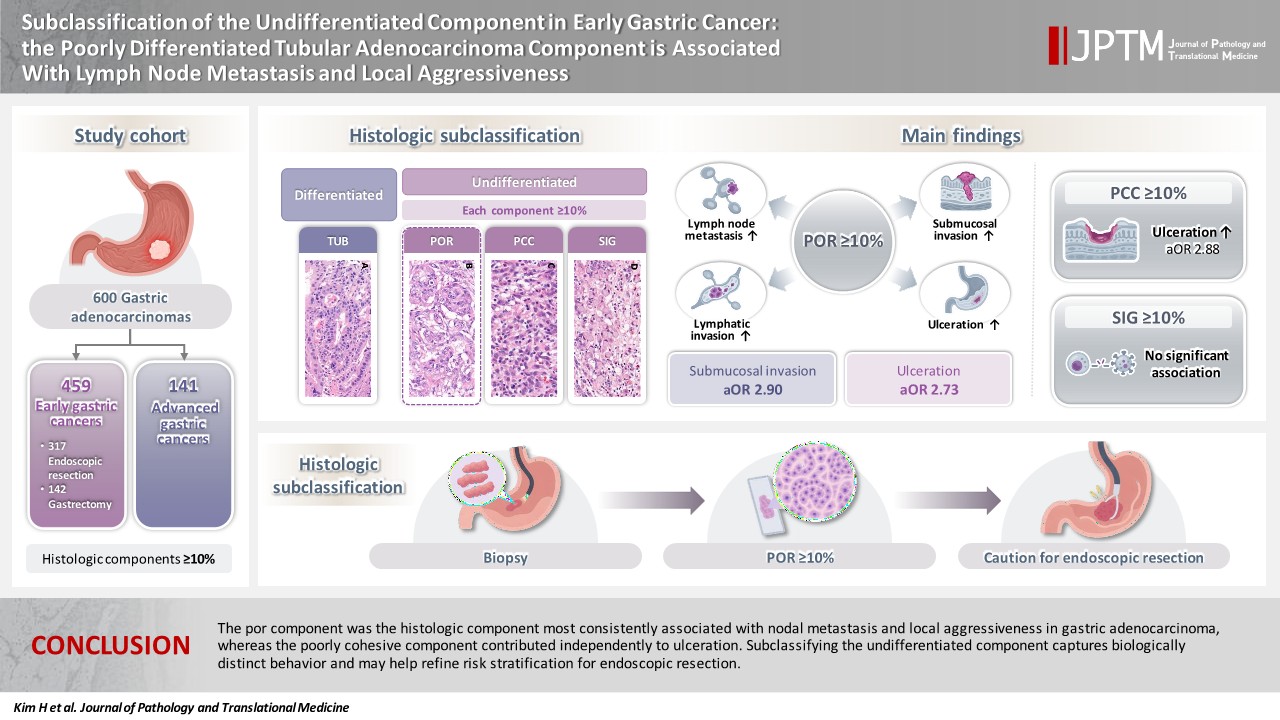
- Subclassification of the undifferentiated component in early gastric cancer: the poorly differentiated tubular adenocarcinoma component is associated with lymph node metastasis and local aggressiveness
- Heesoo Kim, Baek-hui Kim
- J Pathol Transl Med. 2026;60(6):646-656. Published online November 13, 2026
- DOI: https://doi.org/10.4132/jptm.2026.09.15
- 644 View
- 12 Download
-
Abstract
PDFSupplementary Material
- Background
Gastric adenocarcinoma is histologically heterogeneous, and the undifferentiated category encompasses tubular adenocarcinoma, poorly differentiated (por), poorly cohesive carcinoma (pcc), and signet ring cell carcinoma (sig). These components are often treated as a single entity, and which one drives the aggressive behavior of mixed-type tumors remains unclear. We subclassified the undifferentiated component and examined the association of each histologic component with adverse pathologic features. Methods: We retrospectively analyzed 600 gastric adenocarcinomas (459 early, 141 advanced). Each histologic component (tub [tubular adenocarcinoma, well to moderately differentiated], por, pcc, sig) was assessed separately in the mucosal and invasive portions and dichotomized at 10%. Associations with lymph node metastasis (LNM), submucosal invasion, lymphatic invasion, and ulceration were evaluated by univariate testing and multivariable logistic regression. Results: In early gastric cancer, por ≥10% was associated with LNM (p = .006) and lymphatic invasion (p < .001), and was an independent risk factor for submucosal invasion (adjusted odds ratio [OR], 2.90; 95% confidence interval [CI], 1.80 to 4.68; p < .001) and ulceration (adjusted OR, 2.73; 95% CI, 1.40 to 5.34; p = .003). By contrast, pcc ≥10% was independently associated only with ulceration (adjusted OR, 2.88; 95% CI, 1.25 to 6.65; p = .013), and sig showed no association with any adverse feature (all p > .05). Findings in the mucosal component paralleled those in the whole tumor. No histologic component was associated with survival. Conclusions: The por component was the histologic component most consistently associated with nodal metastasis and local aggressiveness in gastric adenocarcinoma, whereas the poorly cohesive component contributed independently to ulceration. Subclassifying the undifferentiated component captures biologically distinct behavior and may help refine risk stratification for endoscopic resection.
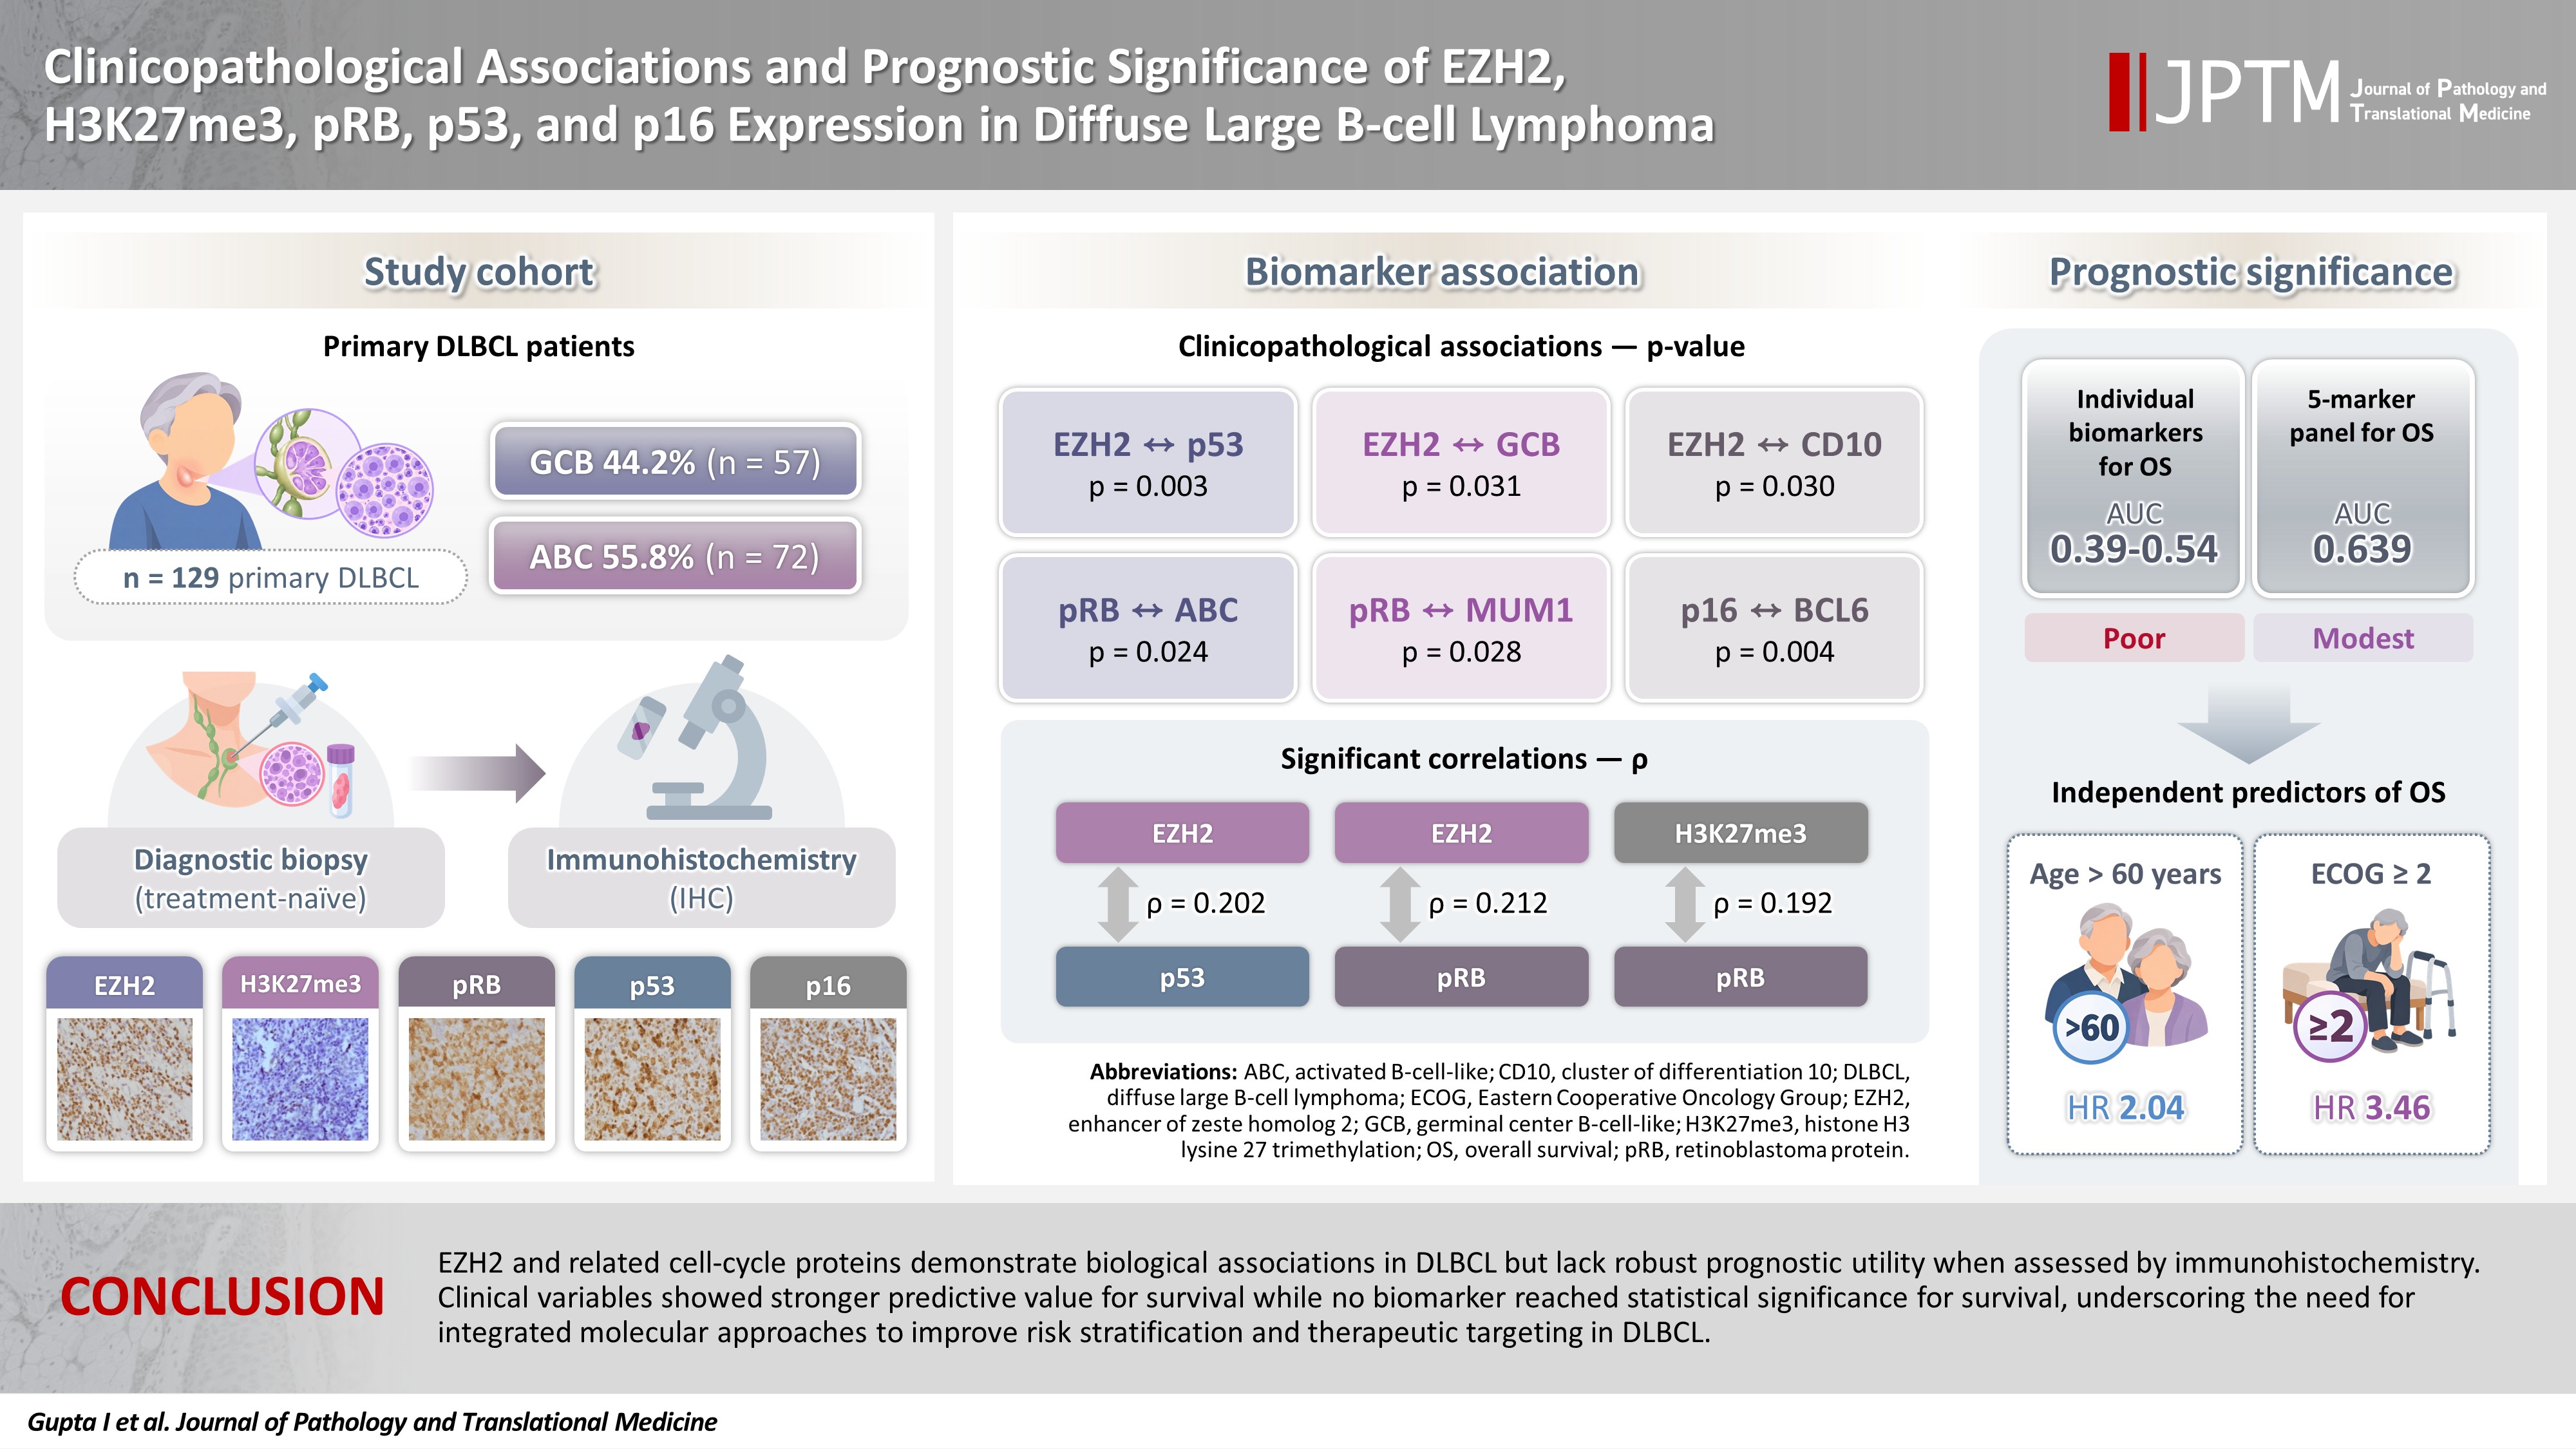
- Clinicopathological associations and prognostic significance of EZH2, H3K27me3, pRB, p53, and p16 expression in diffuse large B-cell lymphoma
- Ishan Gupta, Surabhi Jain, Moien Rasheed Lone, Ajay Gogia, Chandan Krushna Das, Mehar Chand Sharma, Ashish Datt Upadhyay, Saumyaranjan Mallick
- J Pathol Transl Med. 2026;60(6):635-645. Published online November 13, 2026
- DOI: https://doi.org/10.4132/jptm.2026.09.14
- 577 View
- 9 Download
-
Abstract
PDFSupplementary Material
- Background
Diffuse large B-cell lymphoma (DLBCL) is characterized by pronounced heterogeneity in its morphological and biological attributes, with emerging evidence highlighting the pivotal role of epigenomic alterations in its pathogenesis. This study aimed to investigate the relationship between EZH2 expression and cell-cycle regulatory proteins, focusing on their prognostic implications. Methods: This retrospective study included 131 patients with nodal primary DLBCL, who were categorized according to the Hans algorithm and additional immunohistochemistry was performed for selected epigenetic (EZH2 and H3K27me3) and cell-cycle regulatory markers (phosphorylated retinoblastoma [pRB], p16 and p53). Receiver operating characteristic (ROC) curve analysis and Cox regression models were applied to assess prognostic utility. Appropriate statistical analysis was performed. Results: EZH2 was expressed in 59.5% of cases and significantly associated with p53 (p = .003), germinal center B-cell-like (GCB) subtype (p = .031), and CD10 positivity (p = .030). pRB positivity was more frequent in the activated B-cell-like subtype (82.5% vs. 64.3%, p = .024) and was associated with MUM1 (p = .028), while p16 expression was linked to BCL6 (p = .004). ROC analyses demonstrated poor discriminatory ability for overall survival (area under the curve, 0.39 to 0.54), with no clinically actionable cutoffs identified. Stepwise Cox regression identified age >60 years (hazard ratio [HR], 2.04; p = .042) and Eastern Cooperative Oncology Group ≥ 2 (HR, 3.46; p = .001) as independent predictors of overall survival. For progression-free survival, no biomarker reached statistical significance. Conclusions: EZH2 and related cell-cycle proteins demonstrate biological associations in DLBCL but lack robust prognostic utility when assessed by immunohistochemistry. Clinical variables showed stronger predictive value for survival, while no biomarker reached statistical significance for survival, underscoring the need for integrated molecular approaches to improve risk stratification and therapeutic targeting in DLBCL.
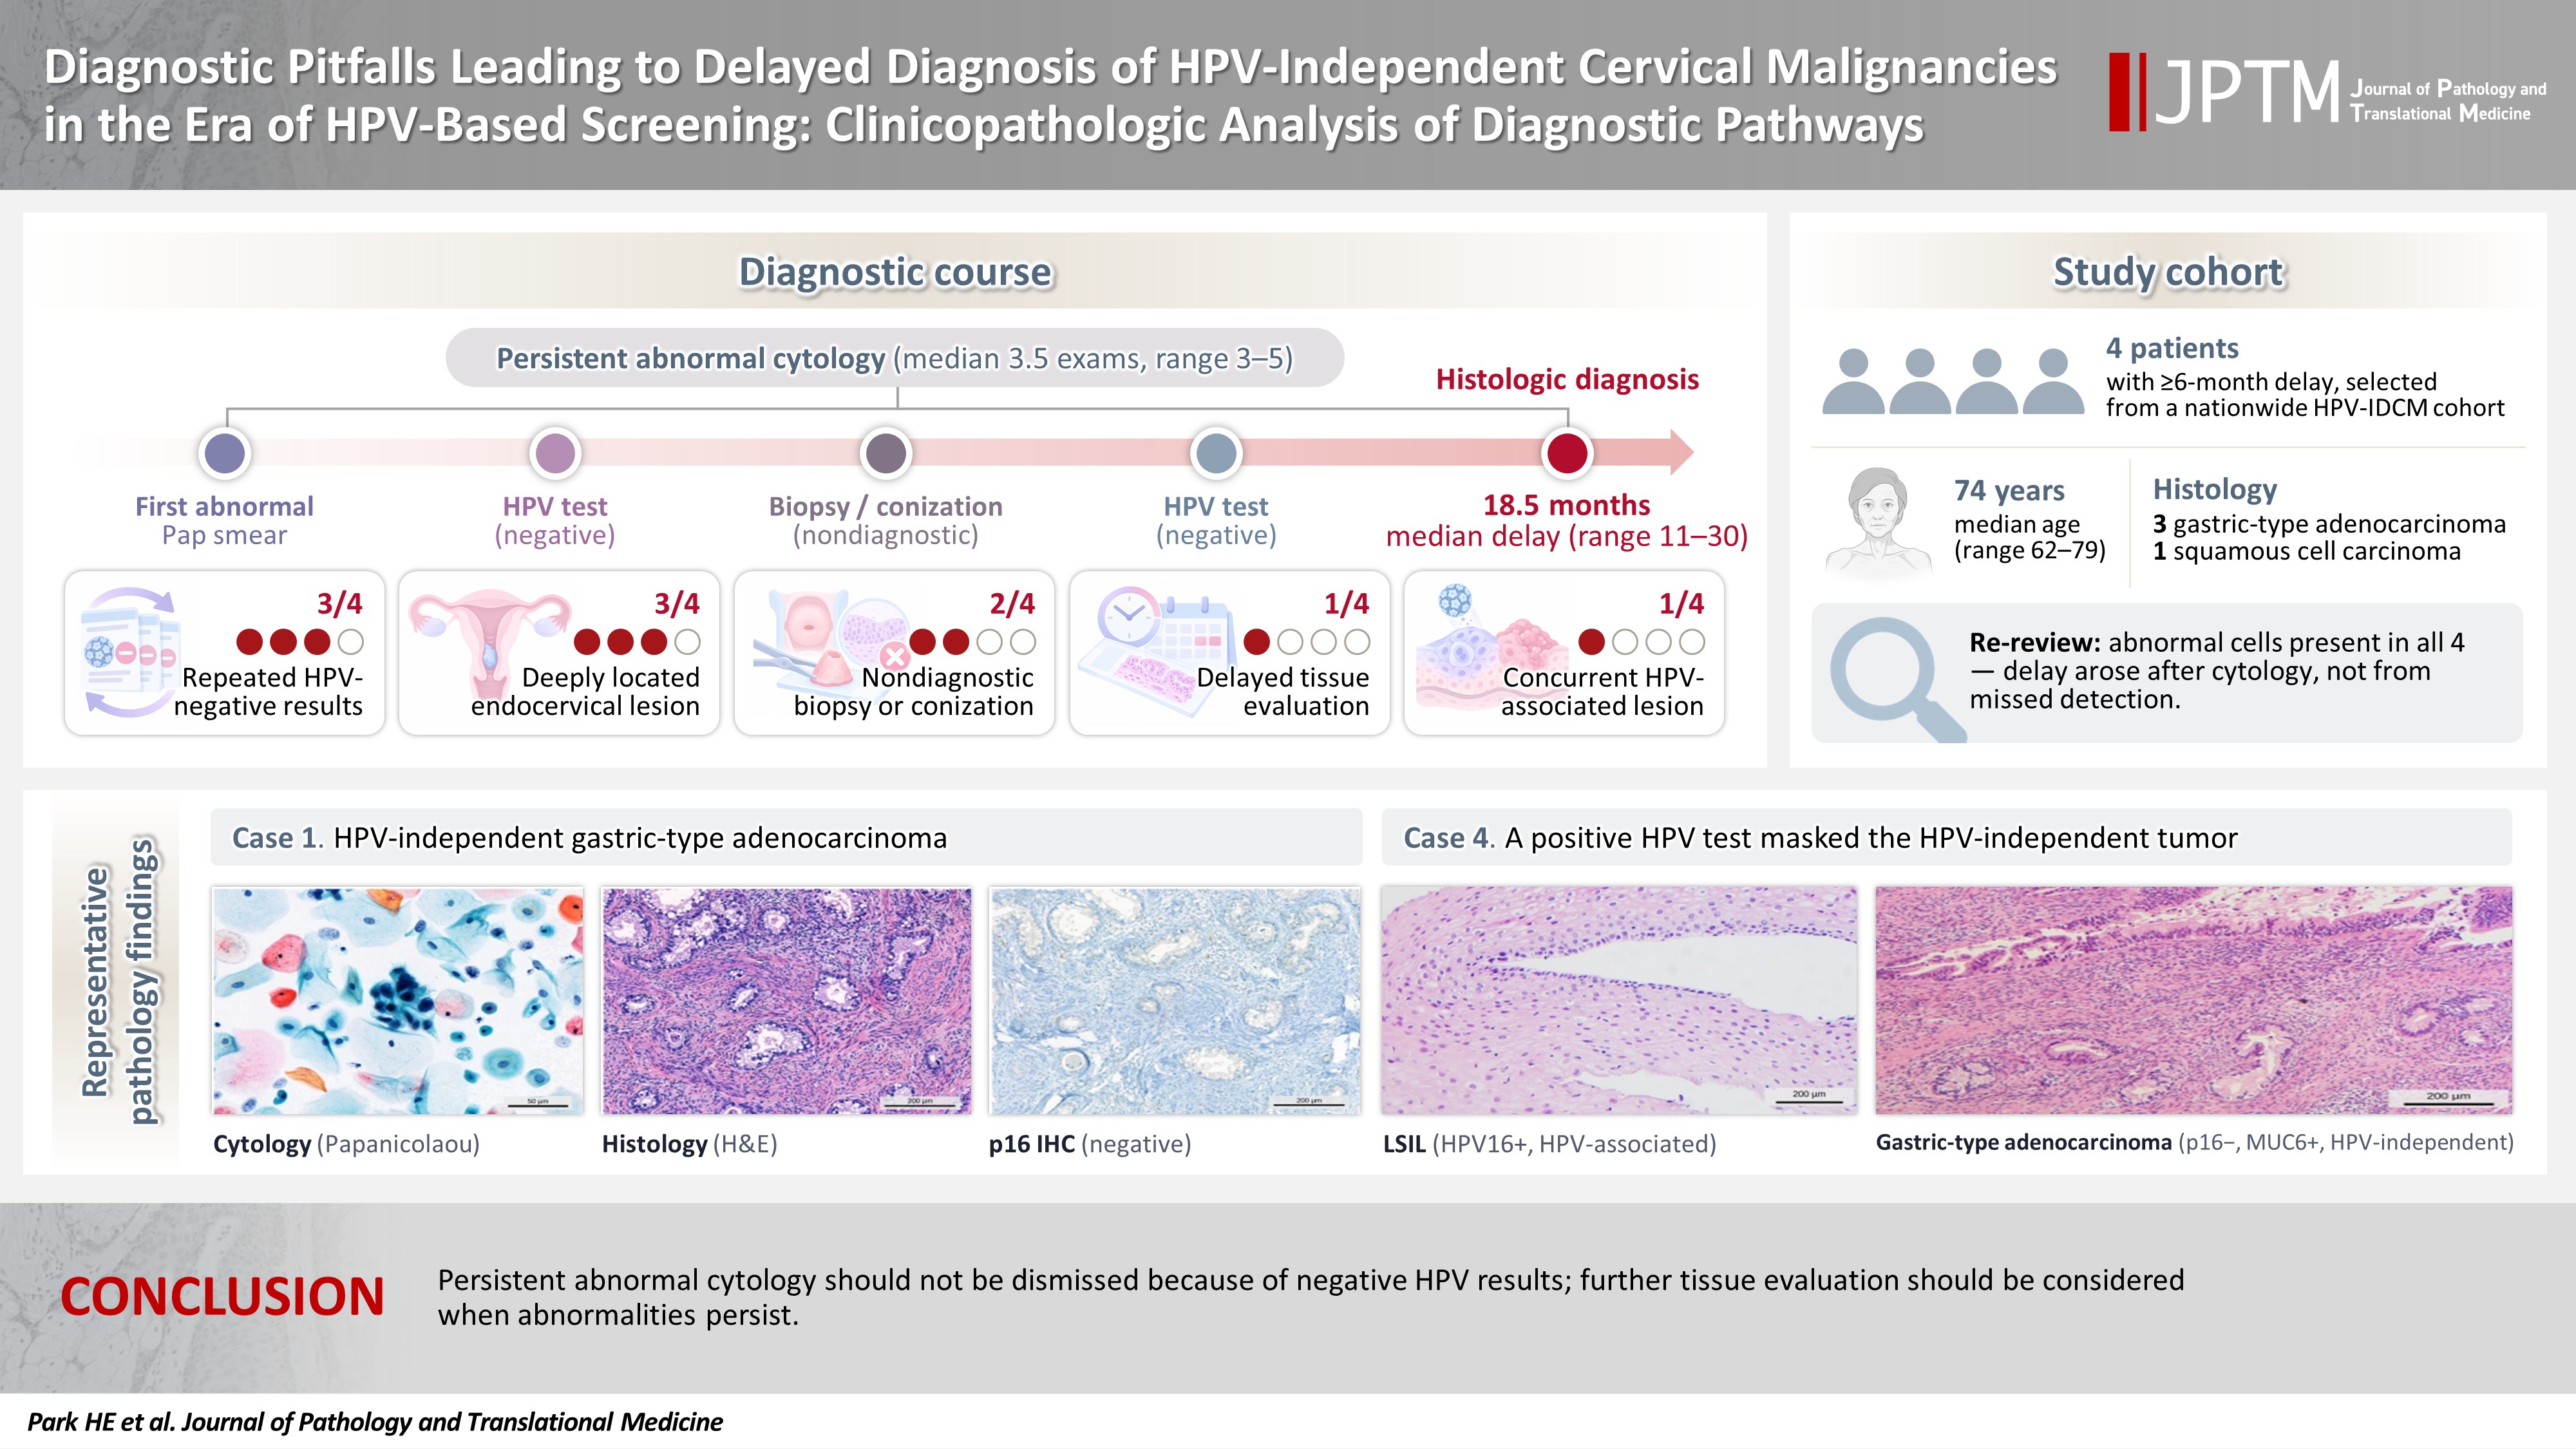
- Diagnostic pitfalls leading to delayed diagnosis of human papillomavirus (HPV)–independent cervical malignancies in the era of HPV-based screening: clinicopathologic analysis of diagnostic pathways
- Hye Eun Park, Hye-Ra Jung, Hyun-Jung Kim
- J Pathol Transl Med. 2026;60(6):670-679. Published online November 13, 2026
- DOI: https://doi.org/10.4132/jptm.2026.08.26
- 555 View
- 7 Download
-
Abstract
PDF
- Background
Human papillomavirus (HPV)–independent cervical malignancies (HPV-IDCM) are a rare but clinically important subset that may escape detection by HPV-based screening. This study investigated diagnostic pitfalls contributing to delayed HPV-IDCM diagnosis and assessed the role of cervical cytology in the diagnostic pathway. Methods: This multicenter retrospective case series was conducted as a policy research project of the Korean Society for Cytopathology. Patients with HPV-IDCM and repeated abnormal cytologic findings before definitive histologic diagnosis were identified. Clinical, cytologic, histologic, and HPV test results were reviewed to identify factors associated with diagnostic delay. Results: Four patients were included, with a median age of 74 years (range, 62 to 79 years). Histologic diagnoses comprised three HPV-independent gastric-type adenocarcinomas and one HPV-independent squamous cell carcinoma. The median interval from the first abnormal cytologic finding to definitive diagnosis was 18.5 months (range, 11 to 30 months). Before diagnosis, all patients underwent a median of 3.5 cytologic examinations (range, 3 to 5). Associated factors included repeatedly negative HPV test results (3/4), nondiagnostic biopsy or conization (2/4), delayed tissue evaluation despite persistent cytologic abnormalities (1/4), deeply located endocervical lesions (3/4), and a concurrent HPV-associated squamous lesion (1/4). Re-review identified atypical or malignant cells in all cases, indicating that the delay did not result from failure of cytologic detection. Conclusions: HPV-IDCM remain vulnerable to delayed diagnosis in the era of HPV-based screening. Persistent abnormal cytologic findings should not be dismissed solely because HPV test results are negative. Careful correlation of cytologic, clinical, and histologic findings remains essential for timely HPV-IDCM detection.
- Prognostic value of PD-L1 combined positive score in colorectal adenocarcinoma
- Thi Thanh Xuan Le, Van Chu Nguyen, Thi Minh Hanh Ngo, Thi Hue Le, Minh Son Le, Huu Song Le, Xuan Hoan Nghiem
- J Pathol Transl Med. 2026;60(6):611-624. Published online November 13, 2026
- DOI: https://doi.org/10.4132/jptm.2026.08.24
- 707 View
- 13 Download
-
Abstract
PDFSupplementary Material
- Background
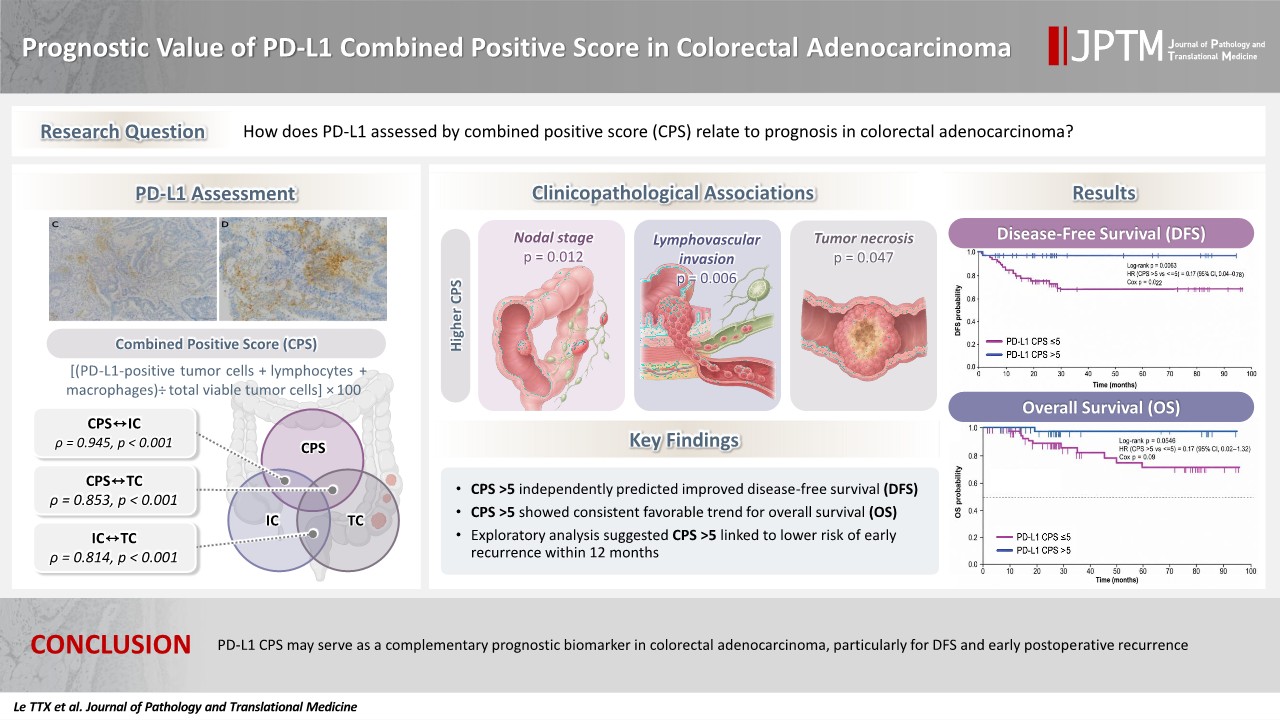
The prognostic significance of programmed cell death ligand 1 (PD-L1) in colorectal adenocarcinoma remains unclear. We evaluated the clinicopathological and prognostic relevance of the PD-L1 combined positive score (CPS). Methods: This single-center retrospective cohort included 124 patients with histopathologically confirmed colorectal adenocarcinoma; PD-L1 was assessed by CPS. Disease-free survival (DFS) and overall survival (OS) were evaluated using Kaplan-Meier methods and parsimonious Cox regression, and early recurrence within 12 months of curative-intent treatment with a truncated Cox model. Results: Higher CPS was significantly associated with nodal stage (p = .012), lymphovascular invasion (p = .006), and tumor necrosis (p = .047). CPS correlated very strongly with immune-cell PD-L1 (rho = 0.945, p < .001) and strongly with tumor-cell PD-L1 (rho = 0.853, p < .001). CPS >5 remained associated with favorable DFS in a prespecified parsimonious multivariable model (adjusted hazard ratio [HR], 0.17; 95% confidence interval [CI], 0.04 to 0.75; p = .019). No PD-L1 metric was significantly associated with OS; however, CPS showed a numerically favorable but non-significant trend (adjusted HR, 0.17; 95% CI, 0.02 to 1.30; p = .088). In the exploratory early recurrence analysis, CPS >5 was associated with a lower risk of early recurrence in a model adjusted only for nodal stage (adjusted HR, 0.21; 95% CI, 0.05 to 0.94; p = .042). Conclusions: PD-L1 CPS may serve as a complementary, hypothesis-generating prognostic marker in colorectal adenocarcinoma, particularly for disease-free survival. However, the lack of mismatch repair (MMR)/microsatellite instability (MSI) data prevents definitive conclusions regarding an MMR/MSI-independent prognostic effect. Further validation in larger, prospectively collected, multicenter cohorts with comprehensive molecular annotation is required.
Case Study
- Intracranial malignant peripheral nerve sheath tumor with myxoid morphology evolving across recurrences: a case report
- Frantisek Vana, Petra Pokorna, Petr Pospisil, Zdenek Mackerle, Marketa Hermanova, Iva Staniczkova Zambo, Martin Barak, Robin Jugas, Radim Jancalek, Ondrej Slaby, Michal Hendrych
- J Pathol Transl Med. 2026;60(6):718-725. Published online November 11, 2026
- DOI: https://doi.org/10.4132/jptm.2026.09.17
- 545 View
- 13 Download
-
Abstract
PDF
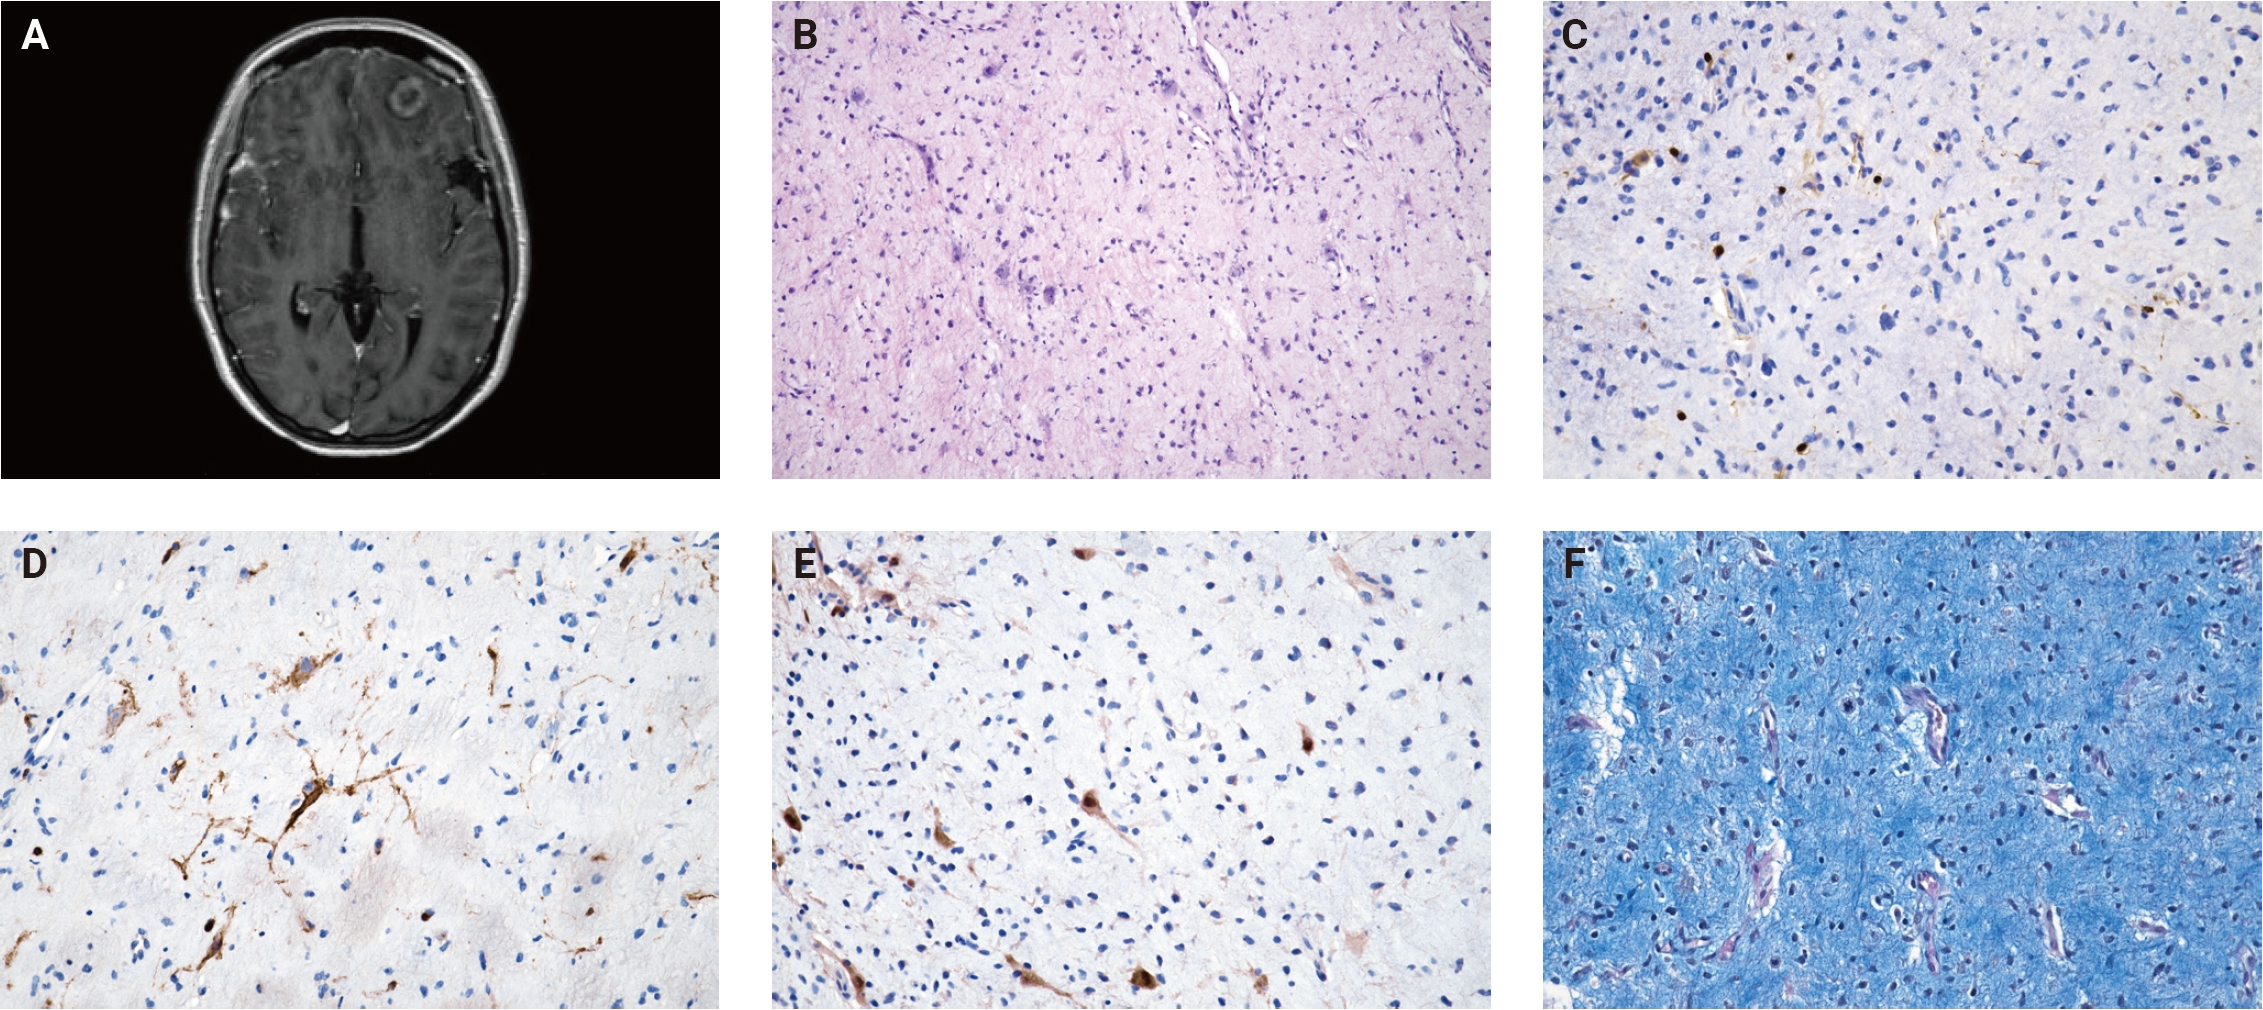
- A malignant peripheral nerve sheath tumor (MPNST) is a rare, aggressive spindle-cell sarcoma that exceptionally occurs intracranially. Herein, we report a case of intracranial spindle-cell neoplasm with abundant myxoid stroma. The immunophenotype of the primary tumor did not align with any known peripheral nerve sheath tumor and the lesion did not correspond to any methylation category defined by the Heidelberg classifier with a sufficiently high classification score, although MPNST was the highest-scoring category. Over the course of repeated recurrences, the tumor acquired increased cellularity, mitotic activity and loss of H3K27me3 expression. Subsequent methylation profiling supported a diagnosis of MPNST. The tumor harbored a gain-of-function variant in NRAS p.Gly13Arg and TP53 p.Arg273Cys from the initial tumor onwards, consistent with previous reports describing activation of Ras/mitogen-activated protein kinase as an early event in MPNST tumorigenesis. These findings illustrate the diagnostic complexity of rare intracranial sarcomas with myxoid morphology and suggest that some may represent early MPNST.
Original Articles
- Concordance of flow cytometric E6/E7 mRNA detection with human papillomavirus DNA testing and cervical cytology in a cervical cancer screening cohort
- Dat Quoc Ngo, Trang Kieu Ha, Mi Ngoc Thi Tran, Anh Mai Thi Nguyen, Truong Nhat Trinh, Thien Thanh Ly, Linh Ngoc Khanh Nguyen, Thu Dang Anh Phan
- J Pathol Transl Med. 2026;60(6):680-686. Published online November 10, 2026
- DOI: https://doi.org/10.4132/jptm.2026.09.09
- 665 View
- 16 Download
-
Abstract
PDF
- Background
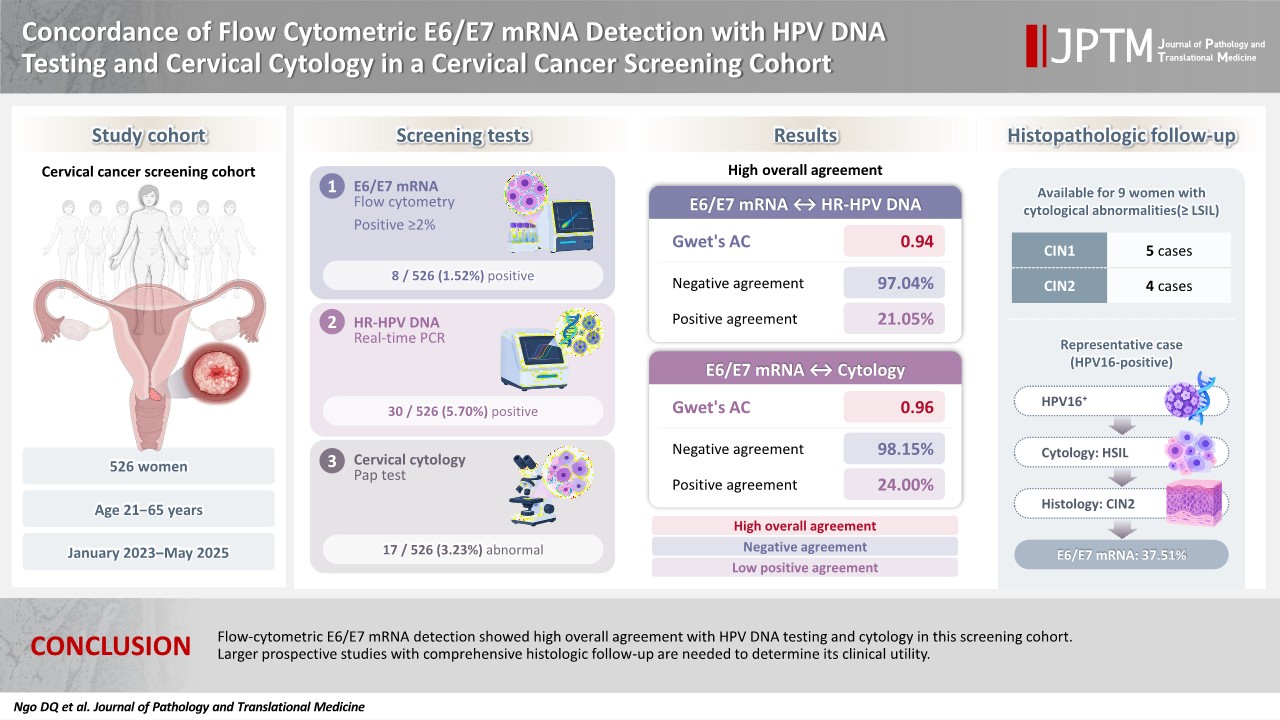
Overexpression of viral oncogenes E6 and E7 of high-risk (HR)–human papillomavirus (HPV) plays a key role in the progression to cervical intraepithelial neoplasia (CIN) and cancer. Detection of E6/E7 mRNA may help distinguish between transient and transforming infections, thus improving cervical cancer screening accuracy. This study aimed to evaluate the association of E6/E7 mRNA expression with HR-HPV infection, cervical cytology, and histologically confirmed cervical lesions and to compare its agreement with HPV DNA testing and cytology. Methods: A total of 526 women undergoing cervical cancer screening between January 2023 and May 2025 were enrolled. E6/E7 mRNA expression was assessed using flow cytometry with the HPV OncoTect 3Dx E6/E7 mRNA assay and compared with HR-HPV DNA testing, cervical cytology, and available histopathologic findings from biopsy specimens. Results: Among 526 samples, eight (1.5%) tested positive for E6/E7 mRNA, compared to 30 (5.7%) HR-HPV DNA–positive and 17 (3.2%) abnormal cytology results. Median E6/E7 mRNA expression was higher in HR-HPV– positive cases and in cytologically abnormal cases. Almost perfect agreement was observed between E6/E7 mRNA results, HR-HPV DNA testing, and cytology. Histopathologic follow-up was available for nine women with cytological abnormalities ≥low-grade squamous intraepithelial lesion, including four CIN2 and five CIN1 cases. E6/E7 mRNA expression was markedly elevated in one CIN2 case associated with HPV16 infection (37.51%), while two CIN1 cases demonstrated high mRNA expression despite negative HPV DNA results. Conclusions: Flow-cytometric E6/E7 mRNA detection showed high overall agreement with HPV DNA testing and cytology in this screening cohort. Larger prospective studies with comprehensive histologic follow-up are needed to determine its clinical utility.
- Targeted next-generation sequencing–based mutational signature analysis in endometrial cancer: utility and limitations across molecular subtypes
- Uijin Kim, Ahwon Lee, Keun Ho Lee, Sung Jong Lee, Sook Hee Hong, Donghyuk Lee, Jun Kang, Miseon Lee
- J Pathol Transl Med. 2026;60(6):625-634. Published online November 10, 2026
- DOI: https://doi.org/10.4132/jptm.2026.09.07
- 729 View
- 14 Download
-
Abstract
PDFSupplementary Material
- Background
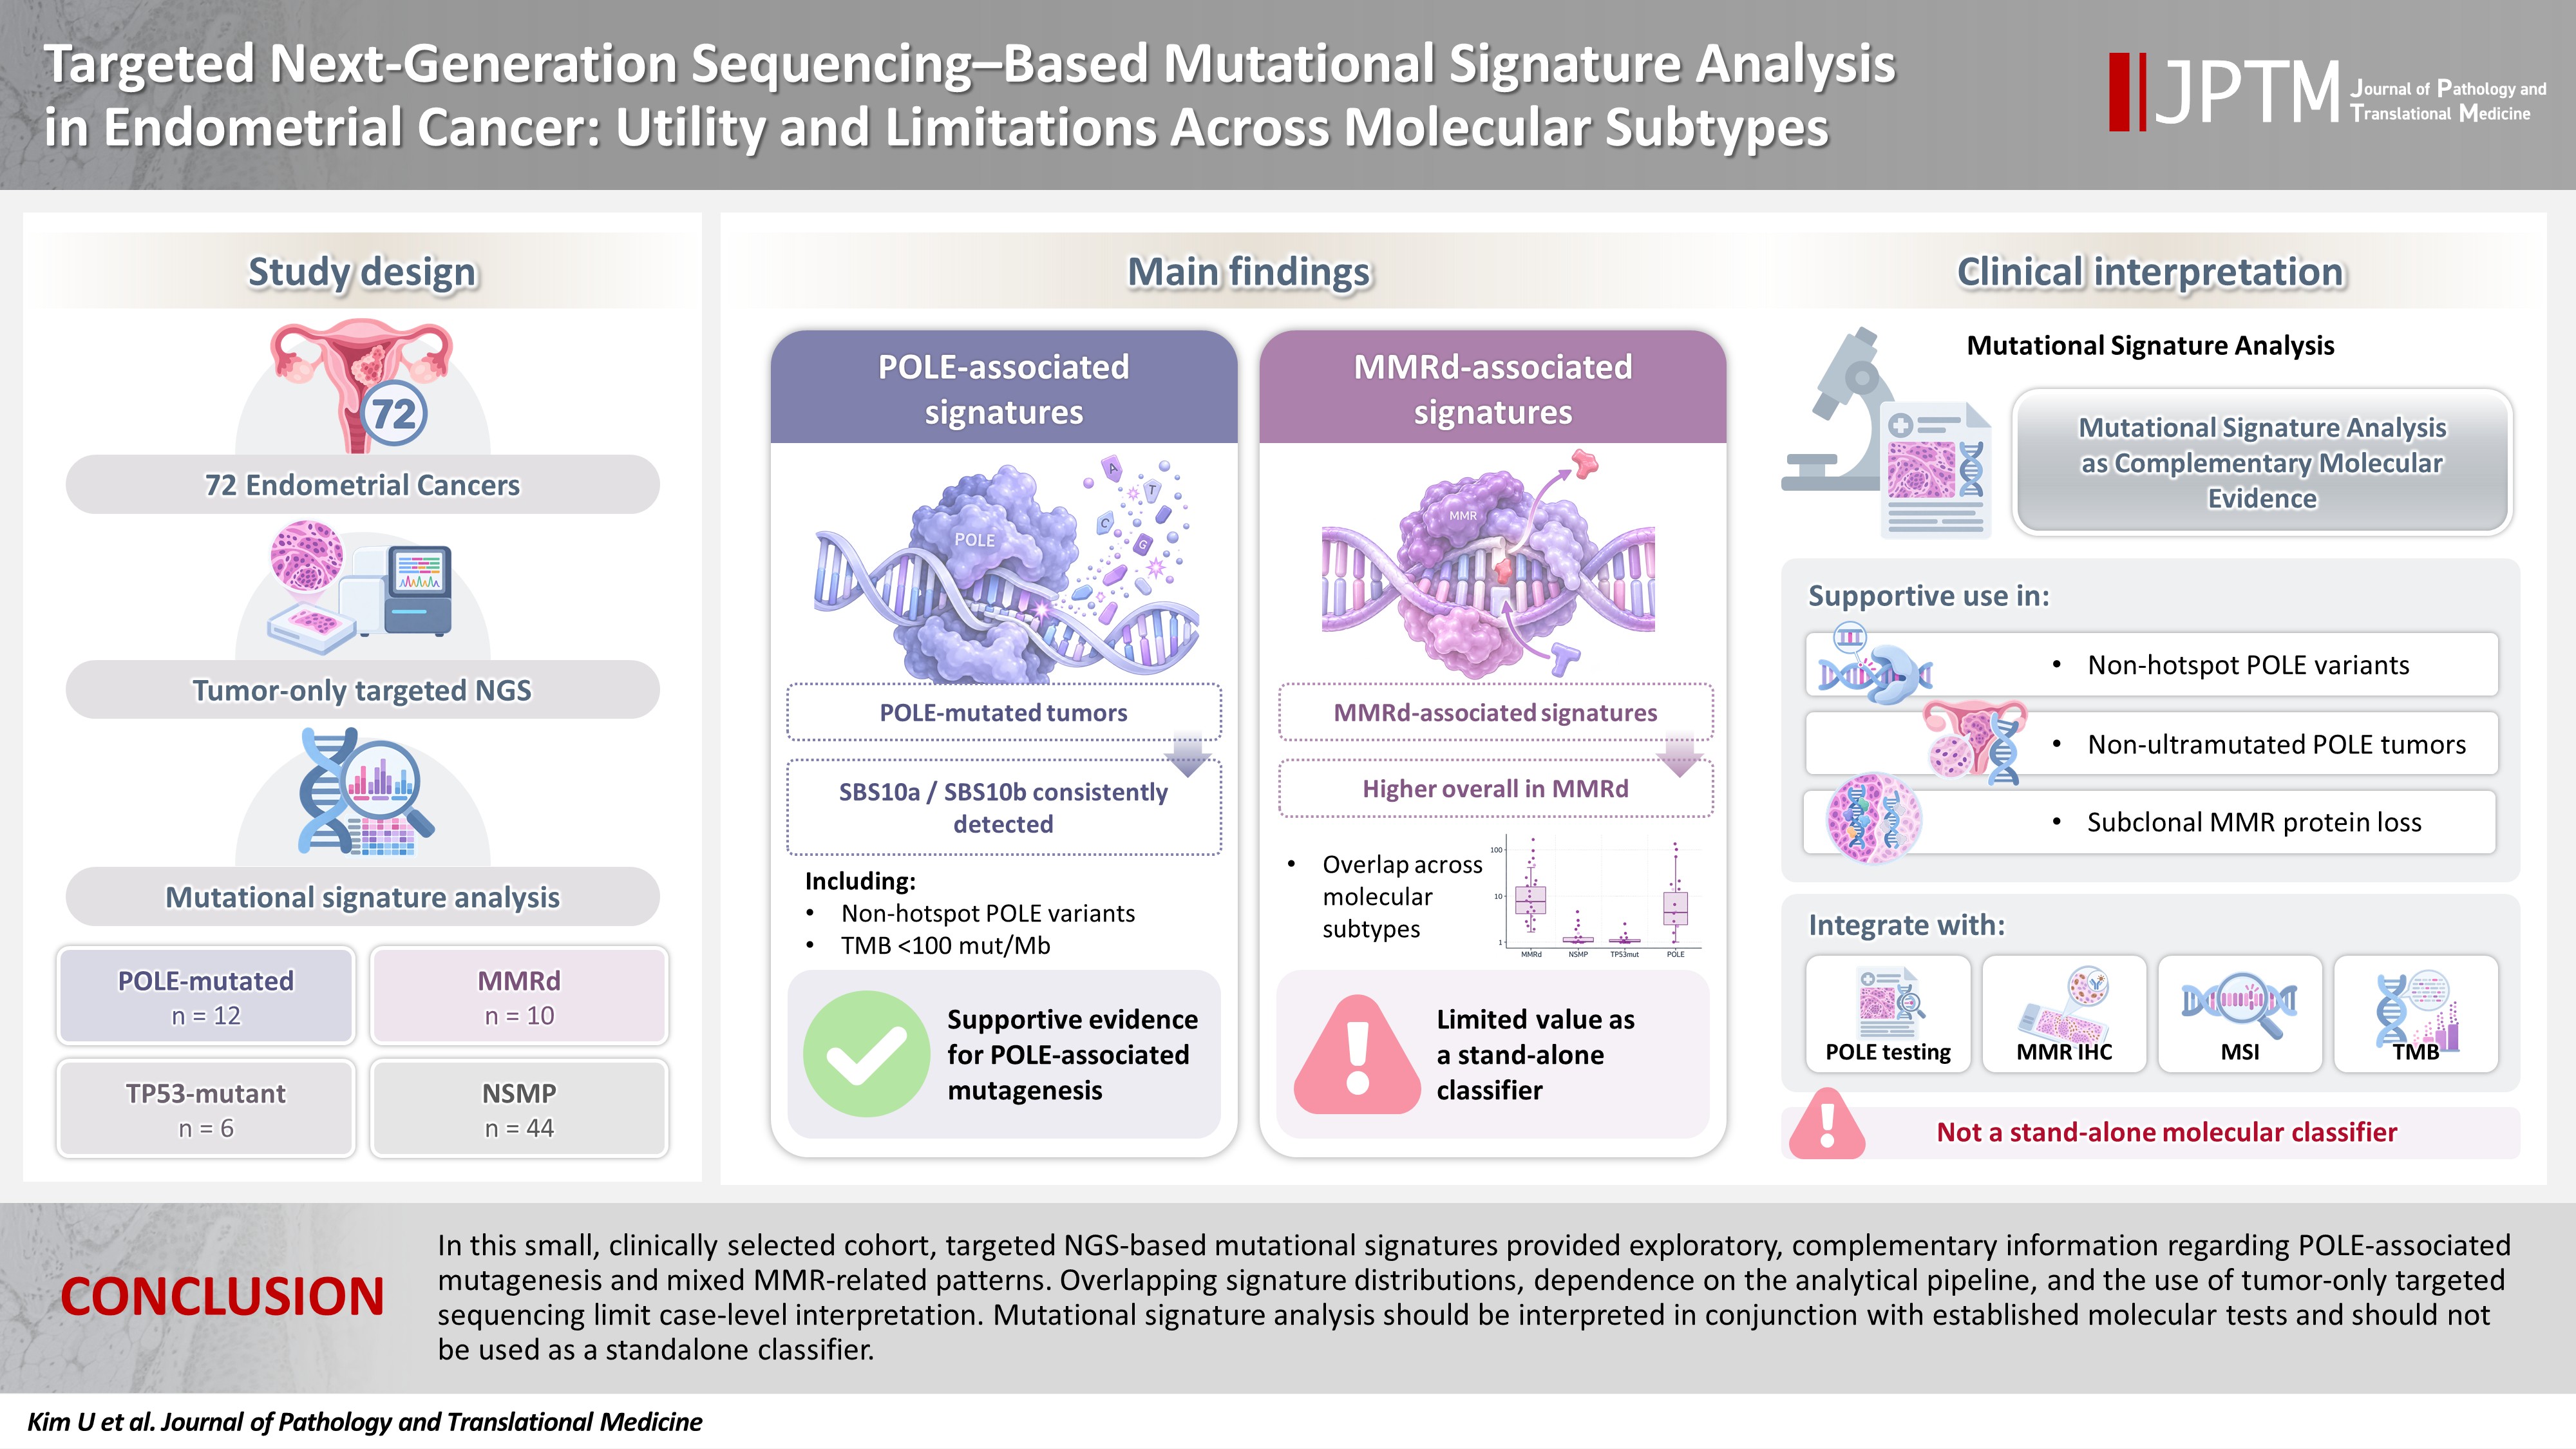
Molecular subtype classification is essential for staging endometrial cancer, planning adjuvant treatments, and stratifying prognosis. However, the correlation between mutational signature analysis using tumor-only targeted next-generation sequencing (NGS) data and molecular subtypes, as well as the interpretive value at the individual case level, remains inadequately characterized. Methods: We performed mutational signature analysis on tumor-only targeted NGS data from 72 endometrial cancer cases using the SATS R package. Molecular classification into four subtypes (POLE-mutated, mismatch repair deficient [MMRd], TP53-mutant, and no specific molecular profile [NSMP]) was established through a standard stepwise algorithm that integrated NGS and immunohistochemistry. Results: Out of the 72 endometrial cancers, 12 were classified as POLE-mutated, 10 as MMRd, six as TP53-mutant, and 44 as NSMP. All POLE-mutated tumors exhibited POLE-associated signatures (SBS10a/SBS10b), including cases with non-hotspot POLE exonuclease variants and tumor mutation burdens below the conventional ultramutation threshold. MMRd-associated signatures showed a broader distribution across molecular subtypes; while the summed MMRd-associated signatures were typically higher in MMRd tumors, low-level contributions were also noted in subsets of NSMP and TP53-mutant tumors. Within the POLE-mutated group, MMRd-associated signatures were more pronounced in cases displaying subclonal MMR protein loss as determined by immunohistochemistry. Conclusions: In this small, clinically selected cohort, targeted NGS-based mutational signatures provided exploratory, complementary information regarding POLE-associated mutagenesis and mixed MMR-related patterns. Overlapping signature distributions, dependence on the analytical pipeline, and the use of tumor-only targeted sequencing limit case-level interpretation. Mutational signature analysis should be interpreted in conjunction with established molecular tests and should not be used as a stand-alone classifier.
Case Studies
- Extra-axial poorly differentiated chordoma of the knee masquerading as periprosthetic joint infection: a case report
- Hee-Jung Yang, Hye Ra Jung, Joon Hyuk Choi, Chang-Jin Yon, Sang Pyo Kim
- J Pathol Transl Med. 2026;60(6):710-717. Published online November 10, 2026
- DOI: https://doi.org/10.4132/jptm.2026.08.31
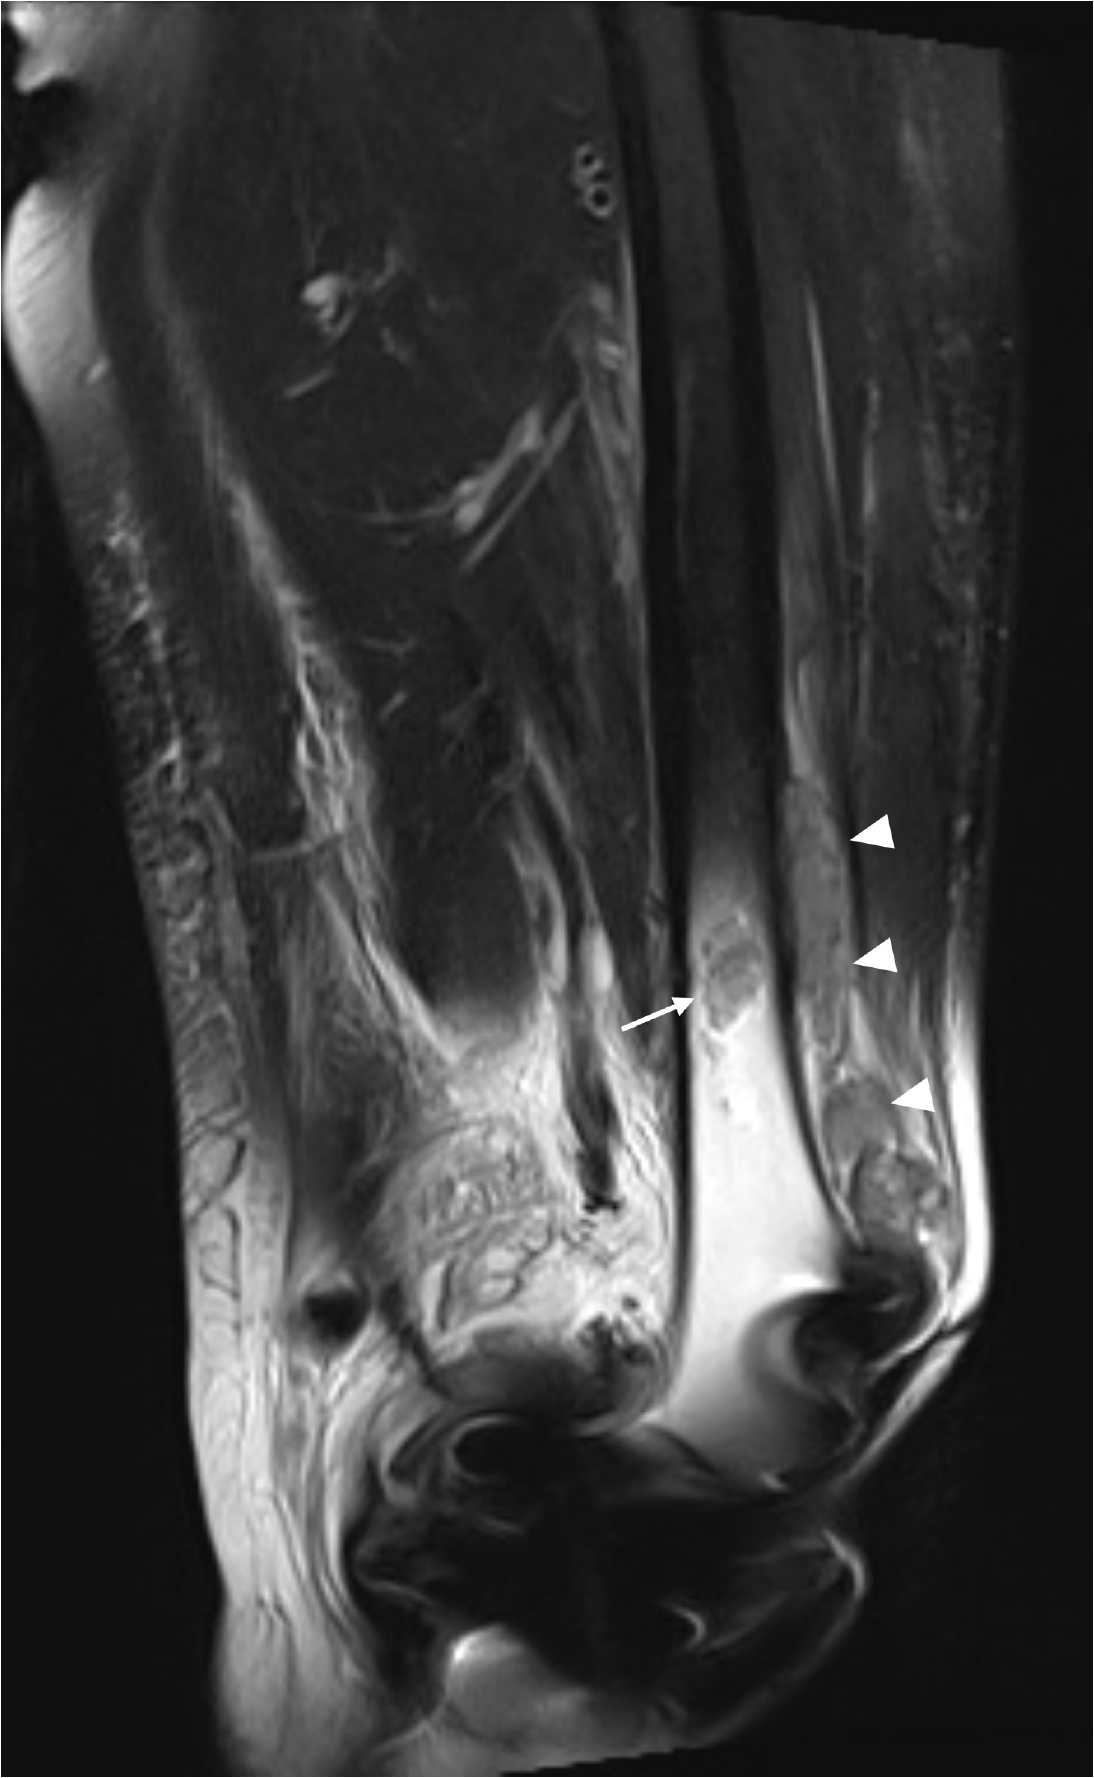
- 512 View
- 10 Download
-
Abstract
PDFSupplementary Material
- Poorly differentiated chordoma (PDC) is a malignant neoplasm defined by the co-expression of brachyury and cytokeratin with loss of SMARCB1 (INI-1) expression. Extra-axial PDC is exceedingly rare, with only 10 cases reported to date. Here, we report an additional case of extra-axial PDC arising in the soft tissues surrounding the knee joint of a 69-year-old woman, which was initially misdiagnosed as periprosthetic joint infection following total knee arthroplasty. Histologically, the tumor comprised epithelioid to spindled cells with vacuolated, eosinophilic cytoplasm, focal rhabdoid areas, without myxoid stroma. Immunohistochemically, the tumor cells showed diffuse positivity for brachyury and cytokeratin, with loss of INI-1 expression. Next-generation sequencing identified a homozygous deletion of CDKN2A, but no SMARCB1 genomic alteration was detected despite INI-1 loss. This case shows that extra-axial PDC should be considered in the differential diagnosis of soft tissue tumors, irrespective of anatomical site or morphology.
- Silicone lymphadenopathy of the axilla: a potential for misdiagnosis as metastatic carcinoma on fine-needle aspiration cytology
- Nah Ihm Kim, Hyo-Jae Lee, Ji Shin Lee
- J Pathol Transl Med. 2026;60(6):726-731. Published online November 3, 2026
- DOI: https://doi.org/10.4132/jptm.2026.09.08
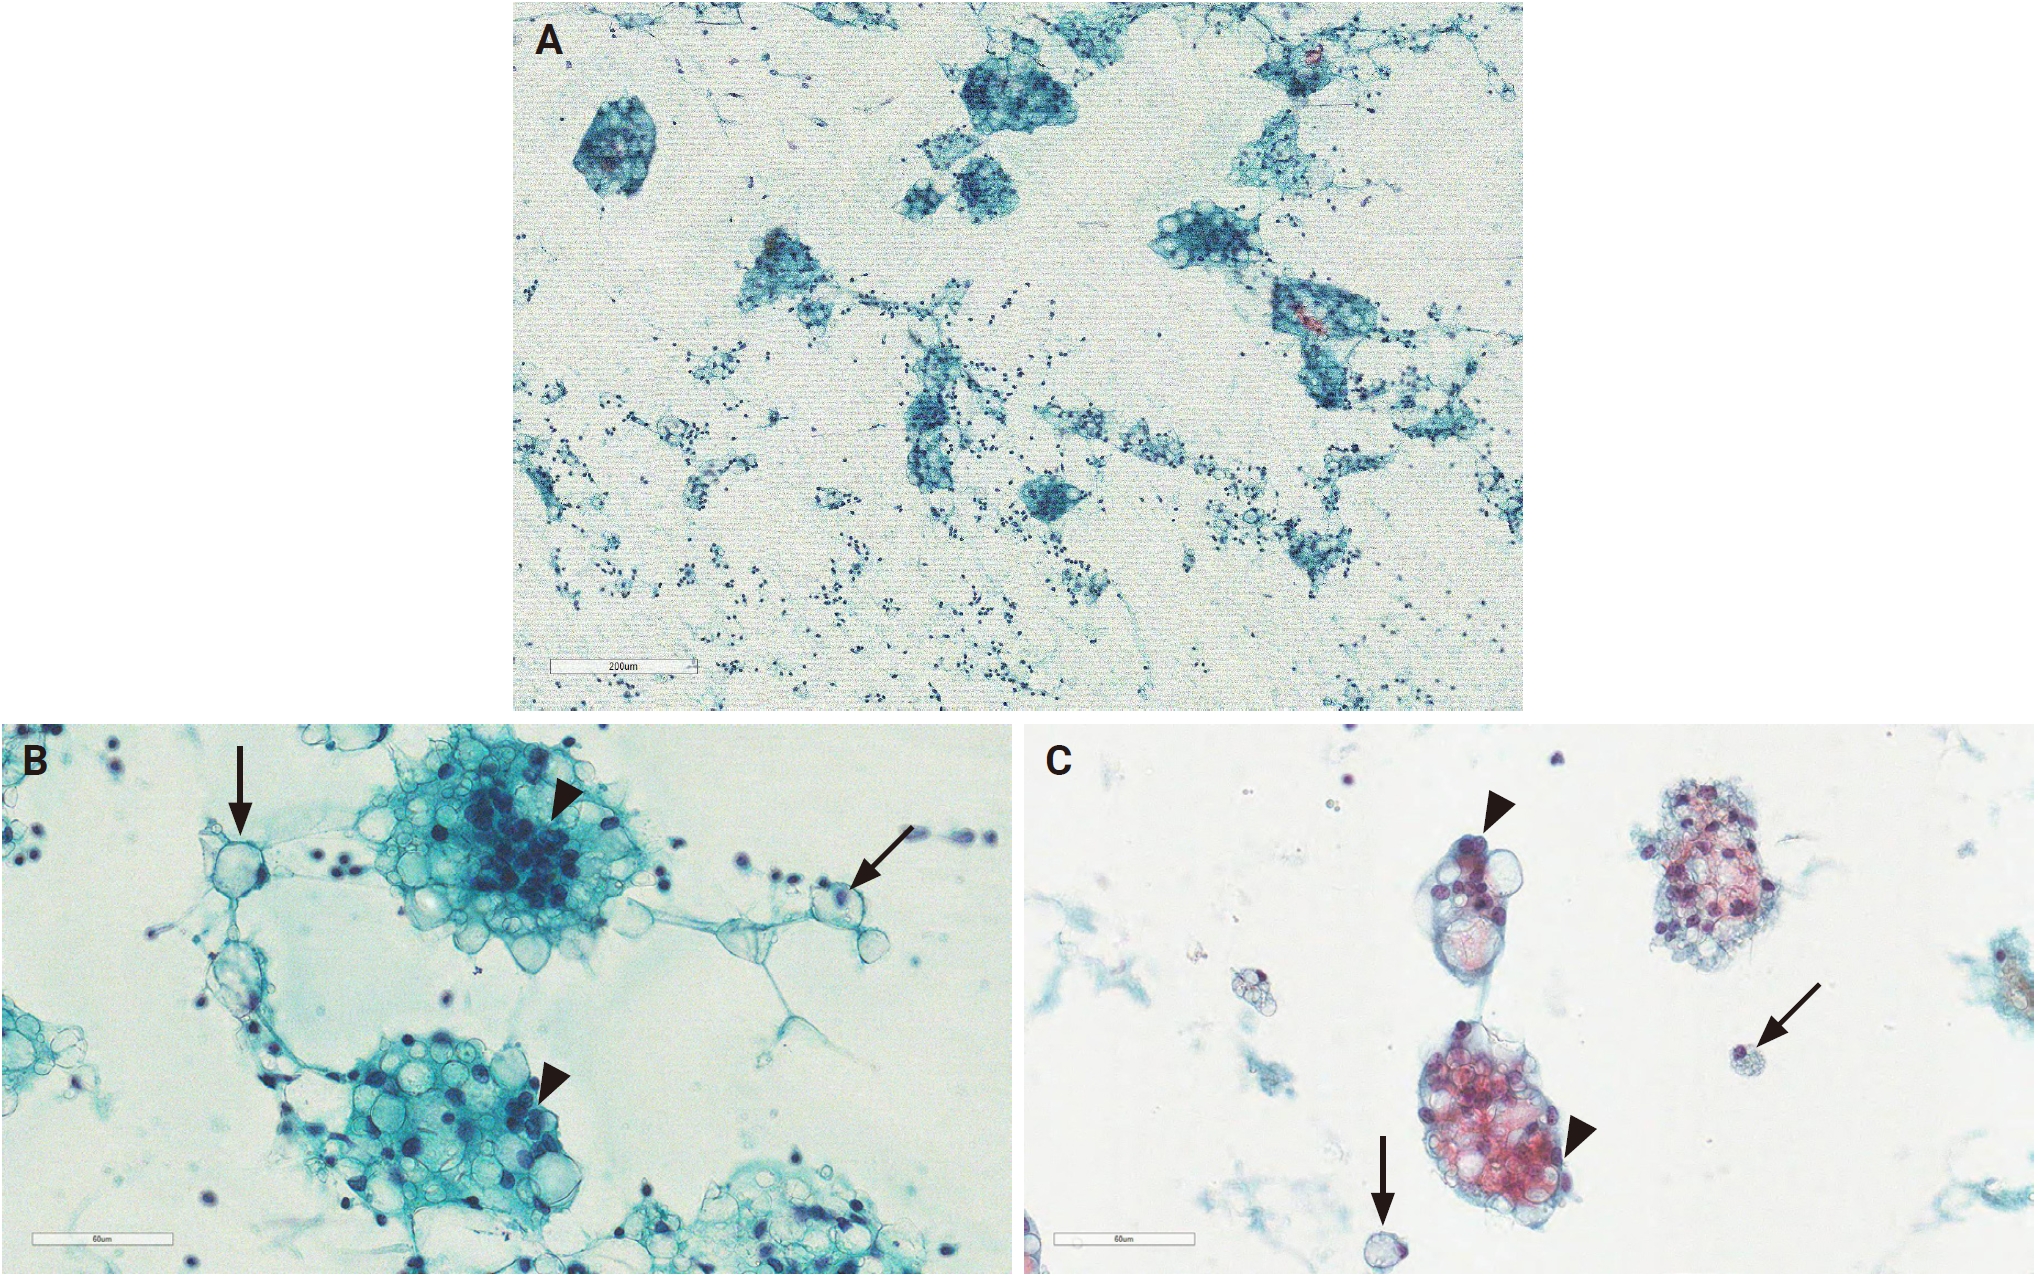
- 645 View
- 19 Download
-
Abstract
PDF
- Silicone lymphadenopathy is an uncommon but well-recognized complication of silicone implant placement resulting from migration of silicone to regional lymph nodes. In patients with prior breast implantation, silicone lymphadenopathy most commonly involves the axillary lymph nodes. Because axillary lymphadenopathy may reflect malignant disease, including metastatic carcinoma, thorough evaluation to exclude neoplasia is essential. Fine-needle aspiration cytology (FNAC) serves as a valuable initial diagnostic modality in the assessment of axillary lymphadenopathy; however, silicone-induced foreign body reactions within lymph nodes may be misinterpreted as metastatic malignancy when silicone lymphadenopathy is not included in the initial differential diagnosis. Herein, a case of axillary silicone lymphadenopathy initially misdiagnosed as metastatic carcinoma on FNAC is presented. This case highlights the importance of recognizing the distinctive cytomorphologic features of silicone lymphadenopathy, which may be sufficiently characteristic to prompt consideration of prior breast implant history during cytopathologic evaluation.
- Meningioma harboring IDH1 R132H mutation: a case report
- Soyeon Ahn, Chung Lee, Jong-Pil Park, Se Hoon Kim
- J Pathol Transl Med. 2026;60(6):704-709. Published online November 3, 2026
- DOI: https://doi.org/10.4132/jptm.2026.08.19
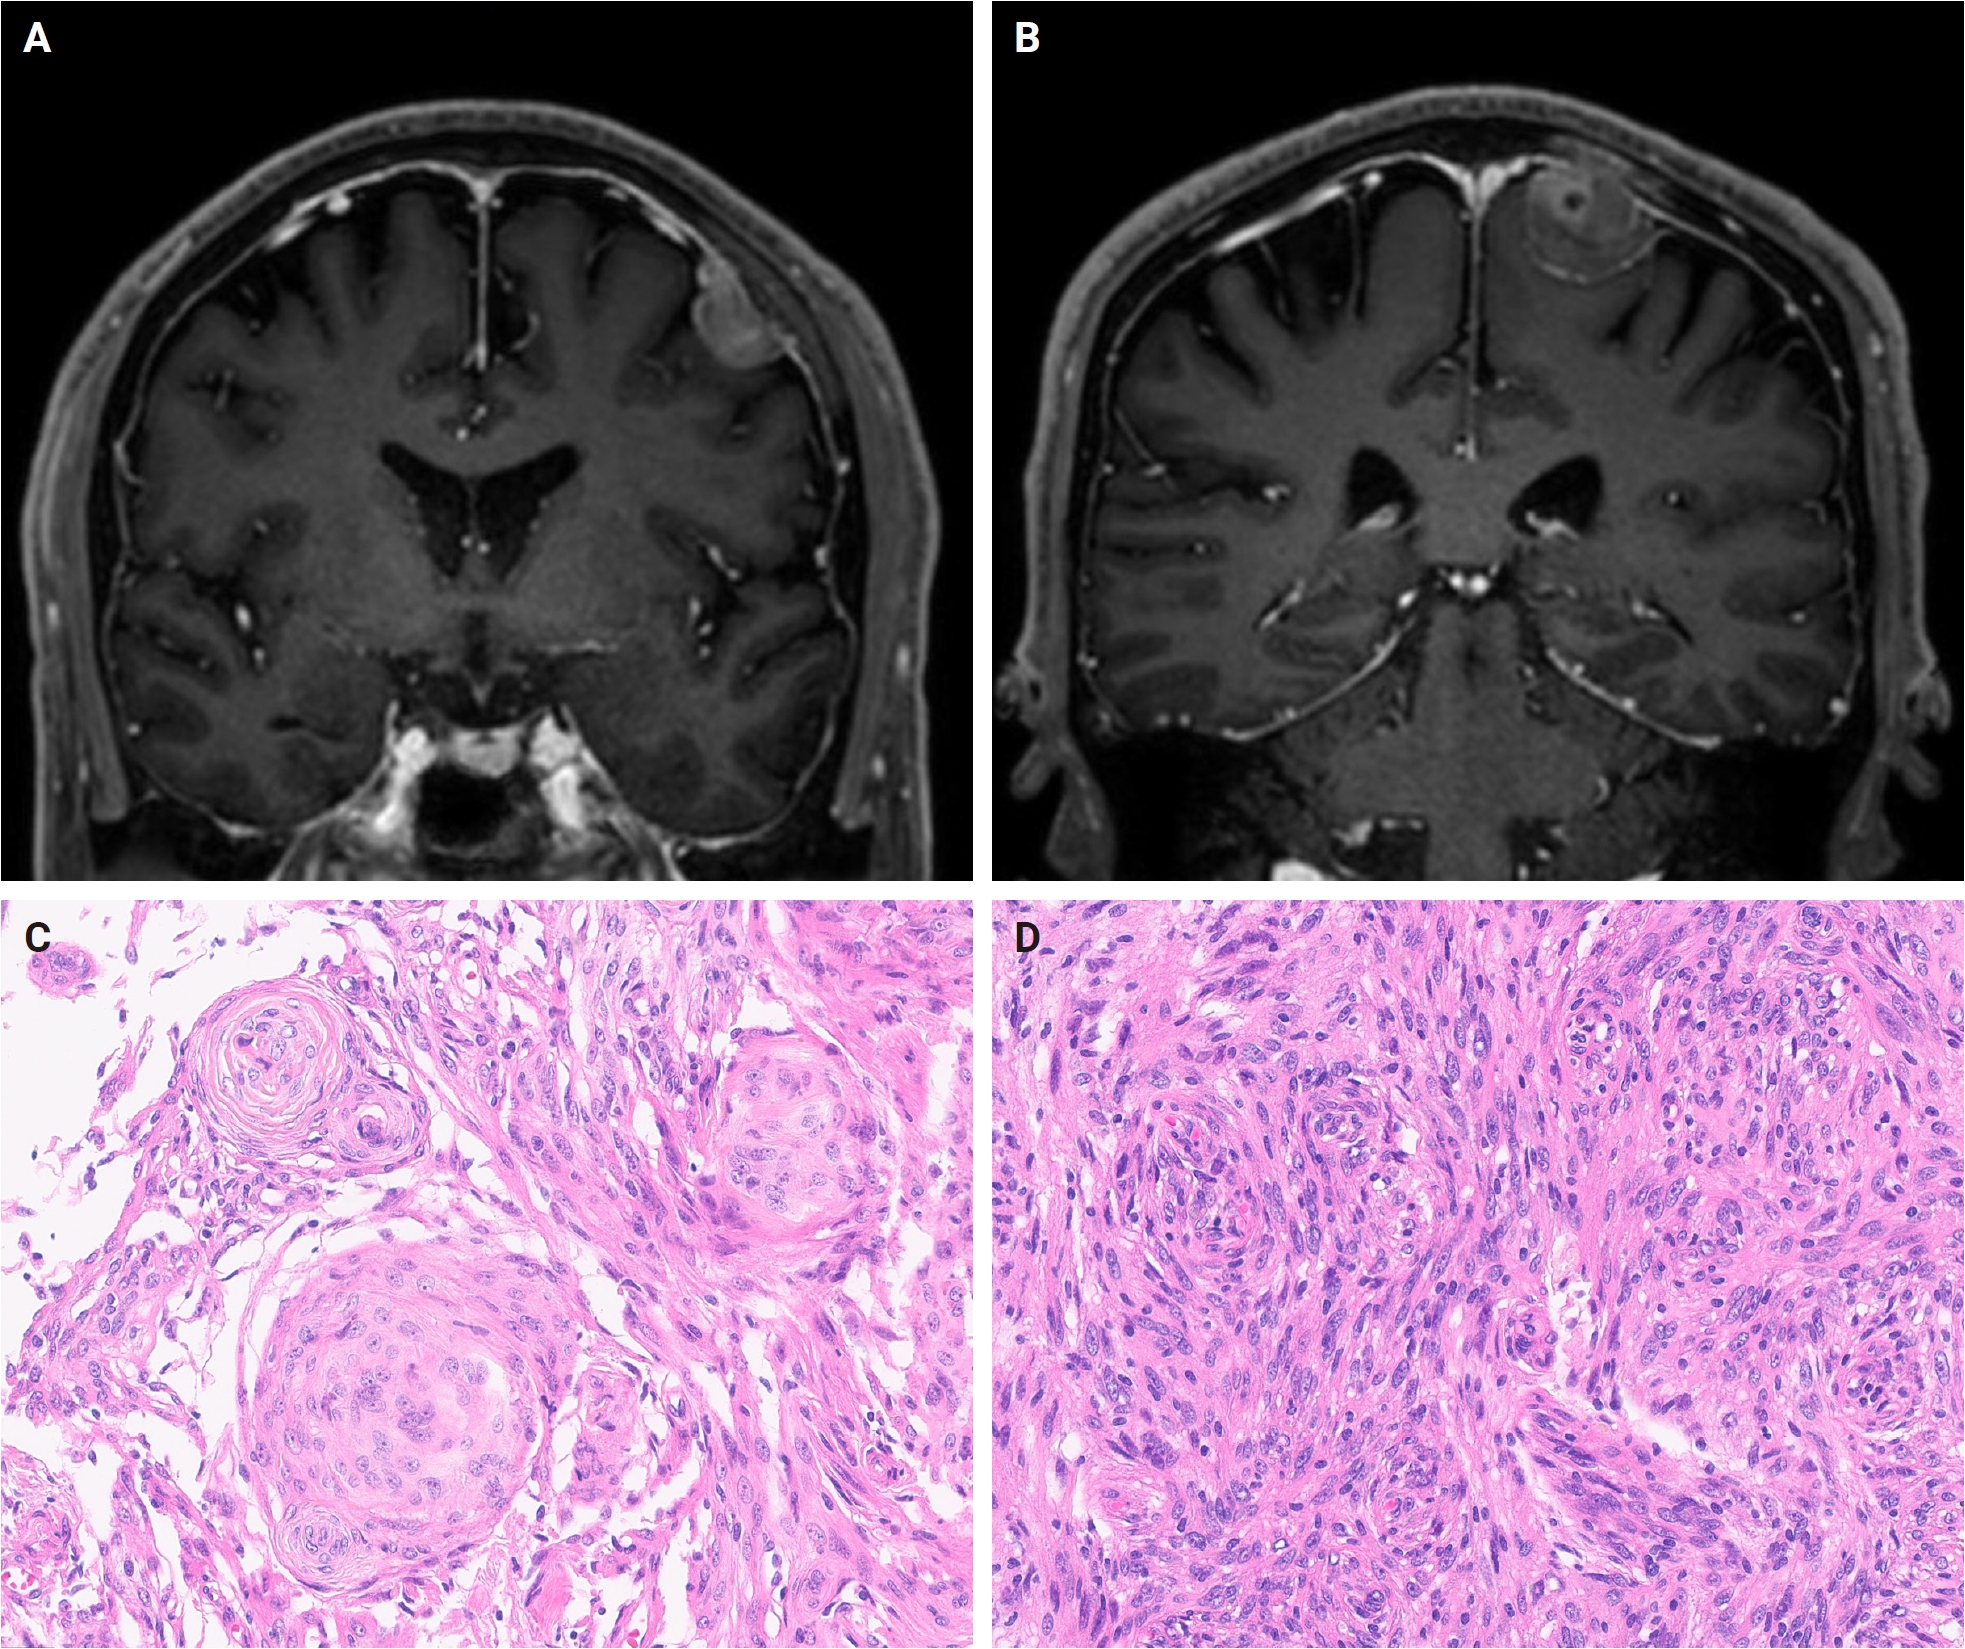
- 711 View
- 23 Download
-
Abstract
PDF
- Meningiomas are the most common primary central nervous system tumors. Monosomy of chromosome 22 is the most frequently reported genetic abnormality in meningioma and the occurrence of IDH1 mutations in meningioma is exceedingly rare. We report an uncommon case of IDH1 R132H-mutant meningioma. A 69-year-old man presented with two intracranial masses, one of which was identified as an IDH1 R132H-mutant meningioma by next-generation sequencing and further confirmed by pyrosequencing and immunohistochemistry. The rarity of this molecular finding and the potentially favorable prognosis observed in previously reported cases highlight the need for its recognition as a distinct molecular subset. Isocitrate dehydrogenase–targeted therapy may represent a future therapeutic option, pending validation through prospective studies and larger case series.
- Colorectal intramucosal carcinoma with lymphatic invasion and lymph node metastasis: a case report
- Joon Mee Kim, Lucia Kim, Jee Young Han, Suk Jin Choi, Jongbeom Shin, Sun Keun Choi
- J Pathol Transl Med. 2026;60(6):698-703. Published online October 19, 2026
- DOI: https://doi.org/10.4132/jptm.2026.08.14
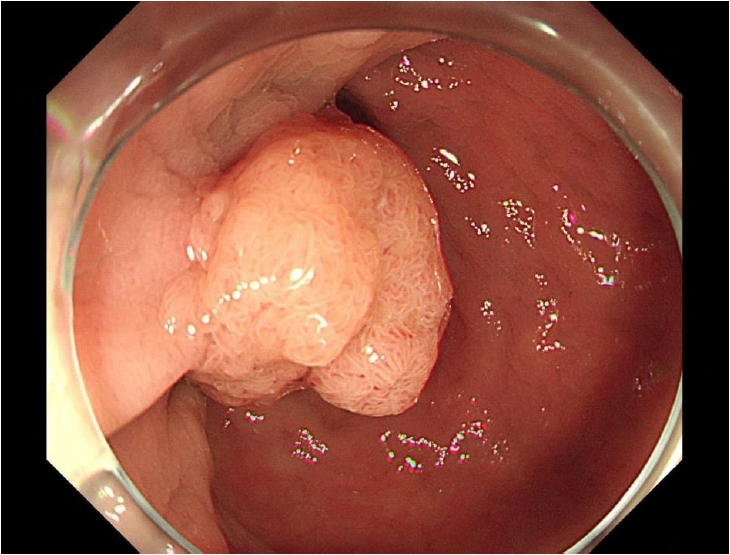
- 1,074 View
- 15 Download
-
Abstract
PDF
- Colorectal intramucosal carcinoma (IMC) is considered to carry negligible risk of lymph node metastasis, reflecting the presumed absence of lymphatics within the lamina propria, and current guidelines endorse endoscopic resection alone as curative. We report a 64-year-old man in whom endoscopic submucosal dissection of a lower rectal tumor revealed a well-differentiated IMC with extensive lymphatic invasion confirmed by D2-40 immunostaining. Subsequent laparoscopic ultralow anterior resection showed no residual tumor at the primary site but confirmed metastasis in one of 12 regional lymph nodes. The tumor was microsatellite-stable, epidermal growth factor receptor–positive, and harbored a KRAS codon 13 mutation (G13X). The patient received adjuvant chemoradiotherapy and remained disease-free at 2 years. This case demonstrates that regional lymph node metastasis can occur in colorectal IMC even without conventional adverse histologic features such as poor differentiation or tumor budding, challenging current risk-stratification frameworks and supporting a more cautious approach when lymphatic invasion is identified.
Original Article
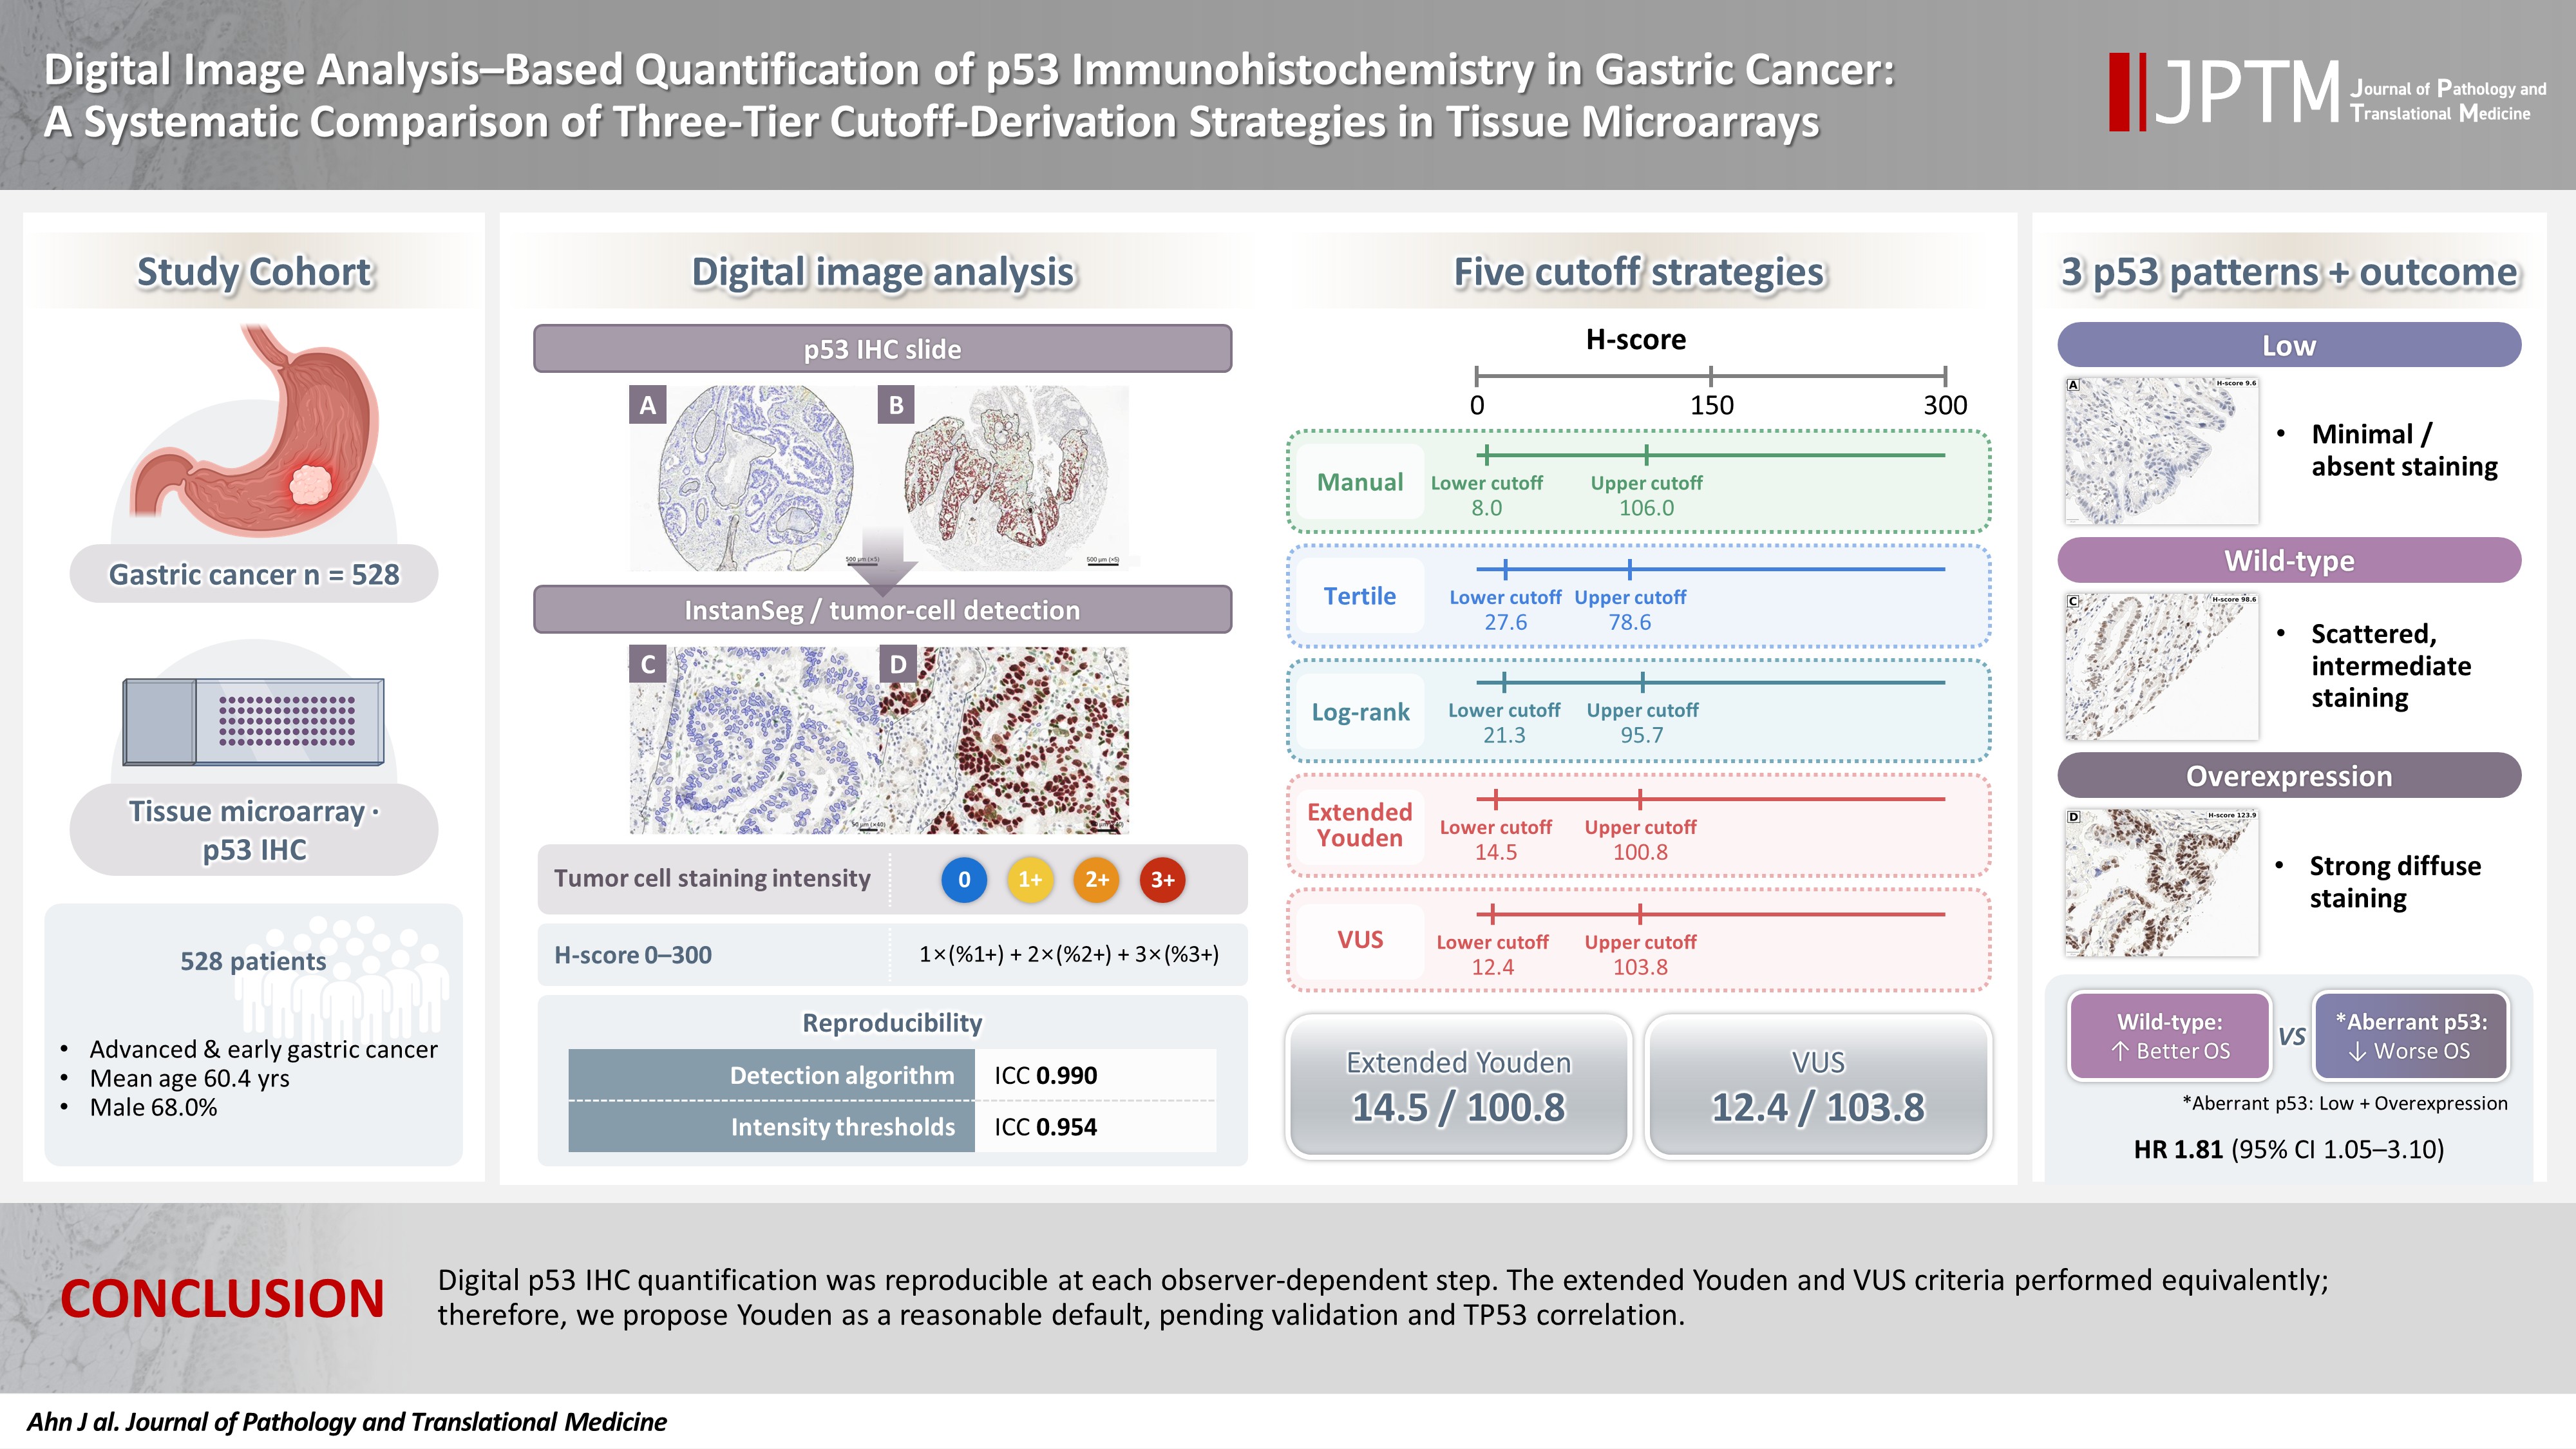
- Digital image analysis–based quantification of p53 immunohistochemistry in gastric cancer: a systematic comparison of three-tier cutoff-derivation strategies in tissue microarrays
- Jaeyoung Ahn, Kyungeun Kim, Hee-Jung Yang, Boram Song, Dong Hoon Kim, Yumin Chung, Seoung Wan Chae
- J Pathol Transl Med. 2026;60(6):593-610. Published online October 19, 2026
- DOI: https://doi.org/10.4132/jptm.2026.08.13
- 1,675 View
- 28 Download
-
Abstract
PDFSupplementary Material
- Background
p53 immunohistochemistry (IHC) is a common surrogate for TP53 alteration, but in gastric cancer, its concordance is imperfect and depends on a non-standardized cutoff. Digital pathology enables H-score quantification, yet neither its reproducibility nor the choice of cutoff- derivation strategy has been systematically compared. Methods: A semi-automated digital workflow quantified p53 IHC in tissue microarrays from 528 gastric cancer patients. Tumor cells were detected with a deep-learning model (InstanSeg), and nuclear staining was expressed as a continuous H-score (0–300). Reproducibility was assessed at each observer-dependent step. Five thresholding strategies were compared: manual cutoffs, tertiles, log-rank optimization, the extended Youden index, and volume under the receiver operating characteristic surface (VUS). The latter two strategies used the manual three-tier IHC interpretation as the reference standard. Results: Quantification was reproducible: two independent manual interpretations agreed in 91.7% of cores (κ = 0.845). The H-score was robust to the detection algorithm (intraclass correlation coefficient, 0.990) and to repeated threshold determination (0.954). H-scores were right-skewed (median, 45.5), and the strategies yielded distinct cutoffs (8.0–27.6 and 78.6–106.0). Log-rank optimization provided the widest separation but lost significance after multiplicity adjustment (p = .168). The extended Youden and VUS cutoffs were statistically indistinguishable. As a supporting check, all classifications showed nominal overall-survival separation, with low and overexpression faring similarly worse than wild-type. Conclusions: Digital p53 IHC quantification was reproducible at each observer-dependent step. The extended Youden and VUS criteria performed equivalently; therefore, we propose Youden as a reasonable default, pending validation and TP53 correlation.
Review Article
- T-lymphoblastic leukemia/lymphoma: a comprehensive review of pathology, molecular features, and differential diagnosis
- David Danielson, Ian T. Lagerstrom, Max Rogers, Kyle Simon, Nadine S. Aguilera, Aaron Auerbach
- J Pathol Transl Med. 2026;60(5):502-515. Published online September 15, 2026
- DOI: https://doi.org/10.4132/jptm.2026.08.01

- 3,624 View
- 73 Download
- 1 Crossref
-
Abstract
PDF
- T-lymphoblastic leukemia/lymphoma (T-ALL/LBL) is an aggressive neoplasm of immature T-lymphoid precursors that is classified as T-cell acute lymphoblastic leukemia when the primary site of involvement is the bone marrow and peripheral blood and as T-cell lymphoblastic lymphoma when it presents as a solid mass, most commonly in the anterior mediastinum. The neoplastic cells are defined by expression of T-lineage antigens (cytoplasmic or surface CD3) together with one or more markers of immaturity (terminal deoxynucleotidyl transferase, CD1a, CD34, CD99, or CD117) and must not fulfill criteria for early T-cell precursor acute lymphoblastic leukemia (ALL). This entity shows a marked male predominance (male:female ≈ 2:1) and predominantly affects children, adolescents, and young adults, accounting for approximately 15% of childhood ALL and 20%–25% of adult ALL cases. Pathologic diagnosis increasingly relies on recurrent molecular alterations such as activating NOTCH1 mutations (>60% of cases), transcription factor rearrangements, and cell-cycle regulator inactivation. Although intensive multiagent chemotherapy regimens have substantially improved outcomes, particularly in pediatric patients, adults and high-risk molecular subgroups continue to experience inferior survival. This review provides a practical, pathology-oriented update on the epidemiology, pathogenesis, diagnostic criteria, differential diagnosis, prognostic factors, and current treatment approaches for T-ALL/LBL.
-
Citations
Citations to this article as recorded by
- Targeting DNA Ligase III Addiction in T-Cell Acute Lymphoblastic Leukemia by the Natural Flavonoid Rhamnetin
Stefania Signorelli, Giada Juli, Serena Ascrizzi, Nicoletta Polerà, Maria Gaetano, Sara Squillacioti, Emanuela Altomare, Amalia Gagliardi, Pierfrancesco Tassone, Pierosandro Tagliaferri, Katia Grillone, Licia Pensabene, Daniele Caracciolo
International Journal of Molecular Sciences.2026; 27(22): 10148. CrossRef
- Targeting DNA Ligase III Addiction in T-Cell Acute Lymphoblastic Leukemia by the Natural Flavonoid Rhamnetin
Original Article
- Diagnostic performance of fine needle aspiration cytology in the preoperative identification of mucoepidermoid carcinoma: a cross-sectional diagnostic analytical study
- Sumaya , Dishant Ramkrishna Sonuwane, Amita Krishnappa
- J Pathol Transl Med. 2026;60(5):549-557. Published online September 15, 2026
- DOI: https://doi.org/10.4132/jptm.2026.07.08

- 1,536 View
- 90 Download
-
Abstract
PDFSupplementary Material
- Background
Mucoepidermoid carcinoma (MEC), the most common malignant tumor of the salivary gland, accounts for 5%–10% of all salivary gland tumors. MEC shows extensive cytomorphological diversity, making preoperative diagnosis challenging. Hence, the present study was conducted to assess the diagnostic accuracy of fine-needle aspiration cytology (FNAC) in diagnosing MEC preoperatively and to discuss the cytological pitfalls in diagnosing mucoepidermoid carcinoma. Methods: The present study was a cross-sectional diagnostic analytical study conducted over a period of five years, which included confirmed cases of MEC. Each case was classified according to the Milan System for Reporting Salivary Gland Cytopathology (MSRSGC) and individual cytomorphological features were noted. All cases were compared by considering histopathology as the gold standard for diagnosis. Sensitivity, specificity, positive predictive value (PPV), and negative predictive value (NPV) of FNAC in diagnosing MEC were calculated to evaluate the diagnostic accuracy of FNAC. Results: All 42 cases of MEC were reclassified according to MSRSGC as follows: category II, one case; category III, one case; category IVA, two cases; category IVb, one case; category V, four cases; and category VI, 33 cases. Discordant cases (5 cases) were mainly due to cystic change, low cellularity, and overlapping features with benign lesions. The sensitivity, specificity, PPV, NPV, and diagnostic accuracy were found to be 88.1%, 100%, 100%, 97.4%, and 97.8%, respectively. Conclusions: FNAC is an important preoperative diagnostic investigation for MEC as reflected by its high specificity, sensitivity, and overall diagnostic accuracy in the present study. Careful attention to individual cytomorphological features and clinicoradiological correlation can significantly improve the diagnostic accuracy by directing the clinicians for further management.
Review Article
- Spread through air spaces as a marker of nonlinear evolutionary trajectories in lung cancer: implications for the 9th edition TNM classification
- Jin-Haeng Chung
- J Pathol Transl Med. 2026;60(5):463-475. Published online September 15, 2026
- DOI: https://doi.org/10.4132/jptm.2026.06.16

- 2,906 View
- 49 Download
-
Abstract
PDF
- Recent advancements in the diagnosis and therapeutic management of lung cancer have contributed to an evolution in pathological reporting standards. The 8th edition of the TNM classification of lung tumors has introduced the invasive size of adenocarcinoma—rather than total tumor size—as the primary determinant for staging. Concurrently, histological grading criteria proposed by the International Association for the Study of Lung Cancer (IASLC), based on predominant and highest-grade architectural patterns, appear to offer improved clinical utility over legacy systems. In addition, tumor spread through air spaces (STAS) has emerged as an actively investigated pattern of invasion, characterized by the presence of neoplastic cells beyond the main tumor mass within the adjacent pulmonary parenchyma. STAS is frequently observed in advanced-stage and node-positive non–small cell lung cancer and often correlates with distant metastasis. Recognizing its clinical relevance, the IASLC Staging Project recently recommended incorporating STAS as a histologic T descriptor in the 9th edition of the TNM classification. Expanding upon this framework, this review explores STAS not merely as a prognostic indicator, but as a potential reflection of divergent evolutionary trajectories influenced by underlying driver mutations. Accordingly, this review aims to comprehensively synthesize the prevailing controversies and recent academic milestones regarding STAS, the current limitations in preoperative STAS risk prediction, the logistical hurdles of intraoperative diagnosis, and critically evaluates the need for prospective clinical trials to validate STAS as a predictive biomarker for adjuvant systemic therapy.
Original Articles
- BRCA1/2-stratified immune profiling of treatment-naive high-grade serous ovarian cancer ascites identifies a Treg-enriched ascitic immune phenotype
- Megha Sharma, Bhavneet Kaur, Bhavana Rai, Man Updesh Singh Sachdeva, Amit Raj Sharma, Parikshaa Gupta, Upasana Gautam, Rashmi Bagga, Radhika Srinivasan
- J Pathol Transl Med. 2026;60(5):558-571. Published online September 11, 2026
- DOI: https://doi.org/10.4132/jptm.2026.07.27

- 2,044 View
- 31 Download
-
Abstract
PDFSupplementary Material
- Background
Malignant ascites is a common presentation in advanced high-grade serous ovarian carcinoma (HGSOC), yet its immune composition and genetic correlates remain poorly defined. This study explored the immune microenvironment of ascitic fluid in ovarian carcinoma and its association with BRCA mutation status, chemotherapy response, and survival. Methods: Ascitic fluid from 133 patients (33 non-malignant controls, 31 non-ovarian carcinoma, and 69 HGSOC cases) was analyzed using multiparameter flow cytometry to quantify lymphocyte and macrophage subsets, and programmed cell death 1/programmed cell death ligand 1 immune-checkpoint marker expression. Targeted sequencing of TP53 and BRCA1/2 was performed in HGSOC, and findings were correlated to immune parameters, chemotherapy response, progression-free and overall survival. Results: Ovarian carcinoma ascites, compared with non-malignant effusions, showed increased CD3+ and CD8+ T-cell frequencies, higher regulatory T cell (Treg)–associated populations, and reduced CD19+CD20+ B-cell levels. Targeted sequencing identified TP53 mutations in 97.4% and BRCA1/2 mutations in 35.9% of sequenced HGSOC cases. BRCA-wild-type cases showed significantly lower CD4+ T-cell and B-cell levels, higher Treg levels, and shorter progression-free and overall survival than BRCA1/2-mutated cases. Higher CD3+ and CD8+ T-cell levels were associated with poor chemotherapy response. In exploratory multivariable Cox models, BRCA-wild-type status remained significantly associated with poorer overall survival, whereas immune-cell groups were not independently significant. Conclusions: HGSOC ascites showed a Treg-enriched immune profile, with relatively higher Treg levels in BRCA-wild-type cases. BRCA-wild-type status was associated with poorer outcomes, while the evaluated immune-cell subsets were not independently prognostic in exploratory analysis. Ascitic fluid-based immune and molecular profiling may provide prognostic information worthy of validation in larger independent cohorts.
- Ki-67 index and galectin-3 as surrogate markers for predicting disease-free survival in luminal-type breast carcinoma treated with neoadjuvant chemotherapy
- Ho-Chang Lee, Wonshik Han, Seock-Ah Im, In Ae Park
- J Pathol Transl Med. 2026;60(5):539-548. Published online September 11, 2026
- DOI: https://doi.org/10.4132/jptm.2026.06.22

- 1,663 View
- 34 Download
-
Abstract
PDFSupplementary Material
- Background
Residual cancer burden (RCB) is an important marker for patients with breast carcinoma treated with neoadjuvant chemotherapy (NACT). However, the association between RCB and prognosis is relatively less significant in residual luminal-type breast carcinoma (LTBC). Associations between clinicopathological variables, including RCB class, and immunohistochemical (IHC) markers with disease-free survival (DFS) were analyzed. Methods: Expression of Ki-67, calreticulin, clusterin, galectin-3, mucin-1, and p27 was assessed in tissue microarray slides of 55 post-NACT resection specimens from LTBC patients treated with docetaxel and doxorubicin. Patients’ age, pre-NACT progesterone receptor status, lymphovascular invasion, histologic grade, ypT category, ypN category, RCB class, and IHC markers were analyzed for their association with DFS using Kaplan-Meier analysis and Cox proportional hazards models. Results: Twenty of the 55 patients developed recurrence or distant metastasis. A Ki-67 index > 2.7% and high galectin-3 expression were associated with shorter DFS on Kaplan-Meier analysis (p < .001 and p = .018, respectively). Other clinicopathological and IHC markers were not significantly associated with DFS. In the multivariate Cox proportional hazards model, a Ki-67 index > 2.7% (hazard ratio, 7.23; p < .001) and high galectin-3 expression (hazard ratio, 4.51; p = .007) remained independent predictors of shorter DFS. Conclusions: The Ki-67 index and high galectin-3 expression in post-NACT resection specimens may serve as surrogate markers for predicting recurrence in LTBC.
Review Article
- Obesity-driven adipokine signaling in breast cancer: mechanistic insights, therapeutic challenges, and opportunities for precision oncology
- Vadakke Kunnumma Soonu, Praveen Kumar Shenoy, Valiyaparampil Gopi Deepak Roshan, Vipin Gopinath, Krishnan Sreejith
- J Pathol Transl Med. 2026;60(5):476-492. Published online September 9, 2026
- DOI: https://doi.org/10.4132/jptm.2026.06.30
- 2,465 View
- 37 Download
- 1 Crossref
-
Abstract
PDF
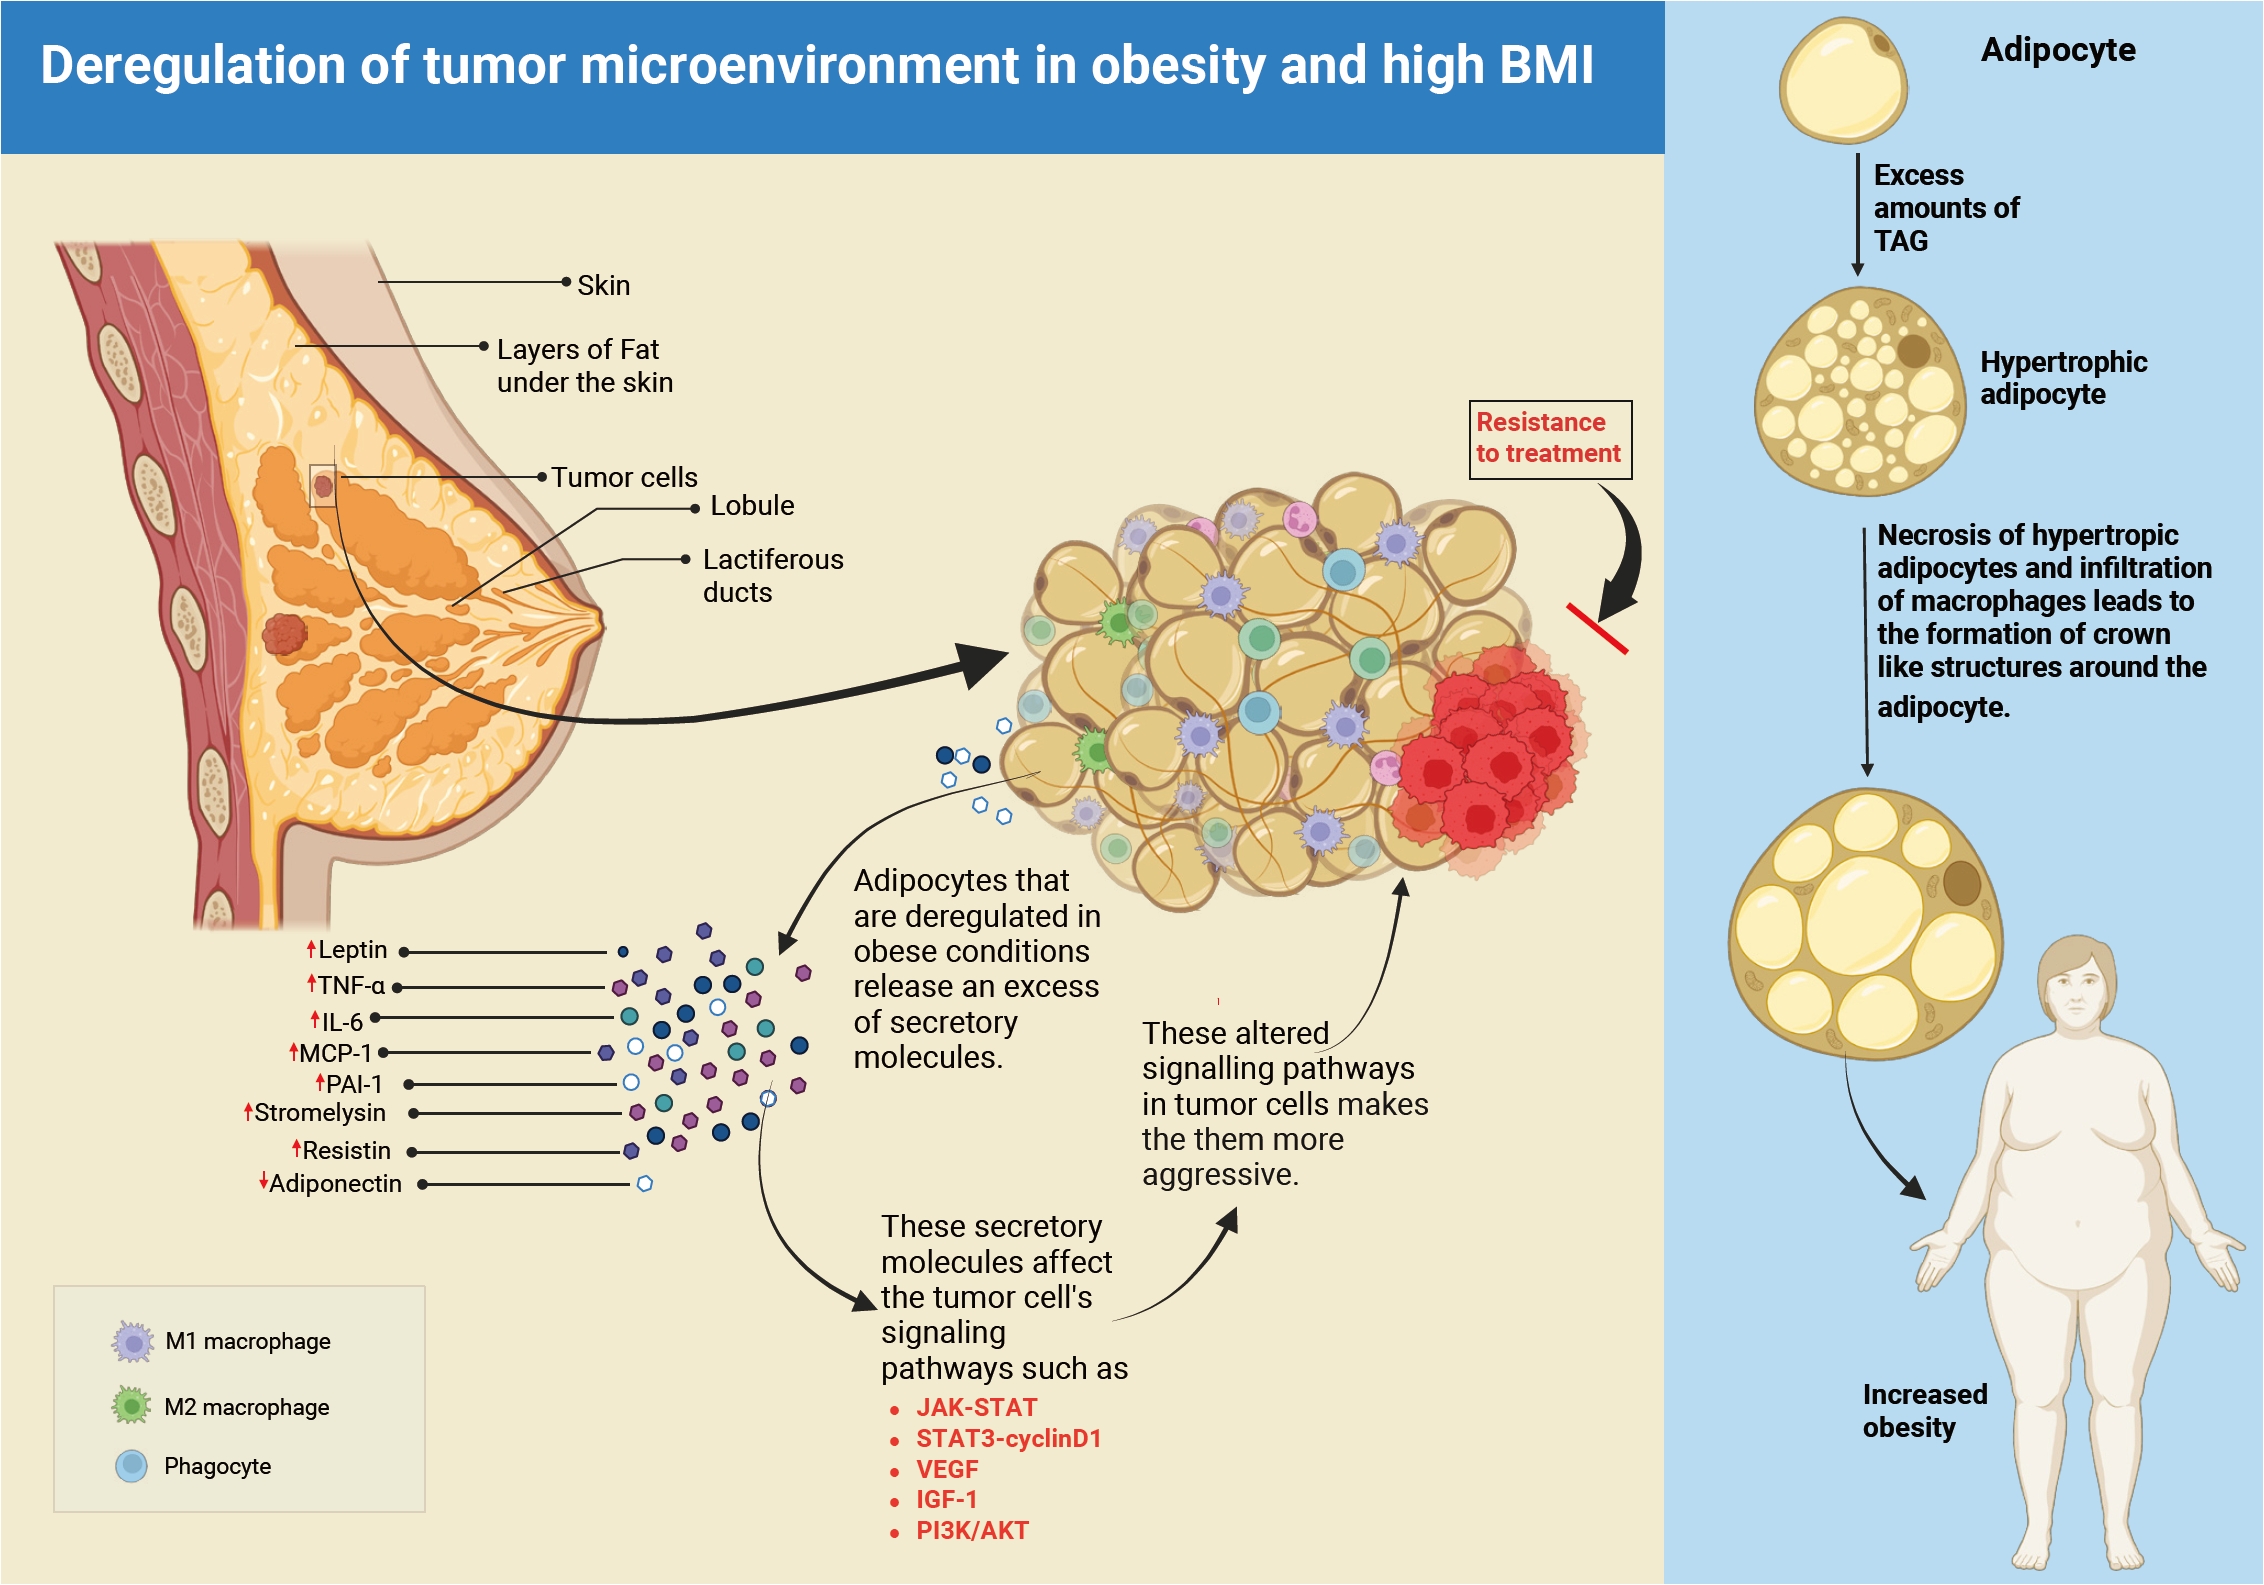
- Breast cancer is the leading cause of illness and death among women worldwide, with more than 2.3 million new cases diagnosed each year. The incidence and fatality rates are steadily increasing, notably in Asian countries. Obesity has been established as a major and growing risk factor for breast cancer progression. The World Health Organization reports that adult obesity rates have doubled since 1990. Obesity promotes tumor growth by inhibiting adipokine production and activating cancer-promoting pathways. In obese people, the microenvironment surrounding breast cancer cells is drastically altered. This is mostly due to the malfunctioning of adipocytes (fat cells) and macrophages. These defective cells' adipokines alter signaling pathways required for cancer cell proliferation, survival, and inflammation. This dysregulation has a significant role in tumor development, metastasis, and resistance to traditional cancer treatments, particularly in obese patients. This review highlights the role of adipokines in breast cancer, with a focus on disease progression, therapeutic challenges, and knowledge gaps. Clarifying how obesity alters tumor biology is key to advancing personalized and effective treatments for obese patients.
-
Citations
Citations to this article as recorded by- Cervical and Breast Cancer: Uncontrolled Epithelial Growth Driven by Xenoestrogen Dominance, Disrupted Paracrine Signaling, and Arrested Apoptosis
Albert Despot, Ivan Sabol, Zlatko Hrgović, Ana-Marija Despot, Ivica Vlatkovic, Mara Tešanović, Dora Fureš, Sanja Malinac Malojčić, Vesna Ćosić, Nikola Sinković, Rajko Fureš
Cells.2026; 15(21): 1956. CrossRef
- Cervical and Breast Cancer: Uncontrolled Epithelial Growth Driven by Xenoestrogen Dominance, Disrupted Paracrine Signaling, and Arrested Apoptosis
Case Study
- Gastric amphicrine carcinoma in the stomach: an unexpected presentation of MUTYH-associated polyposis
- Seungkyun Lee, Byung-Hoon Min, Young-Gon Kim, Soomin Ahn, Kyoung-Mee Kim
- J Pathol Transl Med. 2026;60(6):693-697. Published online September 7, 2026
- DOI: https://doi.org/10.4132/jptm.2026.06.24
- 1,449 View
- 17 Download
-
Abstract
PDF
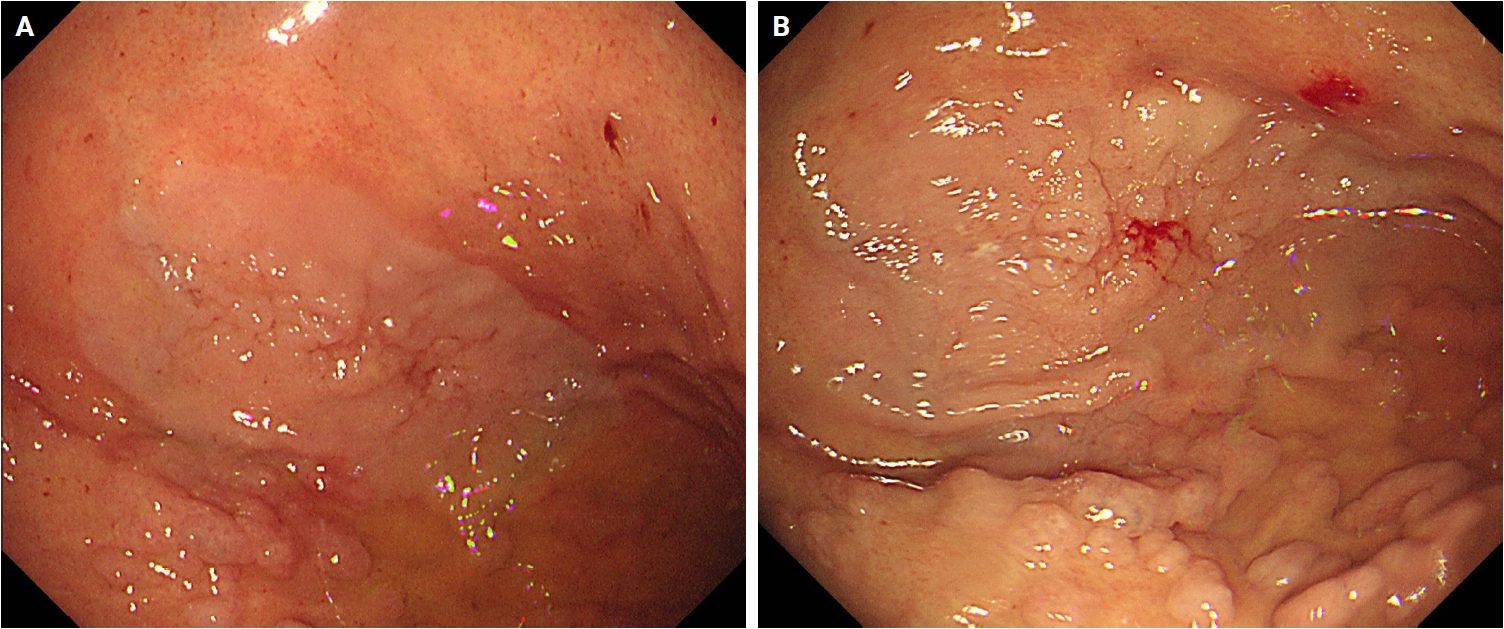
- Amphicrine carcinomas of the stomach, defined by dual exocrine and neuroendocrine differentiation within the same neoplastic cell, are exceedingly rare. MUTYH-associated polyposis (MAP) is an autosomal recessive polyposis syndrome characterized by multiple colorectal adenomas and variable upper gastrointestinal involvement; however, amphicrine carcinomas have not been previously documented in this setting. We report a gastric amphicrine carcinoma arising in the background of extensive fundic gland polyposis in a patient with MAP. Endoscopy revealed a 3.5-cm flat elevated lesion in the gastric fundus amid extensive fundic gland polyposis. Histologically, the tumor consisted of a single population of cells exhibiting combined glandular and neuroendocrine differentiation without zonal or biphasic architecture, and many of these cells demonstrated true amphicrine morphology. Immunohistochemistry confirmed co-expression of cytokeratin and the neuroendocrine markers chromogranin A and synaptophysin in the same cell population. Germline targeted next-generation sequencing identified biallelic MUTYH variants in trans (c.733C>T, p.Arg245Cys [likely pathogenic]; c.842C>T, p.Ala281Val [variant of uncertain significance]), supporting a diagnosis of MAP. To our knowledge, this is the first reported case of a gastric amphicrine carcinoma in a MAP patient, expanding the spectrum of MAP-associated upper gastrointestinal neoplasia and underscoring the importance of vigilant endoscopic surveillance in hereditary polyposis syndromes.
Review Article
- Sentinel lymph node biopsy in melanoma: pathologic evaluation and diagnostic considerations
- Dre Barnachea, Bonnie Lee
- J Pathol Transl Med. 2026;60(5):493-501. Published online September 1, 2026
- DOI: https://doi.org/10.4132/jptm.2026.07.01

- 3,092 View
- 76 Download
-
Abstract
PDF
- Sentinel lymph node biopsy (SLNB) is a widely used staging procedure in melanoma that provides important prognostic information and guides clinical management. The sentinel lymph node (SLN), defined as the first lymph node in the lymphatic drainage pathway from a primary tumor, represents the most likely site of early regional metastasis. Accordingly, identification of metastatic melanoma within SLNs has significant implications for staging and risk stratification and is associated with worse clinical outcomes. The SLNB procedure involves preoperative and intraoperative lymphatic mapping techniques, including radiotracer localization with or without blue dye injection, which allow identification of SLNs. Histopathologic evaluation includes careful gross examination, serial sectioning, and immunohistochemical analysis using melanocytic markers such as SOX10, Melan-A, HMB45, and occasionally PRAME to detect metastatic disease. In addition, prognostic features such as tumor burden, extranodal extension, and microanatomic location of metastases within the lymph node further refine risk assessment. This review provides an overview of SLNB in melanoma, with emphasis on clinical indications, histopathologic evaluation, and key diagnostic and prognostic considerations.
Case Studies
- Ultrasound-guided cryoablation of recurrent thyroid cancer: radiologic-pathologic correlation
- Yeseul Kim, Jae Ho Shin, Kyeong Jin Kim, Soo Myoung Shin, Dawon Park
- J Pathol Transl Med. 2026;60(6):687-692. Published online August 3, 2026
- DOI: https://doi.org/10.4132/jptm.2026.06.04
- 1,772 View
- 51 Download
-
Abstract
PDFSupplementary Material
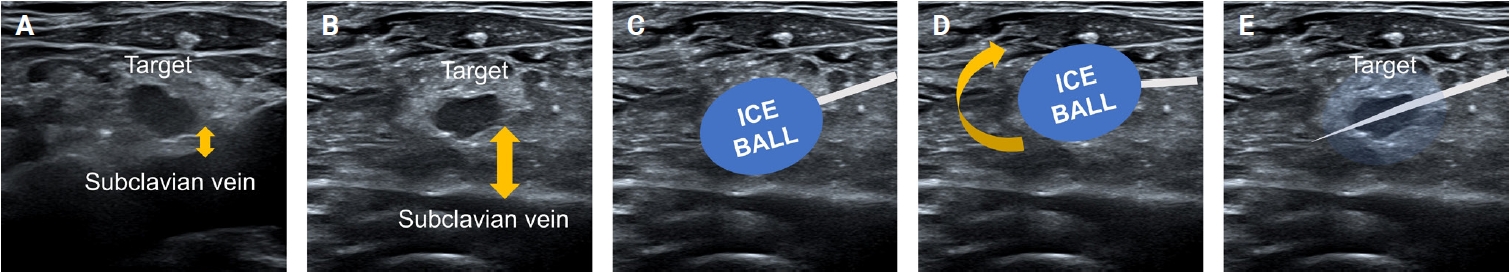
- Cryoablation is a minimally invasive thermal ablation modality that destroys tumor cells through intracellular ice crystal formation and osmotic injury. Although it offers theoretical advantages, its application in recurrent papillary thyroid cancer (PTC) remains limited, and the radiologic-pathologic findings of treatment response have not been well characterized. A 55-year-old male patient with biopsy-proven recurrent PTC in the left supraclavicular fossa and a history of total thyroidectomy, neck dissection, and advanced colorectal cancer underwent a single-session ultrasound-guided cryoablation. The 20-minute procedure was completed without complications. Immediately post-ablation, the lesion volume increased by over 200% with marked hypoechogenicity and obliteration of abnormal feeding vessels on microvascular imaging. Pathology demonstrated disrupted tumor cell membranes, necrotic changes, and myxoid peritumoral stromal alteration, consistent with direct and indirect injuries caused by cryoablation. At the first-month follow-up, repeat biopsy showed no viable tumor, with subacute inflammatory infiltrates, histiocytic aggregates, and progressive fibrosis. On ultrasound, a volume reduction rate of 71.4% was achieved at one month follow-up and 97.1% at three months follow-up. This case report provides the first radiologic-pathologic findings of both immediate and delayed effects of cryoablation in recurrent PTC, supporting its role as a promising minimally invasive palliative therapy.
- Fibrosarcoma of bone masquerading as fibrous dysplasia: diagnostic pitfall and molecular correlates of aggressive behavior
- Wangpan J. Shi, Brady K. Huang, Li Lei
- J Pathol Transl Med. 2026;60(5):578-586. Published online August 3, 2026
- DOI: https://doi.org/10.4132/jptm.2026.05.29
- 1,792 View
- 42 Download
-
Abstract
PDFSupplementary Material
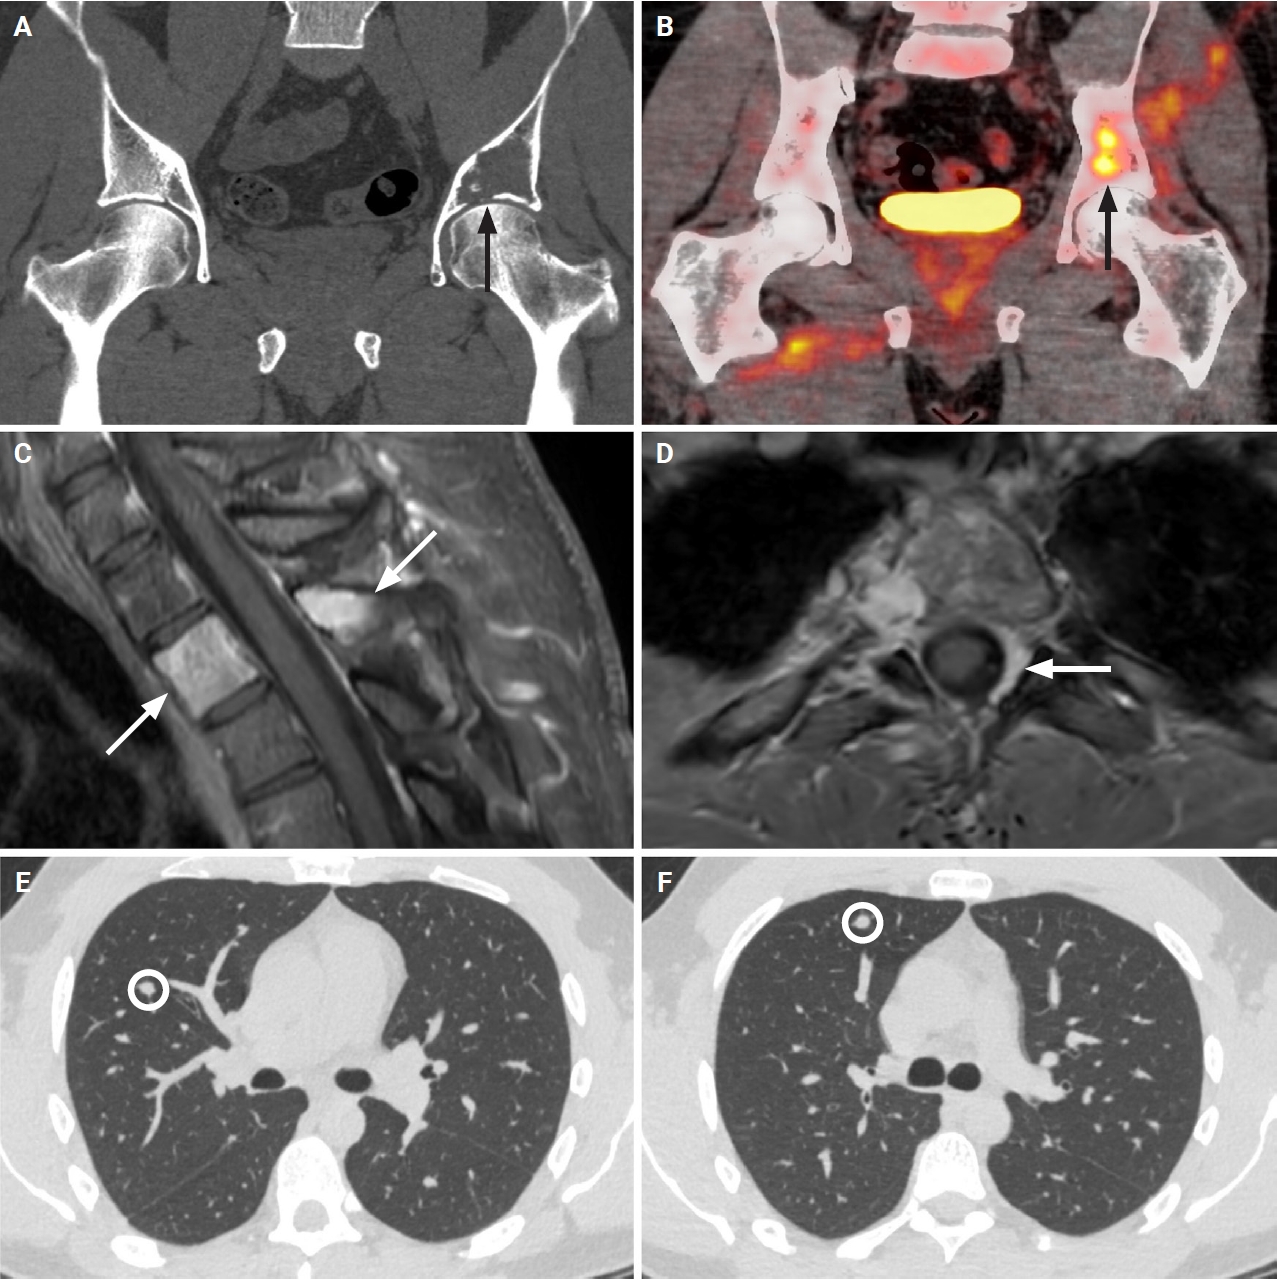
- Low-grade fibro-osseous lesions can be challenging to classify. A 33-year-old man presented with synchronous lesions involving the ilium and T2 vertebra. Because of an impending pathologic fracture, he received several doses of denosumab. Initial biopsies showed bland fibro-osseous lesions lacking GNAS or MDM2 alterations and were favored to represent polyostotic fibrous dysplasia. Subsequent iliac curettage revealed a fascicular spindle cell proliferation with subtle atypia and focal ossification, leading to a revised diagnosis of low-grade fibrosarcoma. Re-biopsy of the T2 lesion demonstrated a similar spindle cell proliferation without ossification. Sequencing identified copy number gains involving KIT, PDGFRA, and TERT. At 16-month follow-up, two metastatic pulmonary nodules developed, one responsive to chemotherapy. The patient remains alive with disease at 27 months after presentation. This case highlights a diagnostic pitfall in which low-grade fibrosarcoma with denosumab-associated ossification may mimic fibrous dysplasia and underscores the prognostic value of molecular profiling beyond histologic grading.
Original Article
- Development of a prognostic prediction model for tumor recurrence or progression in gastrointestinal stromal tumors: integrating inflammatory blood indices with 5 mm2 versus 50 high-power field mitotic counts
- Waratchaya Tirasarnvong, Thammasin Ingviya, Paramee Thongsuksai
- J Pathol Transl Med. 2026;60(5):527-538. Published online July 31, 2026
- DOI: https://doi.org/10.4132/jptm.2026.06.15
- 2,451 View
- 35 Download
-
Abstract
PDFSupplementary Material
- Background
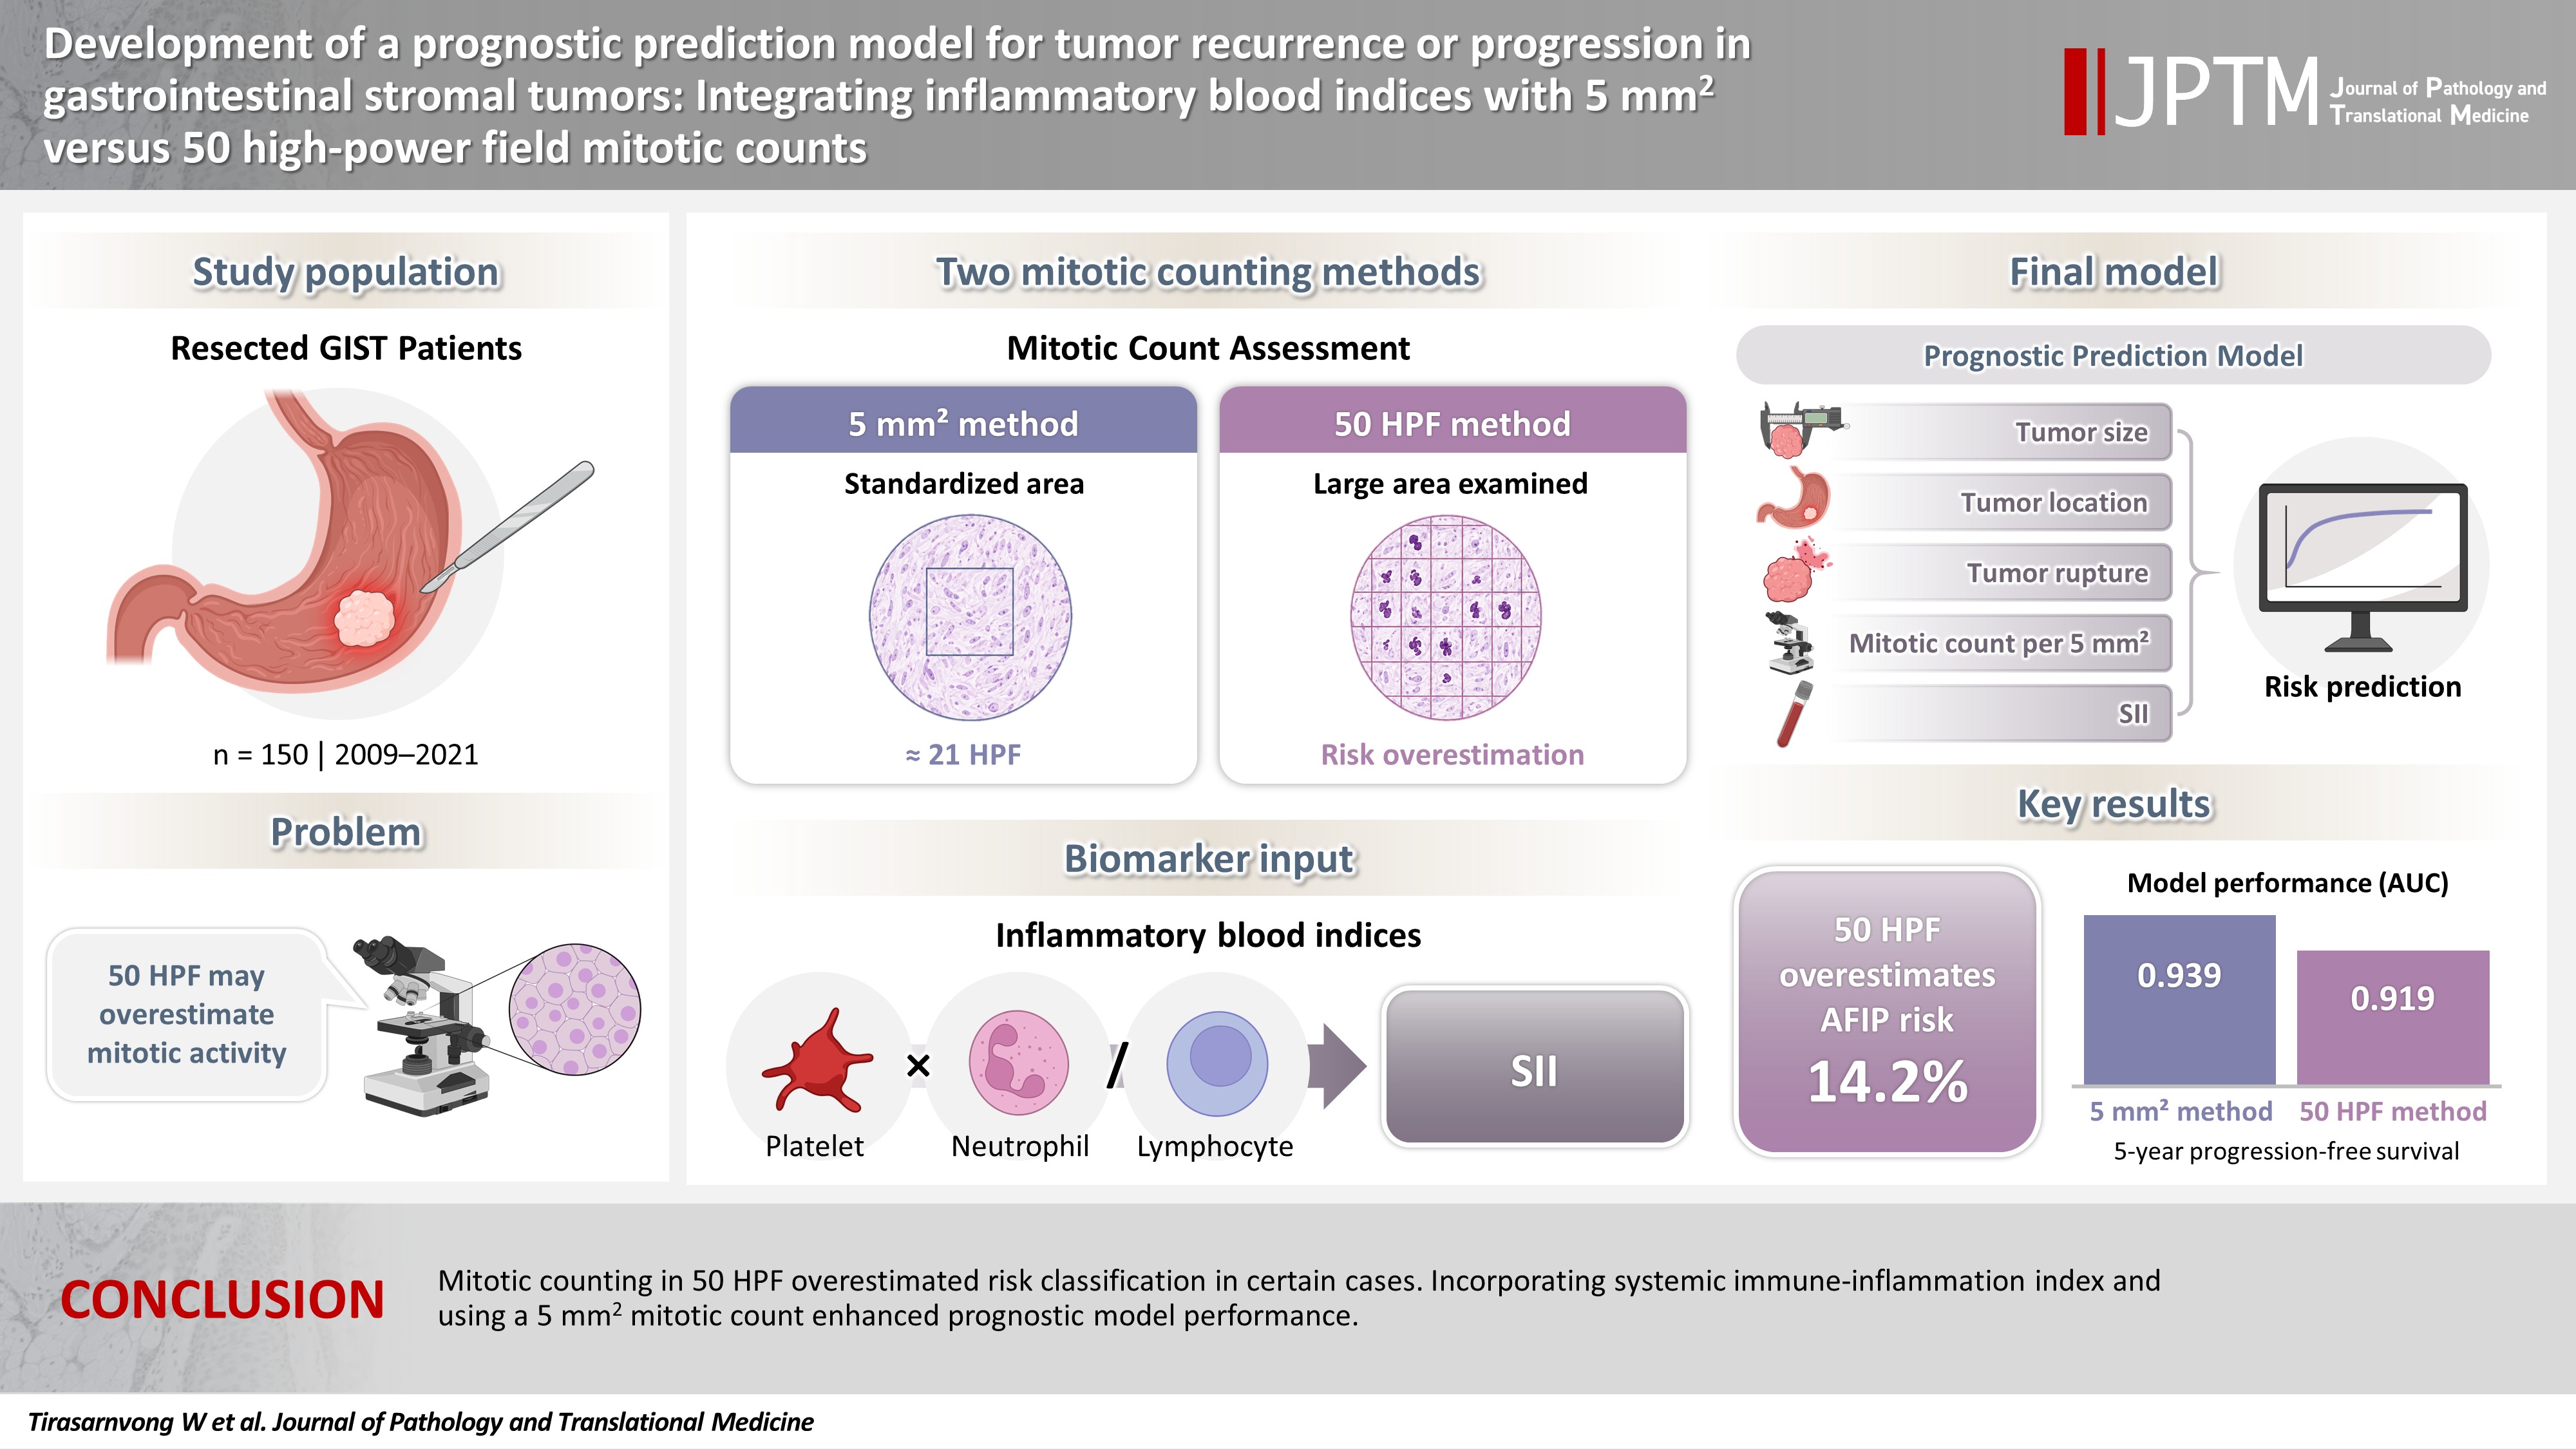
The behavior of gastrointestinal stromal tumors varies according to tumor size, location, mitotic rate, and rupture. Traditional mitotic counting in 50 high-power fields (HPF; 5.3 mm2) may overestimate progression risk, as 5 mm2 corresponds to 20–25 HPF under modern microscopy. However, the 50-HPF method remains widely used. This study evaluated the impact of two mitotic counting methods on risk classification and developed a prognostic model combining inflammatory biomarkers with clinicopathological factors. Methods: We retrospectively analyzed 150 patients who underwent resection at Songklanagarind Hospital between 2009 and 2021. Patients who had received neoadjuvant therapy or had a second primary cancer were excluded. Mitosis was evaluated using both methods. Clinicopathological and serum biomarker data were collected. The primary outcome was 5-year disease-free or progression-free survival. The model was developed using forward stepwise variable selection based on the time-dependent area under the curve and internally validated by bootstrapping. Results: The 50-HPF method overestimated the Armed Forces Institute of Pathology classification in 14.2% of cases. A model incorporating tumor size, location, rupture, mitotic count within 5 mm2, and systemic immune-inflammation index achieved the highest area under the curve of 0.939 in both training and validation sets, outperforming previous models. The 5-mm2 method demonstrated superior performance to the 50-HPF method across all models (0.939 vs. 0.919 for the proposed model). Conclusions: Mitotic counting in 50 HPF overestimated risk classification in certain cases. Incorporating systemic immune-inflammation index and using a 5 mm2 mitotic count enhanced prognostic model performance.
Case Study
- Clinicopathological characteristics of primary malignant cutaneous perivascular epithelioid cell tumor: case report and literature review
- Huaming Li, Dan Zhang, Shiwu Zhang
- J Pathol Transl Med. 2026;60(5):572-577. Published online July 20, 2026
- DOI: https://doi.org/10.4132/jptm.2026.05.10
- 2,531 View
- 43 Download
-
Abstract
PDF
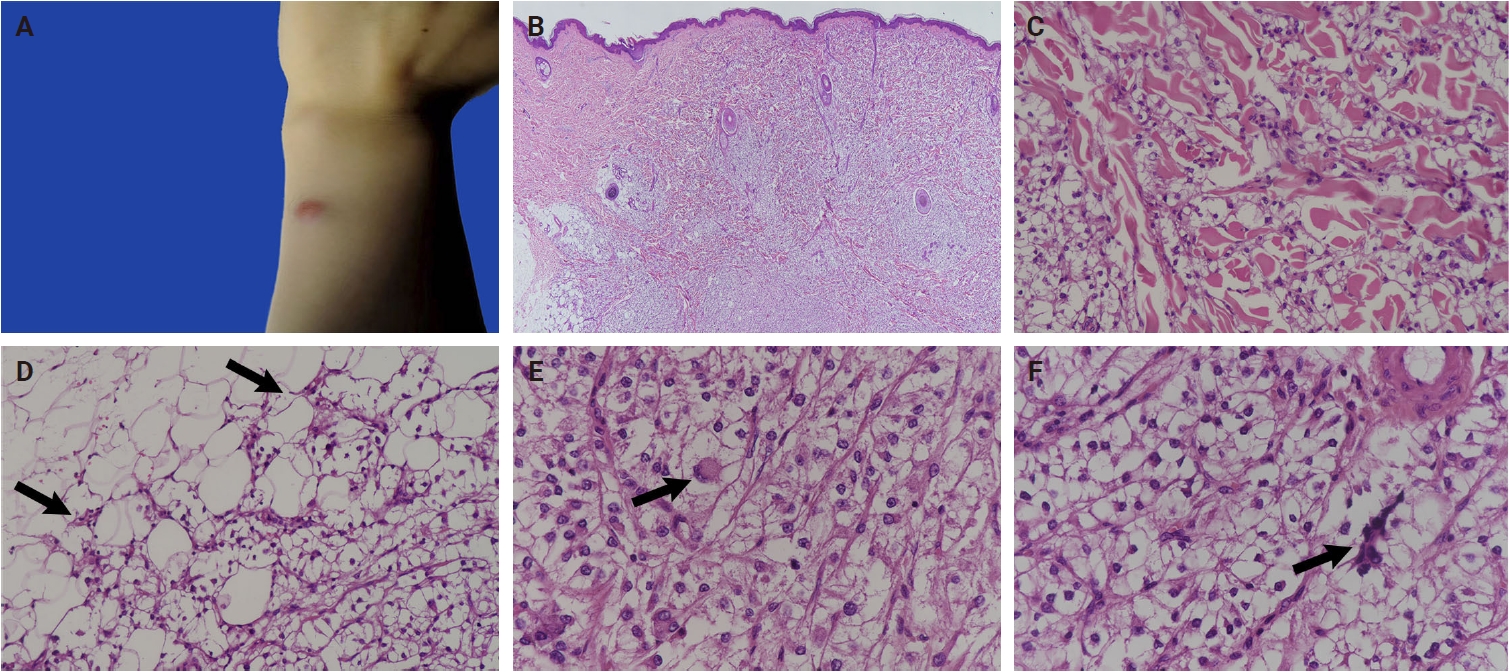
- Primary cutaneous malignant perivascular epithelioid cell tumors (PEComas) are extremely rare. Accurate diagnosis is critical for prognostic evaluation and guiding clinical management. Here, we report a case of a 19-year-old woman with a 1.1 cm exophytic red mass on her left upper limb. Histological examination revealed a dermal tumor composed of clear cells with prominent nucleoli. The tumor cells displayed cytologic atypia, nuclear pleomorphism, multinucleated giant cells, mitoses and invasive growth, with a multinodular distribution within the dermis and vascular invasion. Immunohistochemically, the tumor cells expressed cathepsin K, HMB45, and CD10. Based on morphological and immunohistochemical findings, we classified it as a primary malignant cutaneous PEComa. To date, only eight reported cases have been described as primary malignant cutaneous PEComas. The present case appears to be the youngest patient reported among all malignant PEComas.
Original Article
- Bronchial lesions in a high serum IgA mouse model: pulmonary venular IgA deposition and spatially distinct lymphoid cell aggregation
- Areum Kim, Minhyeok Lee, Yohan Park, Wan Jin Hwang, Hyeseung Lee, Joo Heon Kim, Jin Man Kim, Yong Min Kim, Jin Sun Park, Junguee Lee
- J Pathol Transl Med. 2026;60(5):516-526. Published online July 16, 2026
- DOI: https://doi.org/10.4132/jptm.2026.06.01
- 2,697 View
- 39 Download
-
Abstract
PDF
- Background
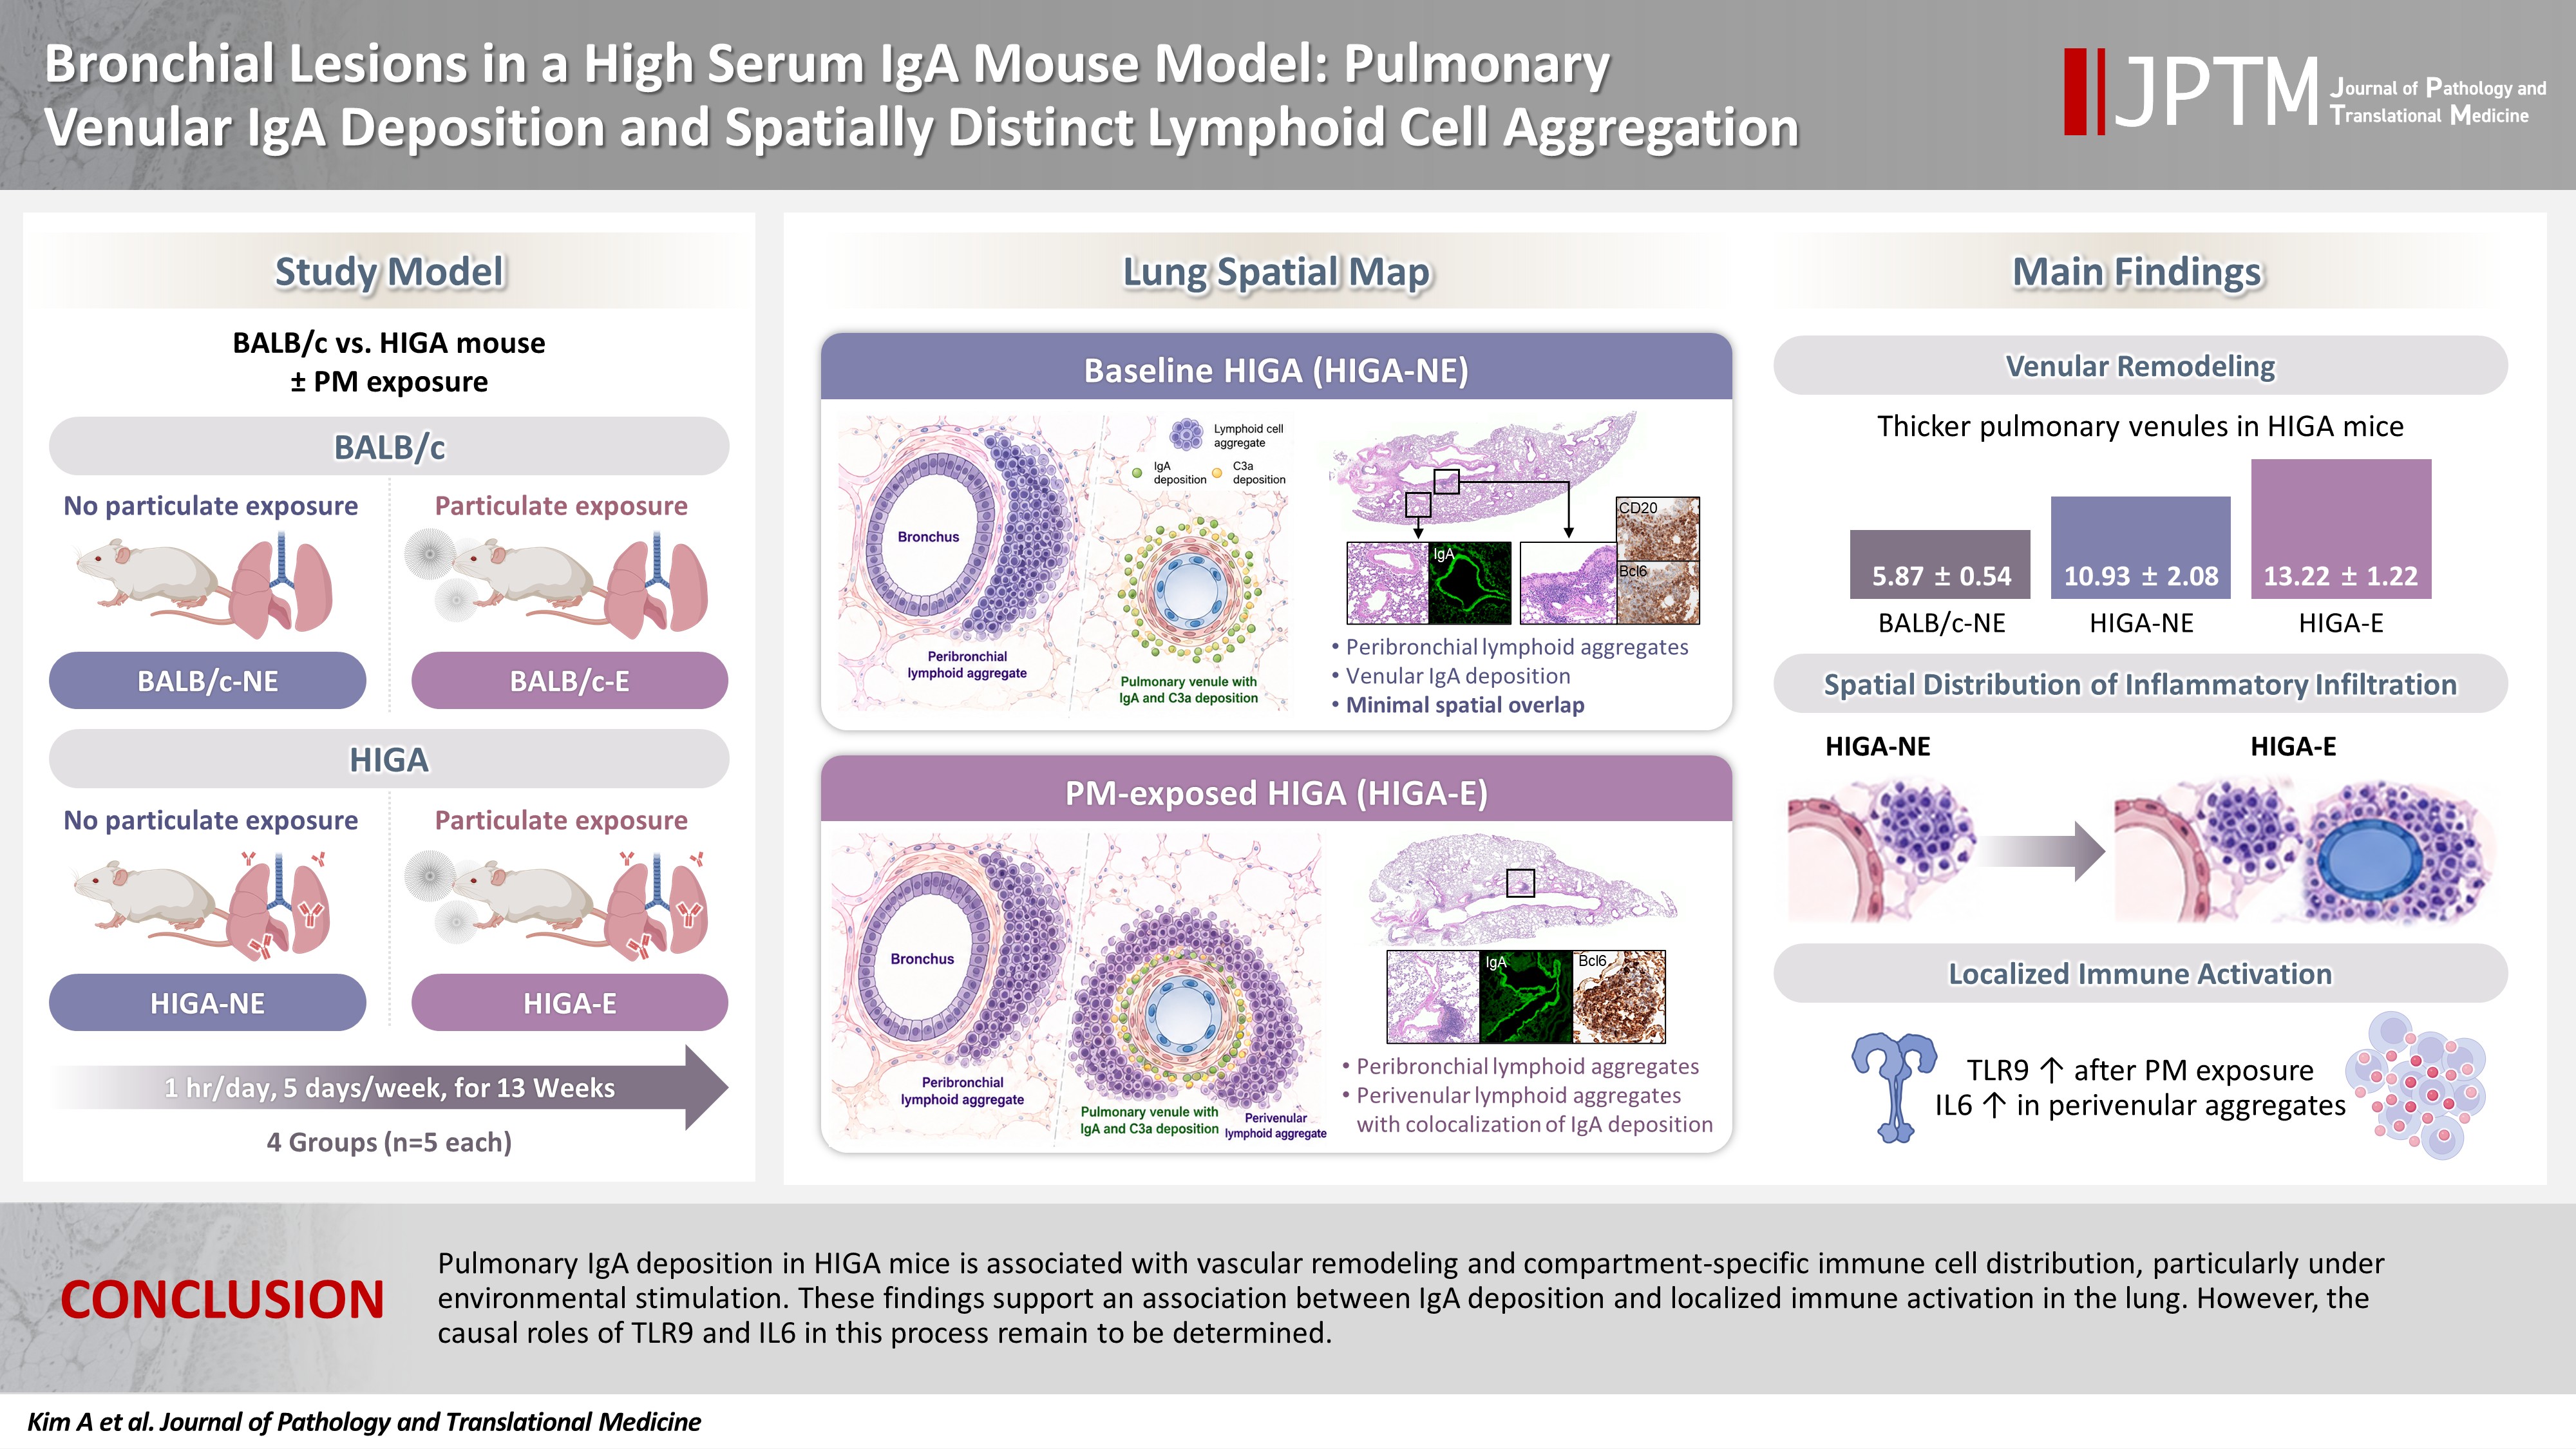
Immunoglobulin A (IgA) nephropathy is a systemic immune complex–mediated disease primarily affecting the kidneys, yet pulmonary involvement remains poorly characterized. This study investigated pulmonary structural alterations, IgA deposition, immune cell distribution, and the impact of chronic environmental immune stimulation. Methods: High-IgA (HIGA) mice and BALB/c controls were examined under baseline conditions and following chronic particulate matter (PM) exposure. Histopathology, immunofluorescence, immunohistochemistry, and lectin-based assays were used to assess pulmonary IgA deposition, lymphoid cell aggregation, and immune activation. Results: Compared with BALB/c controls, HIGA mice exhibited pulmonary venular remodeling characterized by thickening of the venular tunica media and IgA deposition within the smooth muscle layer. Under baseline conditions, lymphoid cell aggregation in HIGA mice was predominantly localized to peribronchial regions, whereas IgA deposition and C3a deposition were confined to pulmonary venules with minimal spatial overlap. Following PM exposure, HIGA mice developed additional perivenular lymphoid cell aggregation that spatially corresponded with IgA deposition, whereas BALB/c mice showed predominantly peribronchial aggregation. PM exposure was associated with increased pulmonary Toll-like receptor 9 (TLR9) expression in both strains. In HIGA mice, TLR9-positive immune cells and interleukin-6 (IL6) expression were enriched in perivenular lymphoid cell aggregates. Conclusions: Pulmonary IgA deposition in HIGA mice is associated with vascular remodeling and compartment-specific immune cell distribution, particularly under environmental stimulation. These findings support an association between IgA deposition and localized immune activation in the lung. However, the causal roles of TLR9 and IL6 in this process remain to be determined.
Review Article
- Lymphomatoid papulosis: a practical review for pathologists
- Mario L. Marques-Piubelli, Carlos A. Torres-Cabala, Roberto N. Miranda
- J Pathol Transl Med. 2026;60(4):388-397. Published online July 15, 2026
- DOI: https://doi.org/10.4132/jptm.2026.06.09
- 3,006 View
- 101 Download
-
Abstract
PDF
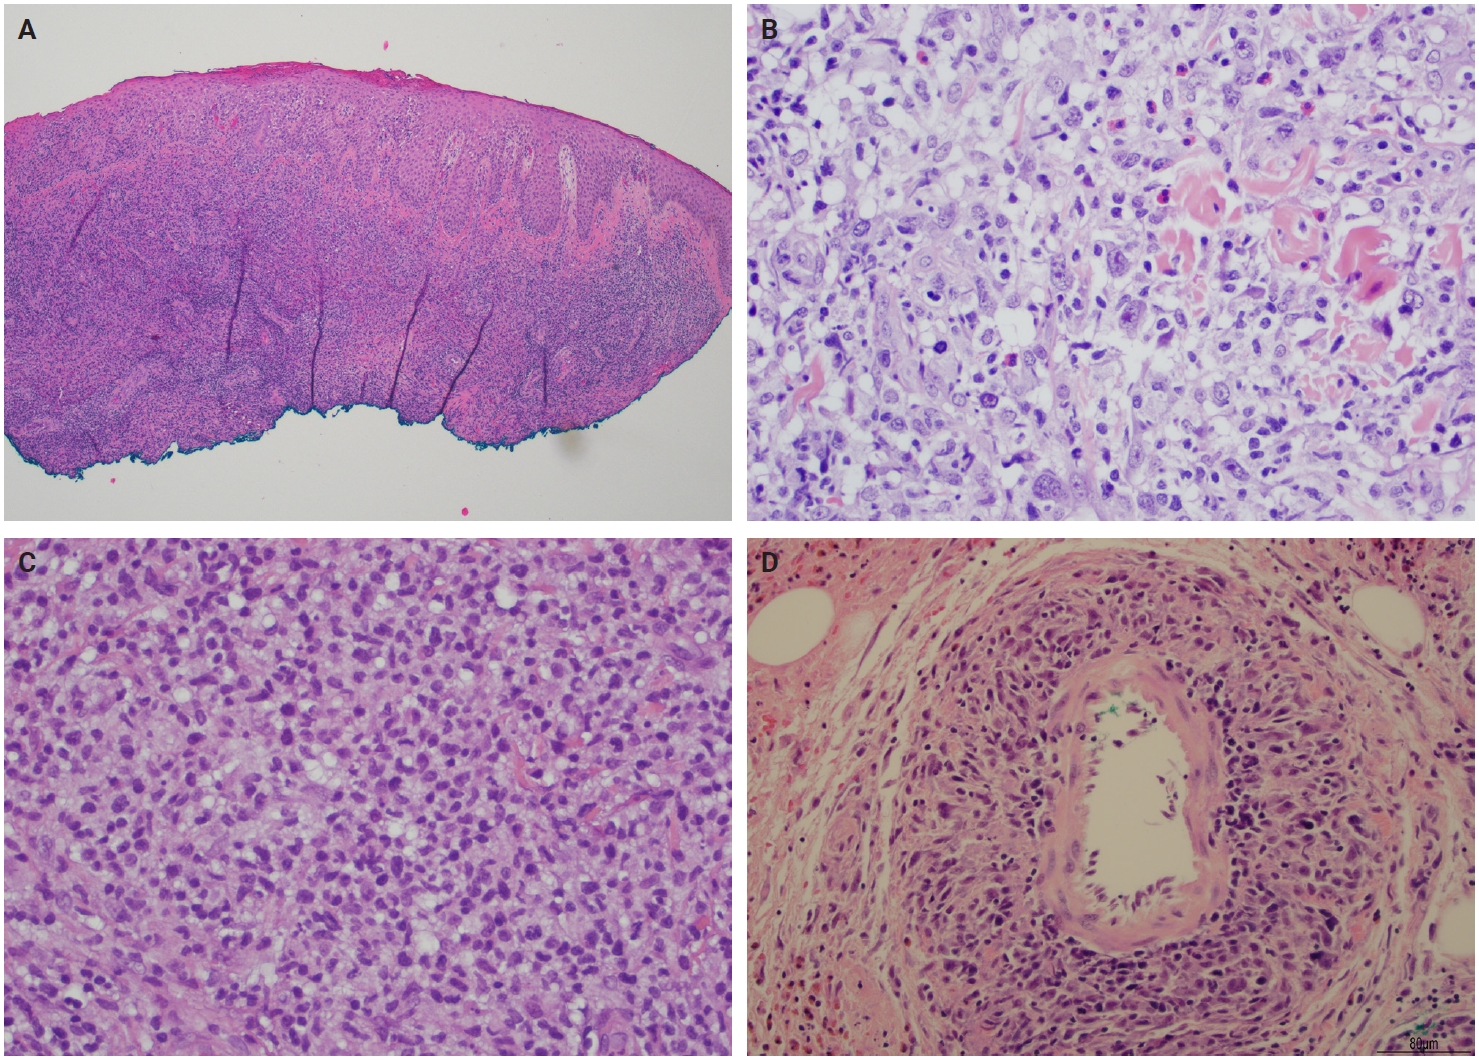
- Lymphomatoid papulosis (LyP) is a primary cutaneous CD30+ lymphoproliferative disorder characterized by a chronic and self-healing recurrent cluster of erythematous papules or nodules on the skin of the trunk and/or extremities. The disease has an indolent clinical course with spontaneous regression or waxing and waning clinical evolution. The histopathologic spectrum of LyP is vast and may show few to numerous atypical cells immersed in a mild to intense inflammatory background. The backbone for the diagnosis is the positivity for CD30, which is one of the criteria to define this group of lymphoproliferative disorders. The association of these different histological and immunophenotypical findings is used to subclassify this disease in different subtypes from A to E, associated with DUSP22/IRF4 rearrangement, and other rare forms. Although this differentiation is important to raise awareness of different differential diagnosis, it does not impact the prognosis or change the treatment, which is usually centered in symptom relief and faster regression. In this review, we aim to summarize the most updated information of the clinical, histopathological, and molecular characteristics of LyP and provide a practical assessment for the diagnostic features that could help with the main differential diagnosis.
Original Article
- Hyalinizing trabecular tumors with areas resembling noninvasive follicular thyroid neoplasm with papillary‑like nuclear features: an immunohistochemical and molecular analysis
- Risa Kanematsu, Mitsuyoshi Hirokawa, Ayana Suzuki, Miyoko Higuchi, Satomi Usuki, Hiroshi Kamma, Takashi Akamizu
- J Pathol Transl Med. 2026;60(4):436-443. Published online July 15, 2026
- DOI: https://doi.org/10.4132/jptm.2026.06.07
- 2,862 View
- 80 Download
-
Abstract
PDF
- Background
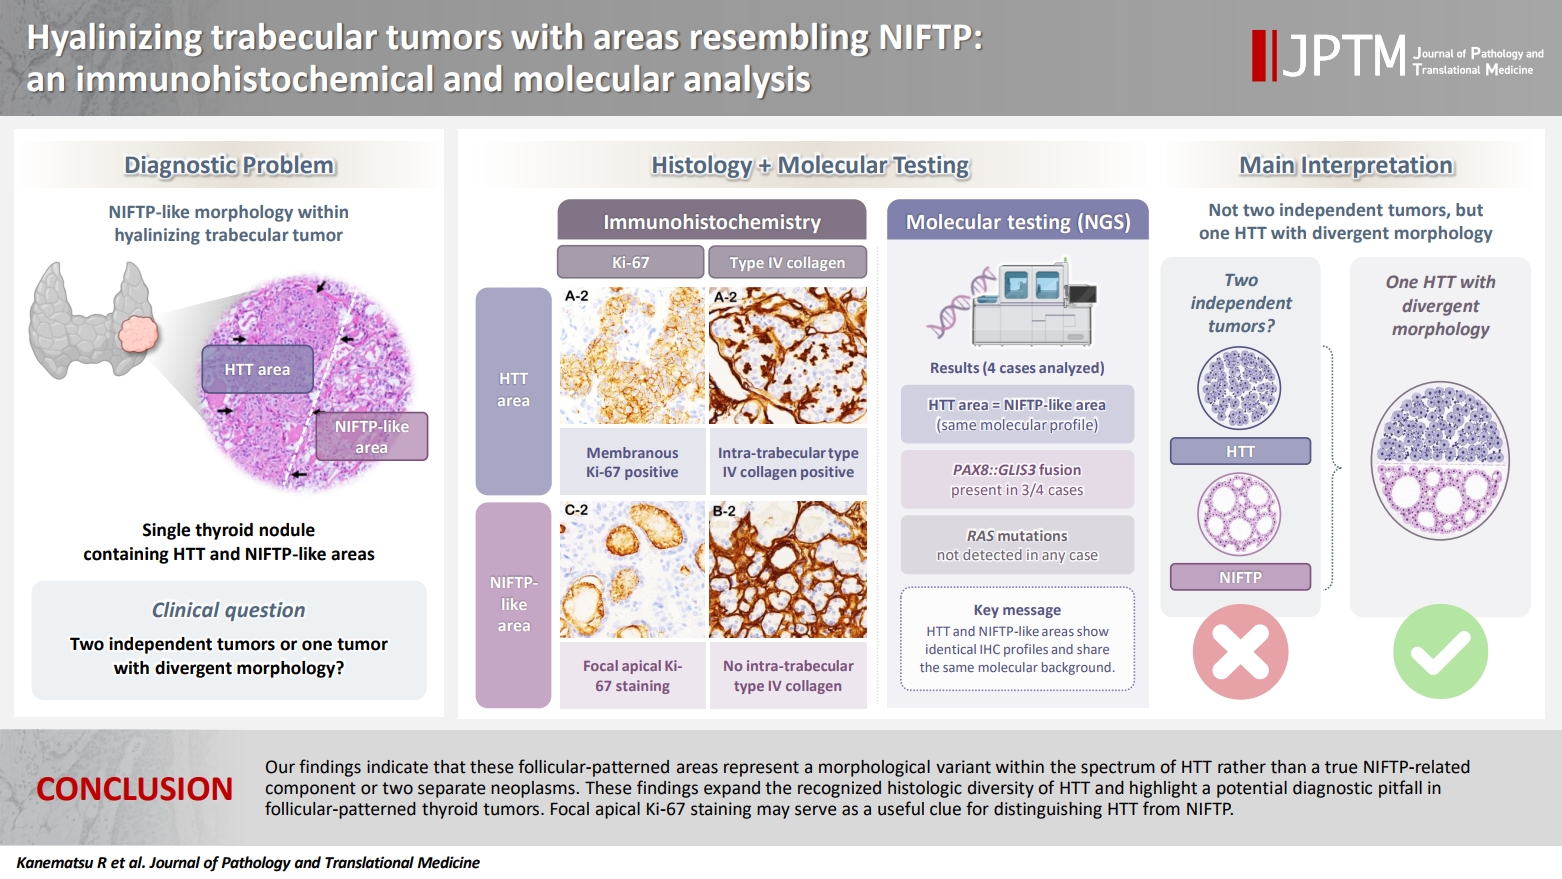
The coexistence of hyalinizing trabecular tumor (HTT) and areas with a morphology of noninvasive follicular thyroid neoplasm with papillary-like nuclear features (NIFTP) within a single thyroid nodule has not been previously reported. We aimed to determine whether such tumors represent two independent neoplasms or a single tumor exhibiting divergent morphology. Methods: Ten tumors containing both HTT and NIFTP-like areas were examined. The term “NIFTP-like” was used strictly as a descriptive morphological designation for areas that fulfill the histologic criteria of NIFTP. Immunohistochemical analyses of Ki-67 (MIB-1) and type IV collagen and targeted molecular testing were performed. Ten NIFTPs, 10 follicular adenomas, and three HTTs were used as controls. Results: HTT components consistently showed characteristic membranous Ki-67 staining and intra-trabecular type IV collagen deposition, whereas NIFTP-like areas lacked these features, except for focal apical Ki-67 staining. Intranuclear cytoplasmic inclusions in HTT were positive for type IV collagen. NIFTPs showed neither membranous Ki-67 nor intra-trabecular type IV collagen. Molecular analysis demonstrated identical profiles between HTT components and NIFTP-like areas: three tumors harbored PAX8::GLIS3 fusions, and none showed RAS mutations. Pure HTT controls exhibited the same pattern. Conclusions: Our findings indicate that these follicular-patterned areas represent a morphological variant within the spectrum of HTT rather than a true NIFTP-related component or two separate neoplasms. These findings expand the recognized histologic diversity of HTT and highlight a potential diagnostic pitfall in follicular-patterned thyroid tumors. Focal apical Ki-67 staining may serve as a useful clue for distinguishing HTT from NIFTP.
Review Articles
- Ganglioglioma and gangliocytoma: a review for pathologists
- Gianfranco E. Umeres-Francia, Melissa Mejia-Bautista, Pouya Jamshidi, Jared T. Ahrendsen
- J Pathol Transl Med. 2026;60(4):379-387. Published online July 15, 2026
- DOI: https://doi.org/10.4132/jptm.2026.06.06
- 3,010 View
- 112 Download
-
Abstract
PDF
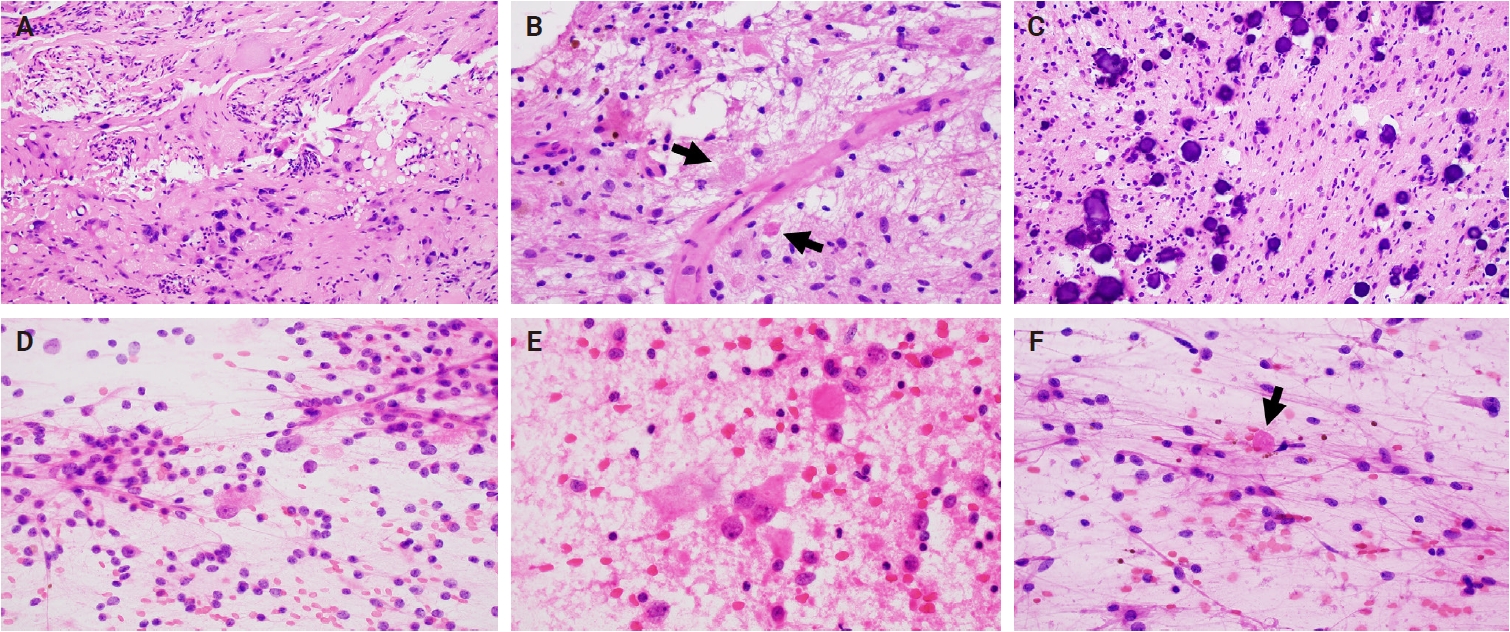
- Ganglioglioma and gangliocytoma are rare, predominantly low-grade neuroepithelial tumors that commonly present with epilepsy in children and young adults. Advances in molecular profiling have improved understanding of their pathogenesis, highlighting key roles for the mitogen-activated protein kinase/ERK signaling pathway. Diagnosis relies on a combination of clinical, radiologic, and histopathologic features, with complete surgical resection offering the best clinical outcomes. This review summarizes current knowledge on their epidemiology, etiology, clinical presentation, imaging characteristics, pathology, treatment strategies, and prognosis.
- Angiomatoid fibrous histiocytoma: a review
- Alexander N. Perez, Phyu P. Aung
- J Pathol Transl Med. 2026;60(4):371-378. Published online July 15, 2026
- DOI: https://doi.org/10.4132/jptm.2026.06.05
- 3,136 View
- 111 Download
- 1 Crossref
-
Abstract
PDF
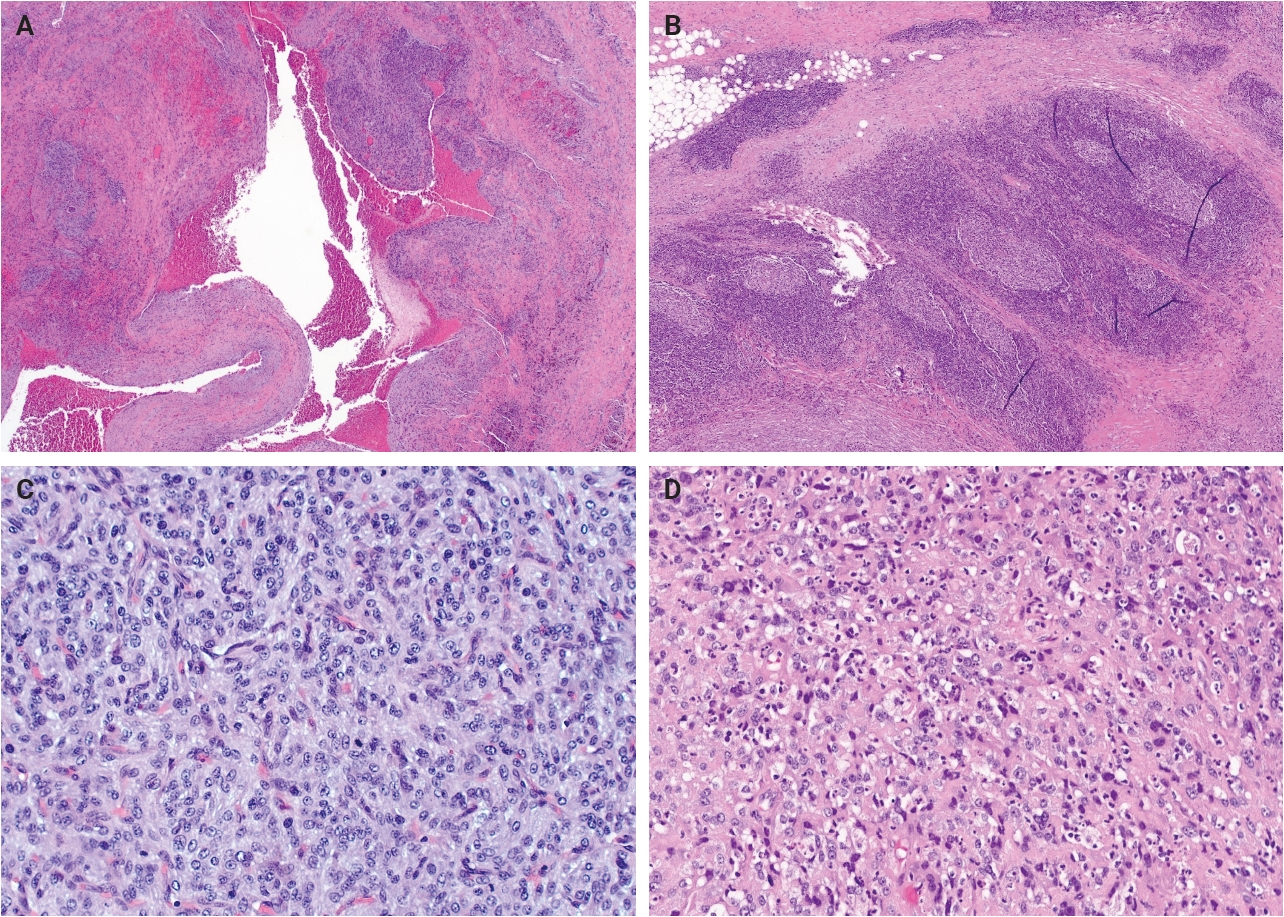
- Angiomatoid fibrous histiocytoma is a rare mesenchymal neoplasm of uncertain cell lineage with indeterminate behavior, hallmarked by EWSR1 translocations. This tumor typically arises in the subcutaneous or deep soft tissues and is composed of bland to mildly atypical histiocytoid cells with frequent intralesional hemorrhagic pseudocystic spaces. It affects both children and adults, without a significant sex predilection. Histologically, the tumor may be mistaken for a lymph node given the apparent predilection for node-bearing sites as well as the brisk lymphoid cuff featuring germinal centers. Surgical excision is often curative, with local recurrence occurring occasionally and metastasis only very rarely. A possible relationship to molecularly related entities arising primarily within the thoracic cavity and intracranial compartment has been proposed, although this association remains incompletely understood.
-
Citations
Citations to this article as recorded by- Angiomatoid Fibrous Histiocytoma: A Report of Two Cases and Review of the Literature
雨欣 谢
Advances in Clinical Medicine.2026; 16(11): 992. CrossRef
- Angiomatoid Fibrous Histiocytoma: A Report of Two Cases and Review of the Literature
Case Study
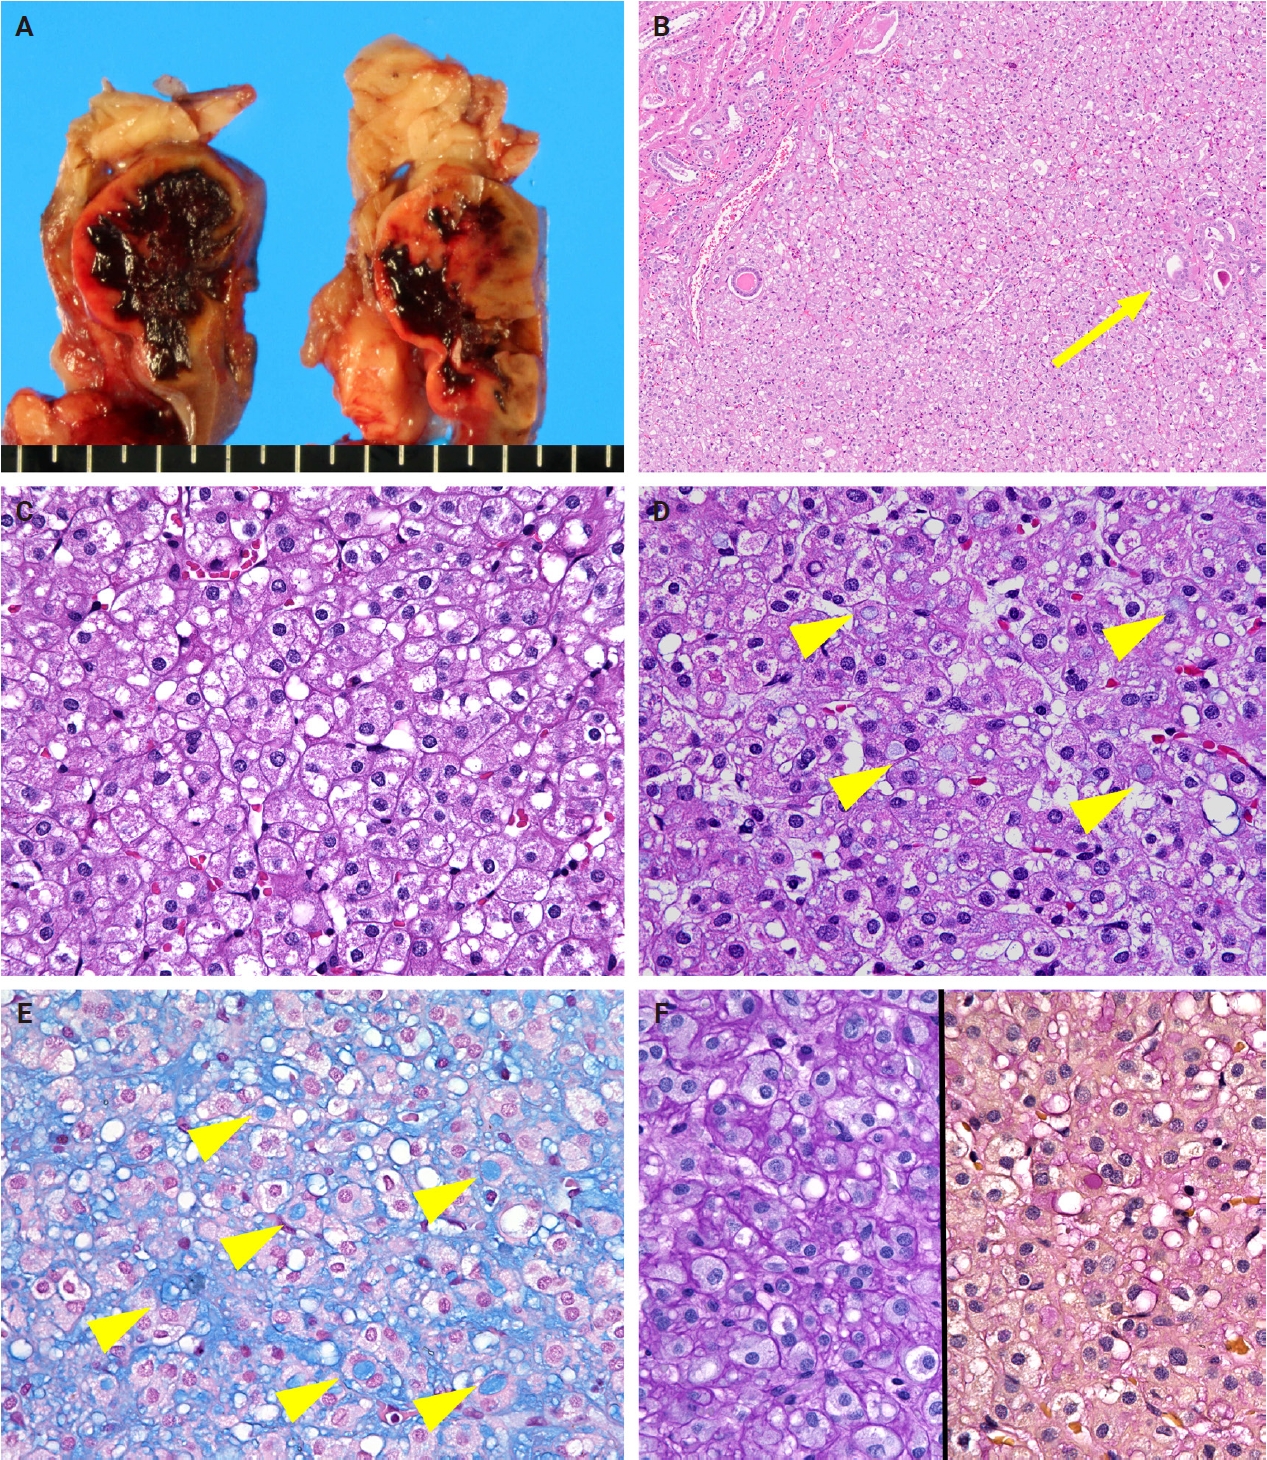
- SDH-deficient renal cell carcinoma with intracytoplasmic mucinous material: a case report and literature review
- Ryosuke Yoshioka, Kosuke Miyai, Kimi Kato, Keiichi Ito, Kimiya Sato, Susumu Matsukuma
- J Pathol Transl Med. 2026;60(4):456-461. Published online July 15, 2026
- DOI: https://doi.org/10.4132/jptm.2026.04.23
- 2,014 View
- 46 Download
-
Abstract
PDF
- Succinate dehydrogenase (SDH)–deficient renal cell carcinoma (RCC) is a rare, molecularly defined neoplasm. We report a 45-year-old man with a right renal mass treated by nephrectomy. Grossly, a 38-mm gray-white-to-brown solid cystic tumor was observed in the lower pole of the kidney. Microscopically, the tumor consisted of sheets and nested proliferation of eosinophilic cells with low-grade nuclei and bubbly or flocculent cytoplasm. No sarcomatoid or rhabdoid features were observed. Abundant extracellular and focal intracytoplasmic mucinous material was observed in the tumor, which was positive for Alcian blue and mucicarmine staining, but negative for periodic acid–Schiff staining. Immunohistochemistry showed complete loss of succinate dehydrogenase subunit B in tumor cells. These findings supported the diagnosis of RCC consistent with SDH-deficient RCC. This case expands the morphological spectrum of SDH-deficient RCC and highlights the diagnostic pitfalls of renal tumors with mucinous material.
Original Article
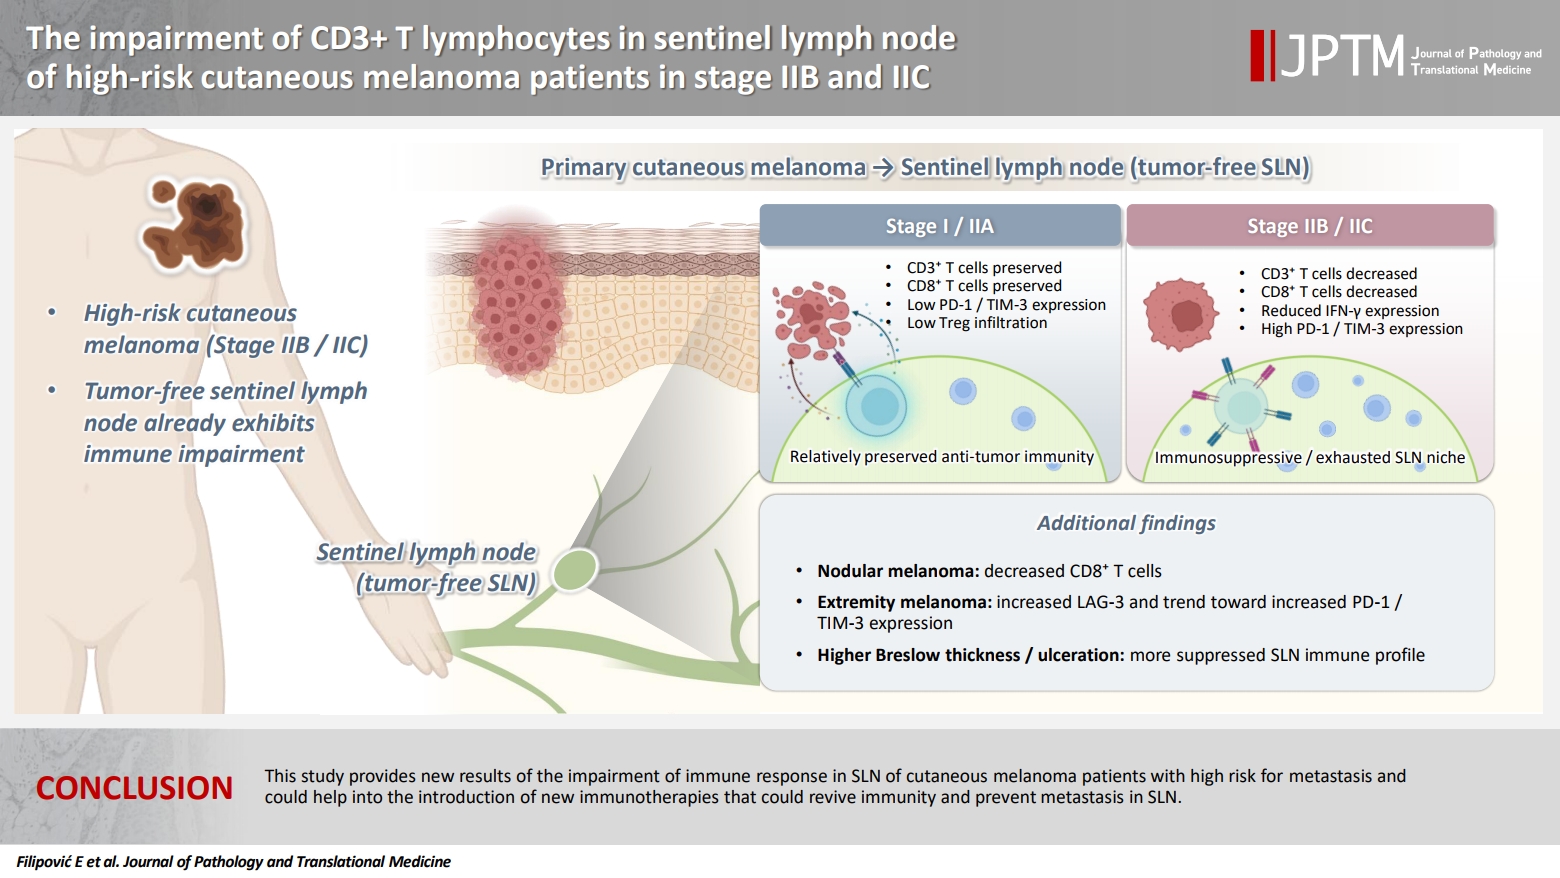
- The impairment of CD3+ T lymphocytes in sentinel lymph node of high-risk cutaneous melanoma patients in stage IIB and IIC
- Emilija Filipović, Katarina Mirjačić Martinović, Ognjen Živković, Nataša Medić Milijić, Ana Lazarević, Zoran Bukumirić, Marko Jevrić, Milan Žegarac
- J Pathol Transl Med. 2026;60(4):422-435. Published online July 15, 2026
- DOI: https://doi.org/10.4132/jptm.2026.04.02
- 1,746 View
- 45 Download
-
Abstract
PDF
- Background
The sentinel lymph node (SLN) in melanoma is almost always the first site of metastasis and its histopathological assessment is essential for the determination of staging and clinical outcome. Furthermore, this procedure offers the investigation of the early immune response in SLN as melanoma-derived factors suppress the immunity in an early stage that may facilitate metastasis. A better understanding of the immunological changes in SLN may help in the therapeutic stimulation of melanoma immunity to prevent tumor metastasis. Methods: SLN tissues without malignant cells from 74 cutaneous melanoma patients (stage I and II) were analyzed. By flow cytometry, we measured the percentage of natural killer cells, CD3+ T lymphocytes, and their expression of interferon-γ (IFN-γ) and inhibitory immune checkpoint molecules (ICMs), and the percentage of CD4+Foxp3+ regulatory T cells (Tregs). Results: Melanoma patients with worse prognosis, in stage IIB–C, had decreased percentage of total CD3+ and CD3+CD8+ T lymphocytes, trend of IFN-γ decrease, increased inhibitory programmed cell death 1 and T cell immunoglobulin and mucin-domain containing 3 ICMs, and higher percentage of Tregs in their SLNs compared with stage I-IIA patients. Furthermore, patients with nodular melanoma had decreased CD3+CD8+ cells compared with patients with superficial spreading melanoma and together with patients with localization of primary tumor on extremities had an increase in the expression of analyzed ICMs. Conclusions: This study provides new results of the impairment of immune response in SLN of cutaneous melanoma patients with high risk for metastasis and could help in the introduction of new immunotherapies that could restore immunity and prevent metastasis in SLN.
Case Study
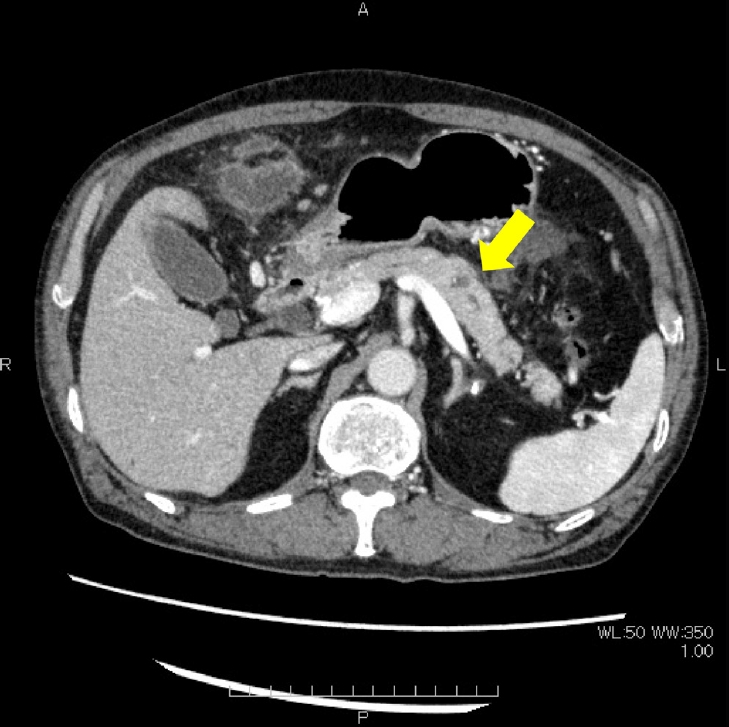
- Non-keratinizing immature squamous metaplasia in the pancreas mimicking malignancy: a diagnostic pitfall in cytology
- Hiroko Hayashi, Tomoaki Kubo, Takuya Hara, Saeko Jinnai, Keisuke Iwasaki
- J Pathol Transl Med. 2026;60(4):444-450. Published online July 15, 2026
- DOI: https://doi.org/10.4132/jptm.2026.02.19
- 1,489 View
- 47 Download
-
Abstract
PDF
- This report describes a challenging case in which atypical immature squamous metaplasia was misinterpreted as malignancy. A 69-year-old man presented with abdominal pain and loss of appetite. Imaging revealed mild pancreatic duct dilation, parenchymal enlargement, and increased fat attenuation in the transverse mesocolon. Endoscopic ultrasound revealed a hypoechoic lesion in the pancreatic body. The serum amylase level was markedly elevated (1,785 U/L), consistent with acute pancreatitis. Repeated pancreatic juice cytology examinations demonstrated atypical epithelial clusters, which raised concerns about possible pancreatic ductal adenocarcinoma. Therefore, distal pancreatectomy with splenectomy and transverse colon resection were performed. However, histopathological examination revealed only atypical immature squamous metaplasia. Retrospective review of the cytological specimens showed overlapping cell clusters with coarse chromatin, prominent nucleoli, nuclear pleomorphism, and peripheral dissociation in a neutrophilic background with focal hemorrhagic necrosis. Although rarely encountered, squamous metaplastic cells can appear in pancreatic cytology and represent a potential pitfall by mimicking adenocarcinoma.
Original Articles
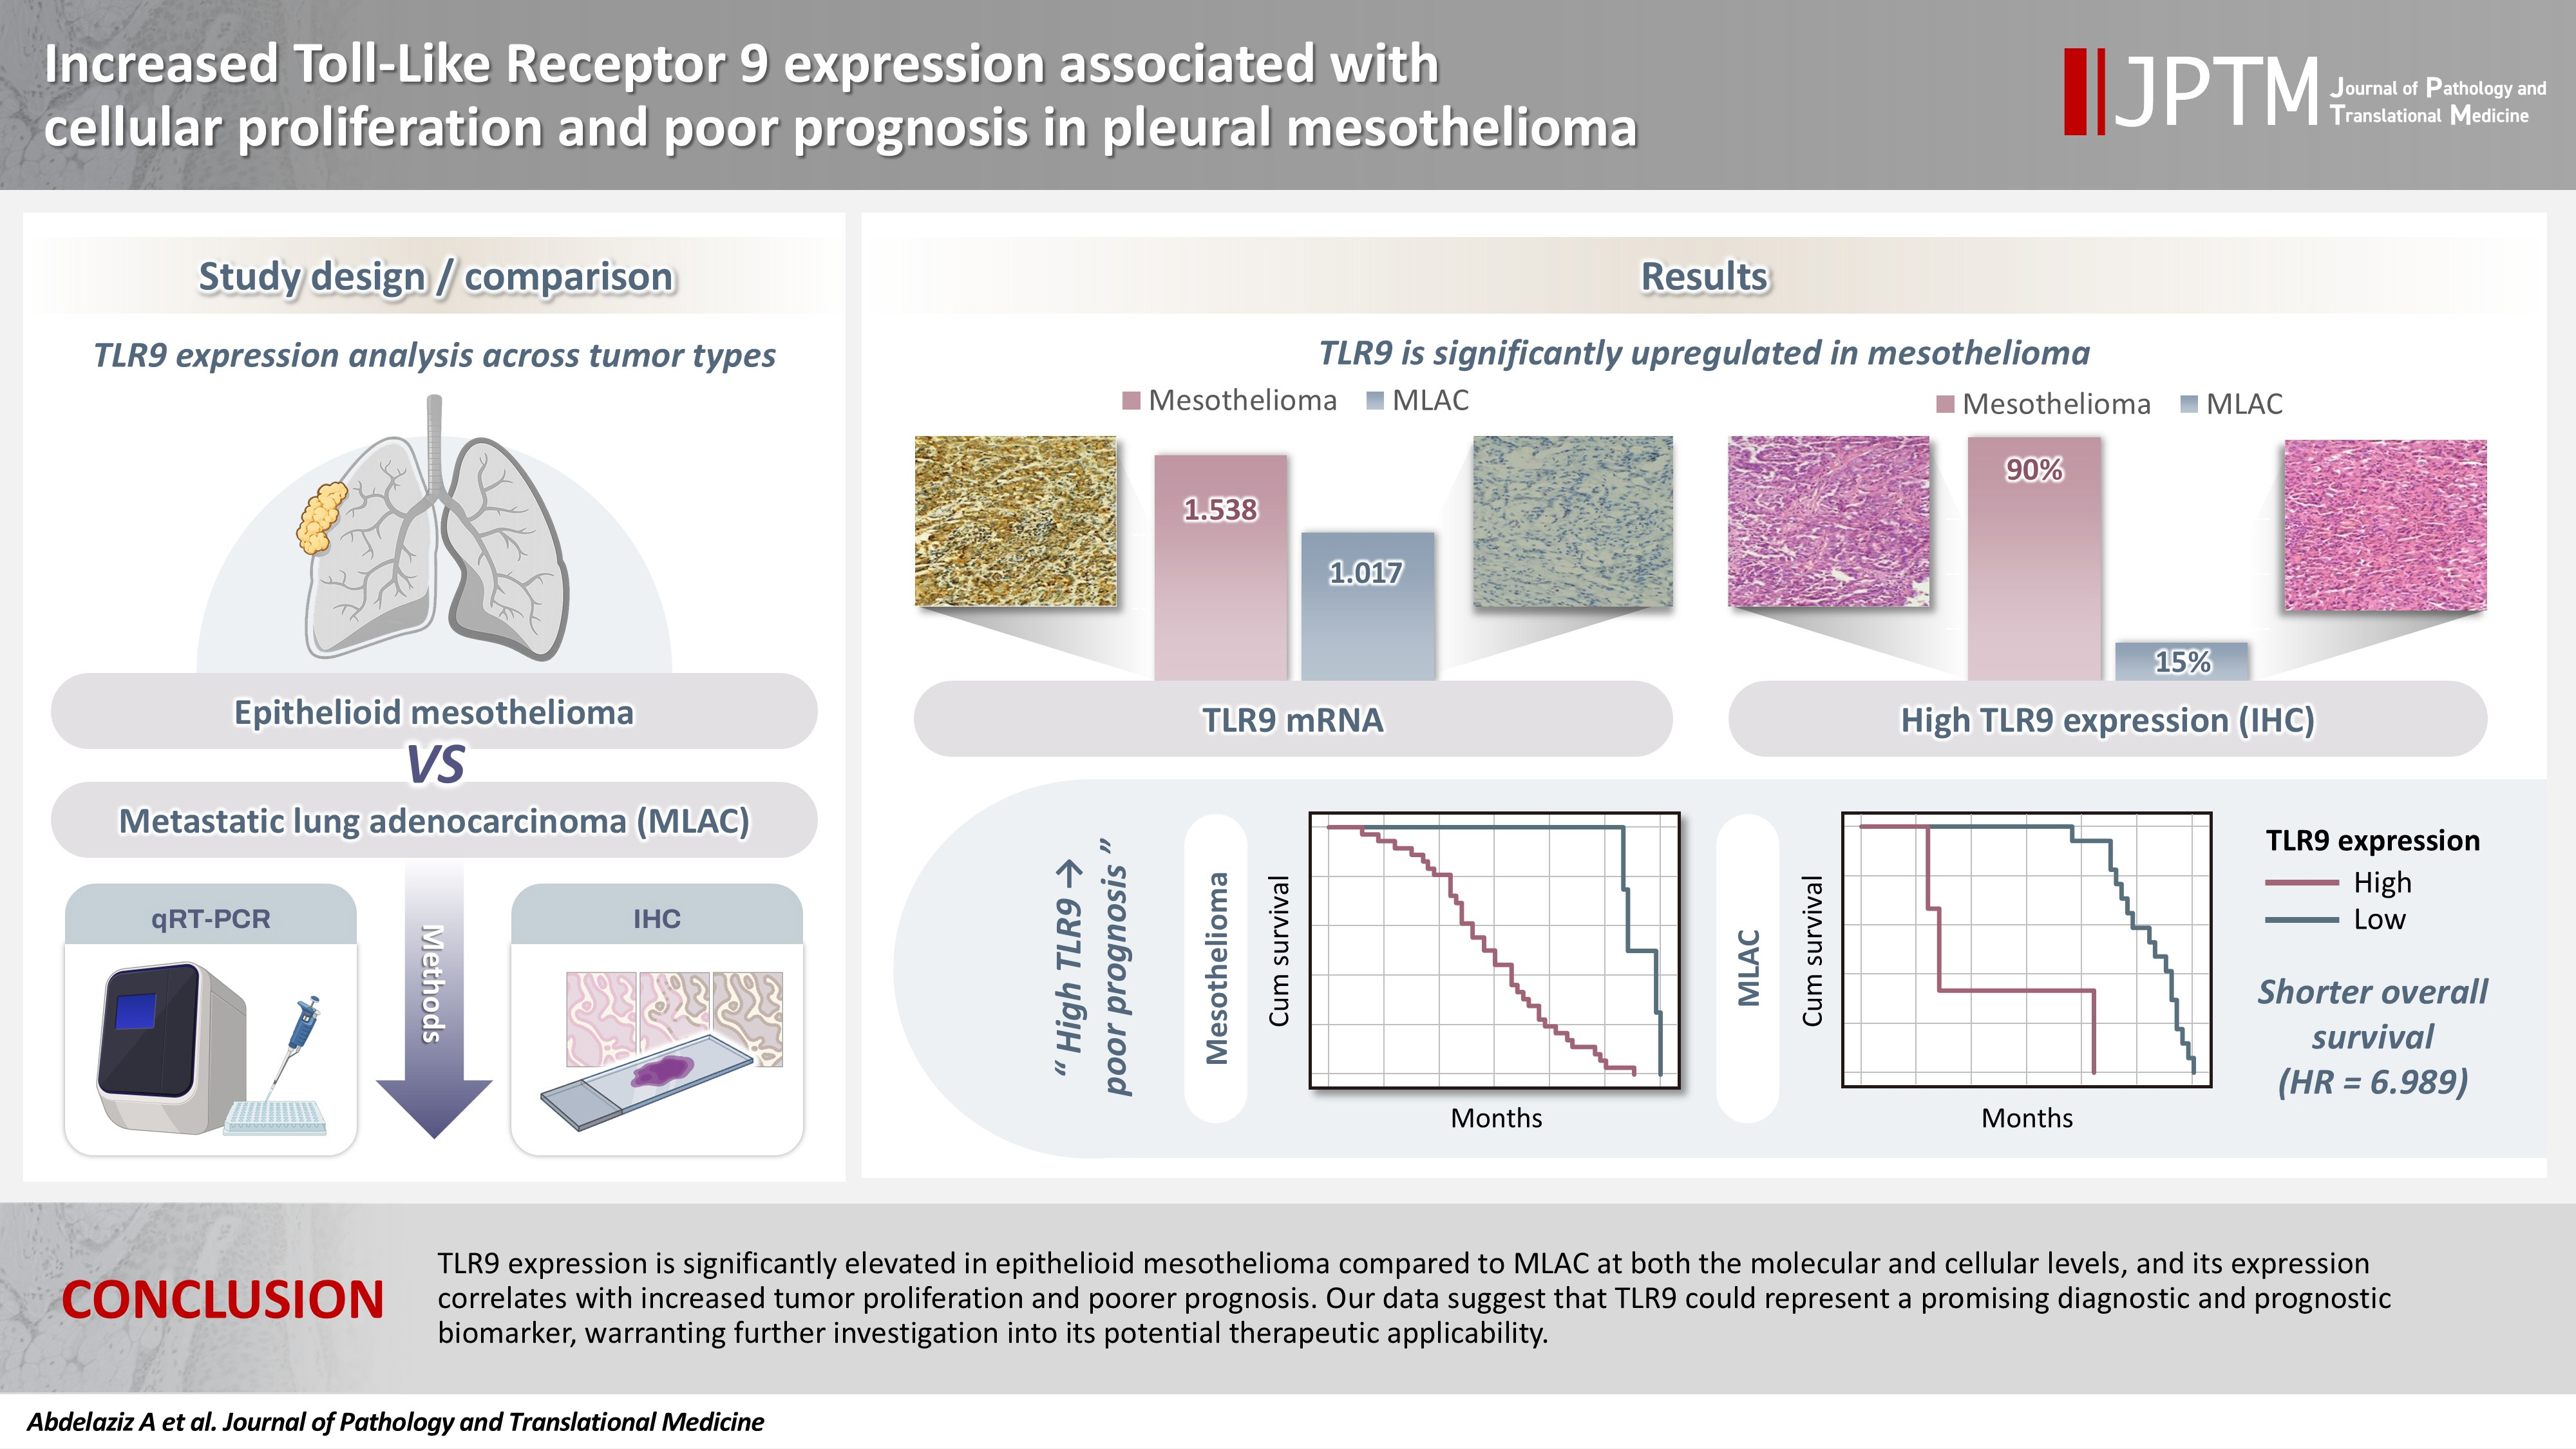
- Increased Toll-like receptor 9 expression associated with cellular proliferation and poor prognosis in pleural mesothelioma
- Ali Omar Abdelaziz, Dina Moustafa Thabit, Rehab Mohamed Kamal, Hend Moness, Rasha Fouad Ahmed, Mariana Fathy Gayyed, Fatma El Zahraa Ammar Mohamed
- J Pathol Transl Med. 2026;60(4):413-421. Published online May 26, 2026
- DOI: https://doi.org/10.4132/jptm.2026.04.01
- 2,397 View
- 49 Download
- 1 Web of Science
- 1 Crossref
-
Abstract
PDFSupplementary Material
- Background
Pleural mesothelioma is an aggressive malignancy with a poor prognosis. The epithelioid subtype is the most common and can be challenging to distinguish from metastatic lung adenocarcinoma (MLAC). The role of Toll-like receptor 9 (TLR9) in the progression of pleural mesothelioma remains unclear. Methods: A total of 30 pleural biopsy specimens were collected, comprising 10 cases of pleural epithelioid mesothelioma and 20 cases of MLAC. The mRNA expression levels of TLR9 and proliferating cell nuclear antigen (PCNA) were quantified. In addition, sixty archived formalin-fixed, paraffin-embedded tissue blocks (40 epithelioid mesothelioma and 20 MLAC) were analyzed via immunohistochemistry using an anti-TLR9 antibody in relation to various clinicopathological parameters. Results: TLR9 expression was significantly higher in epithelioid mesothelioma cases than in MLAC cases (p < .001), with mean values of 1.54 ± 0.09 and 1.02 ± 0.08, respectively. A significant positive correlation was observed between TLR9 and PCNA expression levels specifically in the epithelioid mesothelioma cohort (p < .001, r = 0.8). Furthermore, immunohistochemical analysis confirmed that high TLR9 immunoexpression was significantly more prevalent in epithelioid mesothelioma (36/40 cases; 90%) than in MLAC (3/20 cases; 15%) (p < .001). Notably, elevated TLR9 expression was associated with a significantly shorter overall survival (p = .001). Conclusions: In conclusion, TLR9 expression is significantly elevated in epithelioid mesothelioma compared to MLAC at both the molecular and cellular levels, and its expression correlates with increased tumor proliferation and poorer prognosis. Our data suggest that TLR9 could represent a promising diagnostic and prognostic biomarker, warranting further investigation into its potential therapeutic applicability. -
Citations
Citations to this article as recorded by- Damage-Associated Molecular Patterns in Mesothelioma: Drivers of Inflammation and Therapeutic Targets
Annamaria Molinario, Francesca Caprioglio, Angela A. Rilievo, Marco E. Bianchi, Rosanna Mezzapelle
International Journal of Molecular Sciences.2026; 27(17): 7859. CrossRef
- Damage-Associated Molecular Patterns in Mesothelioma: Drivers of Inflammation and Therapeutic Targets
- A single-institution demographic study of pathologically proven renal disease in kidney transplant recipients over the last 33 years
- Hyejin Noh, Jiyeon Kim, Yeong Jin Choi
- J Pathol Transl Med. 2026;60(4):398-412. Published online May 26, 2026
- DOI: https://doi.org/10.4132/jptm.2026.03.28
- 2,640 View
- 64 Download
-
Abstract
PDFSupplementary Material
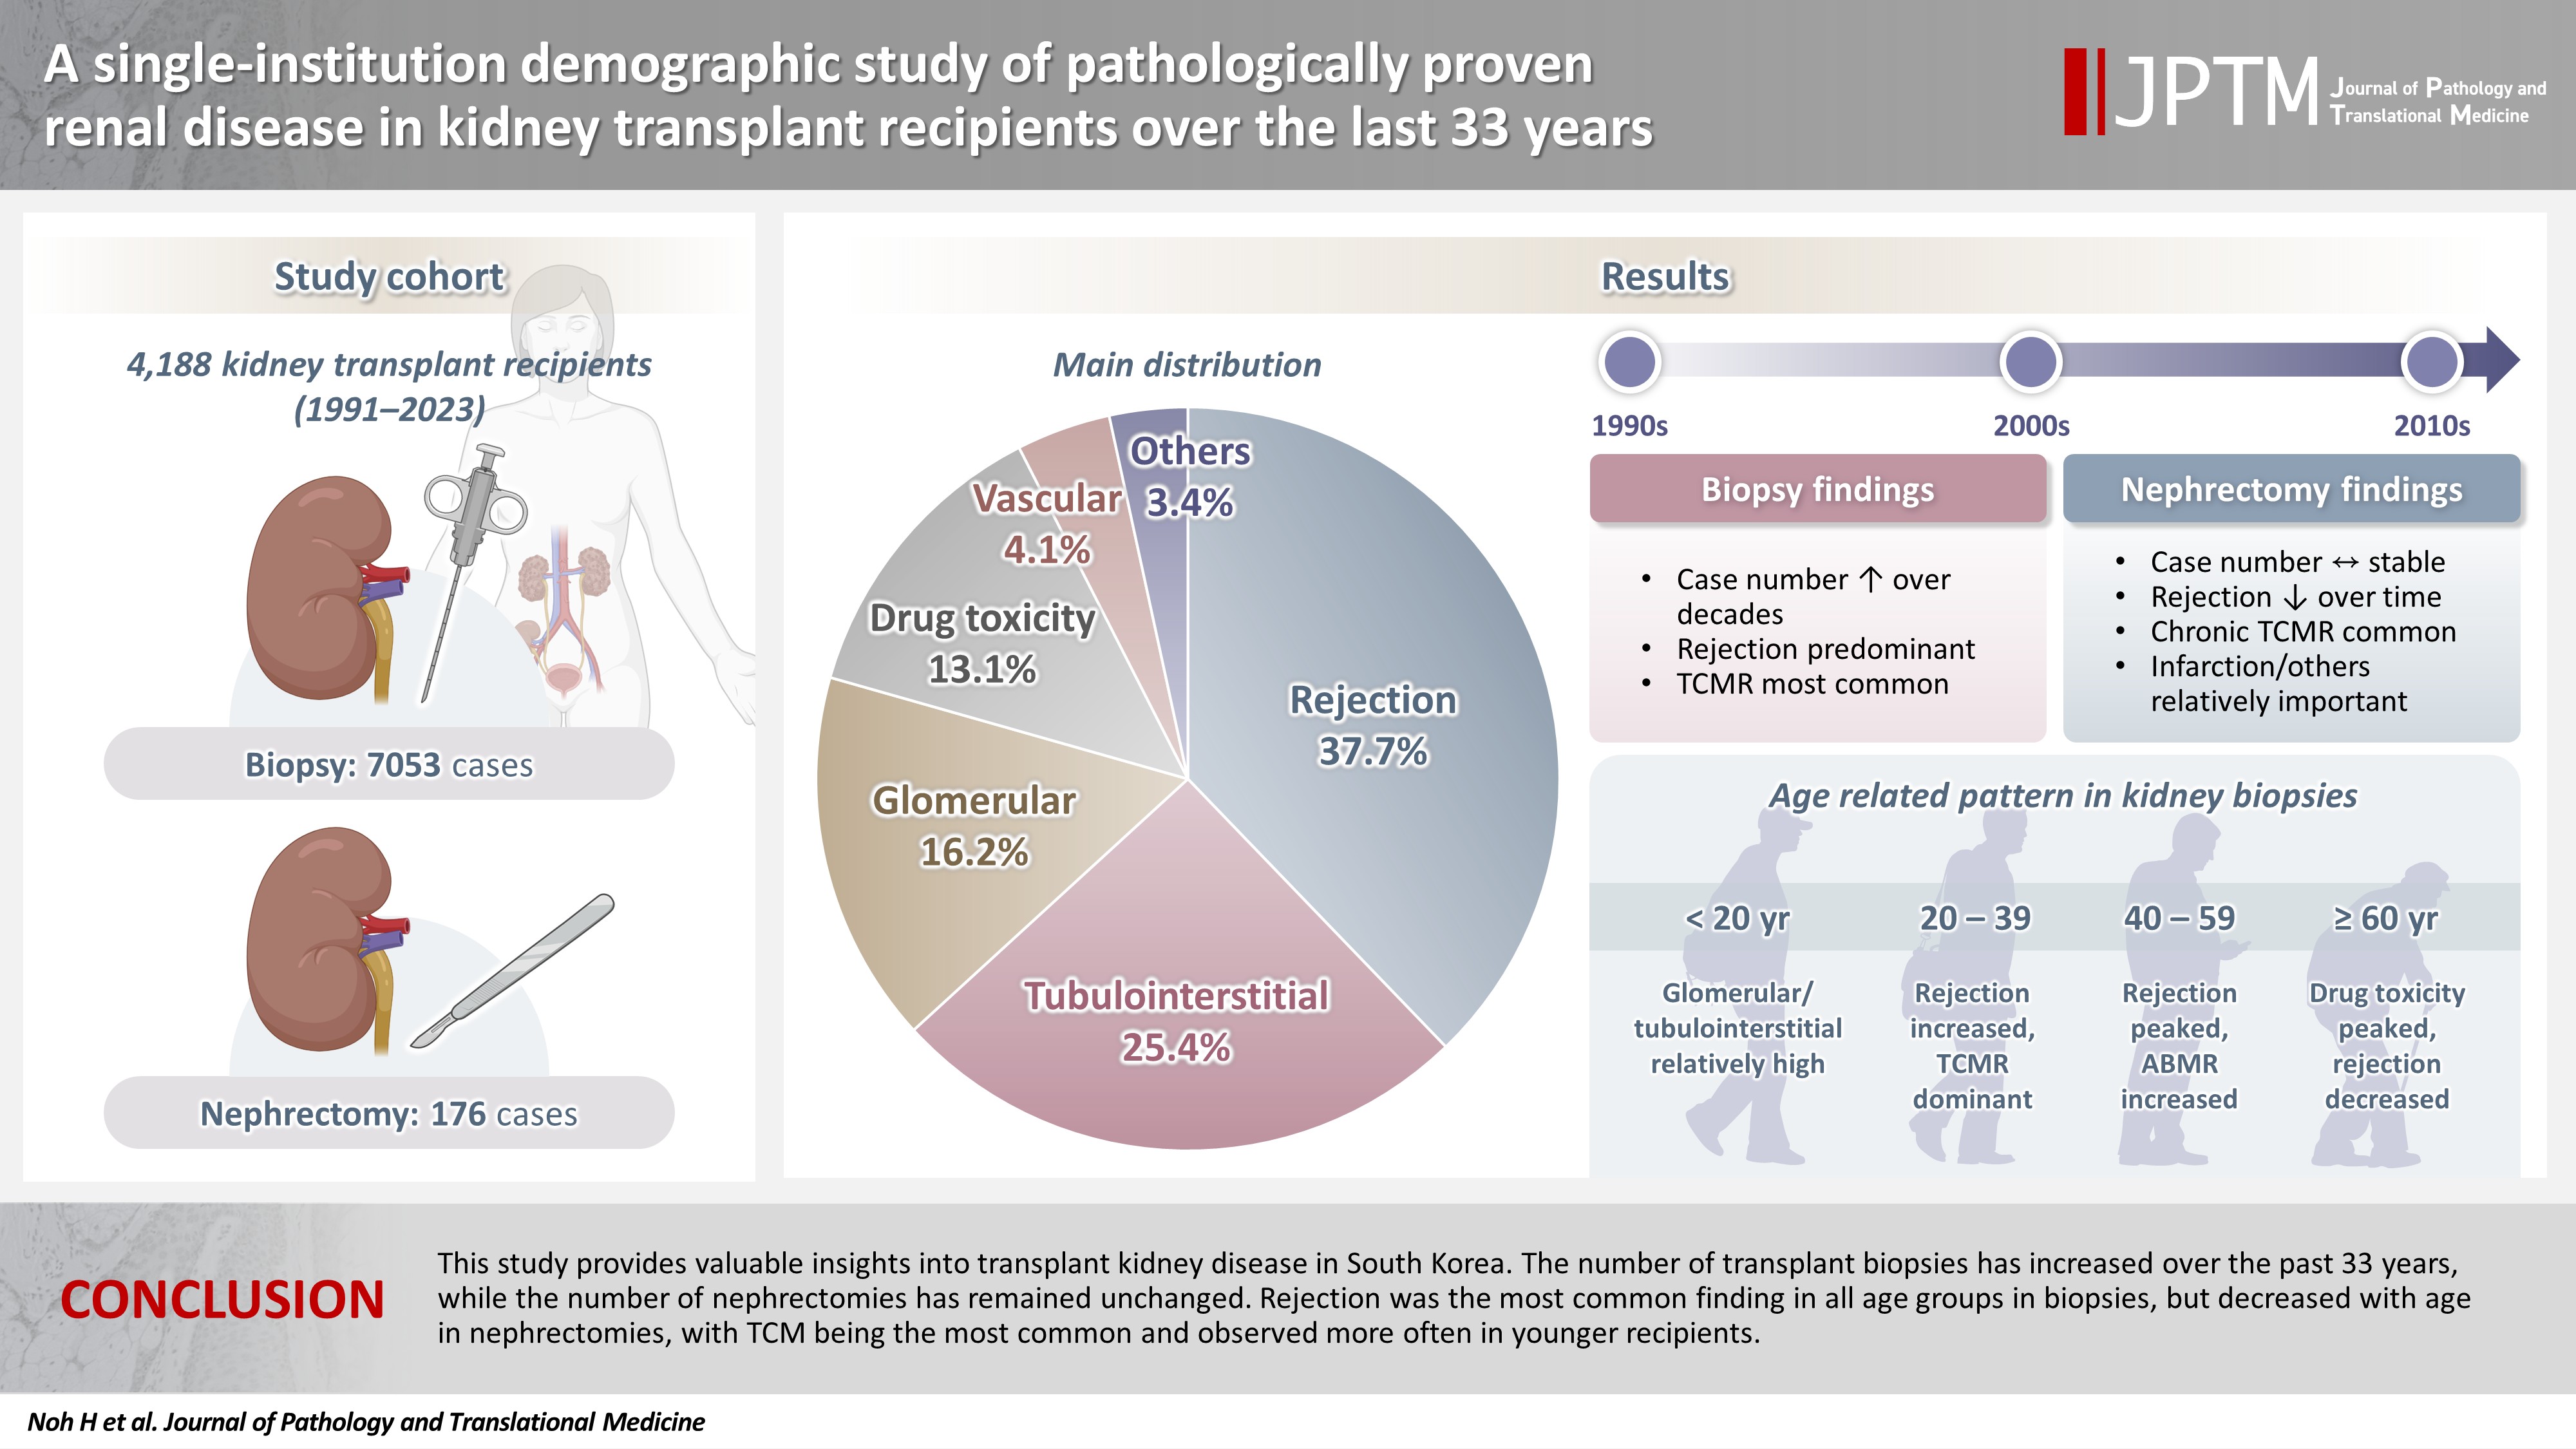
- Background
While the number of kidney transplants for end-stage renal disease (ESRD) is increasing, studies examining the long-term demographic analyses based on pathological diagnosis of transplant kidney remain limited. Methods: We conducted a retrospective analysis of 4,188 transplant recipients who underwent either biopsy or nephrectomy from 1991 to 2023 at Seoul St. Mary’s Hospital. Results: Among 7,229 pathologically confirmed cases, rejection was the most prevalent (37.7%), followed by tubulointerstitial (25.4%), glomerular, drug toxicity, and vascular diseases. In 7,053 transplant biopsies, rejection was predominant across all age groups, with T-cell mediated (TCM) category being the most common (60.1%), followed by antibody-mediated and mixed. Drug toxicity increased with age (p = .047), while glomerular and tubulointerstitial diseases were highest in recipients under 20 (p < .001). Among glomerular diseases, IgA-related glomerulonephritis (45.2%) was the most common. In 176 transplant nephrectomies, the most common diagnosis was rejection (33.5%), followed by renal infarction (19.9%), tubulointerstitial, vascular, glomerular disease, and drug toxicity. “Others” included infarction, ESRD, and lymphangiectasia, which increased with age (p = .011). In nephrectomy cases, rejection decreased over time, with chronic TCM rejection (40.7%) being the most frequent. Conclusions: This study provides valuable insights into transplant kidney disease in South Korea. The number of transplant biopsies has increased over the past 33 years, while the number of nephrectomies has remained unchanged. Rejection was the most common finding in all age groups in biopsies, but decreased with age in nephrectomies, with TCM being the most common and observed more often in younger recipients.
- Incidental serrated lesions of the appendix: analysis of 2,137 appendectomy specimens
- Ömer Atmış, Ecem Dokuzlu Küçük, Hanife Seda Mavili, Fatma Seher Pehlivan, Ayça Tan, Semin Ayhan
- J Pathol Transl Med. 2026;60(3):349-355. Published online May 4, 2026
- DOI: https://doi.org/10.4132/jptm.2026.02.08
- 3,295 View
- 81 Download
-
Abstract
PDF
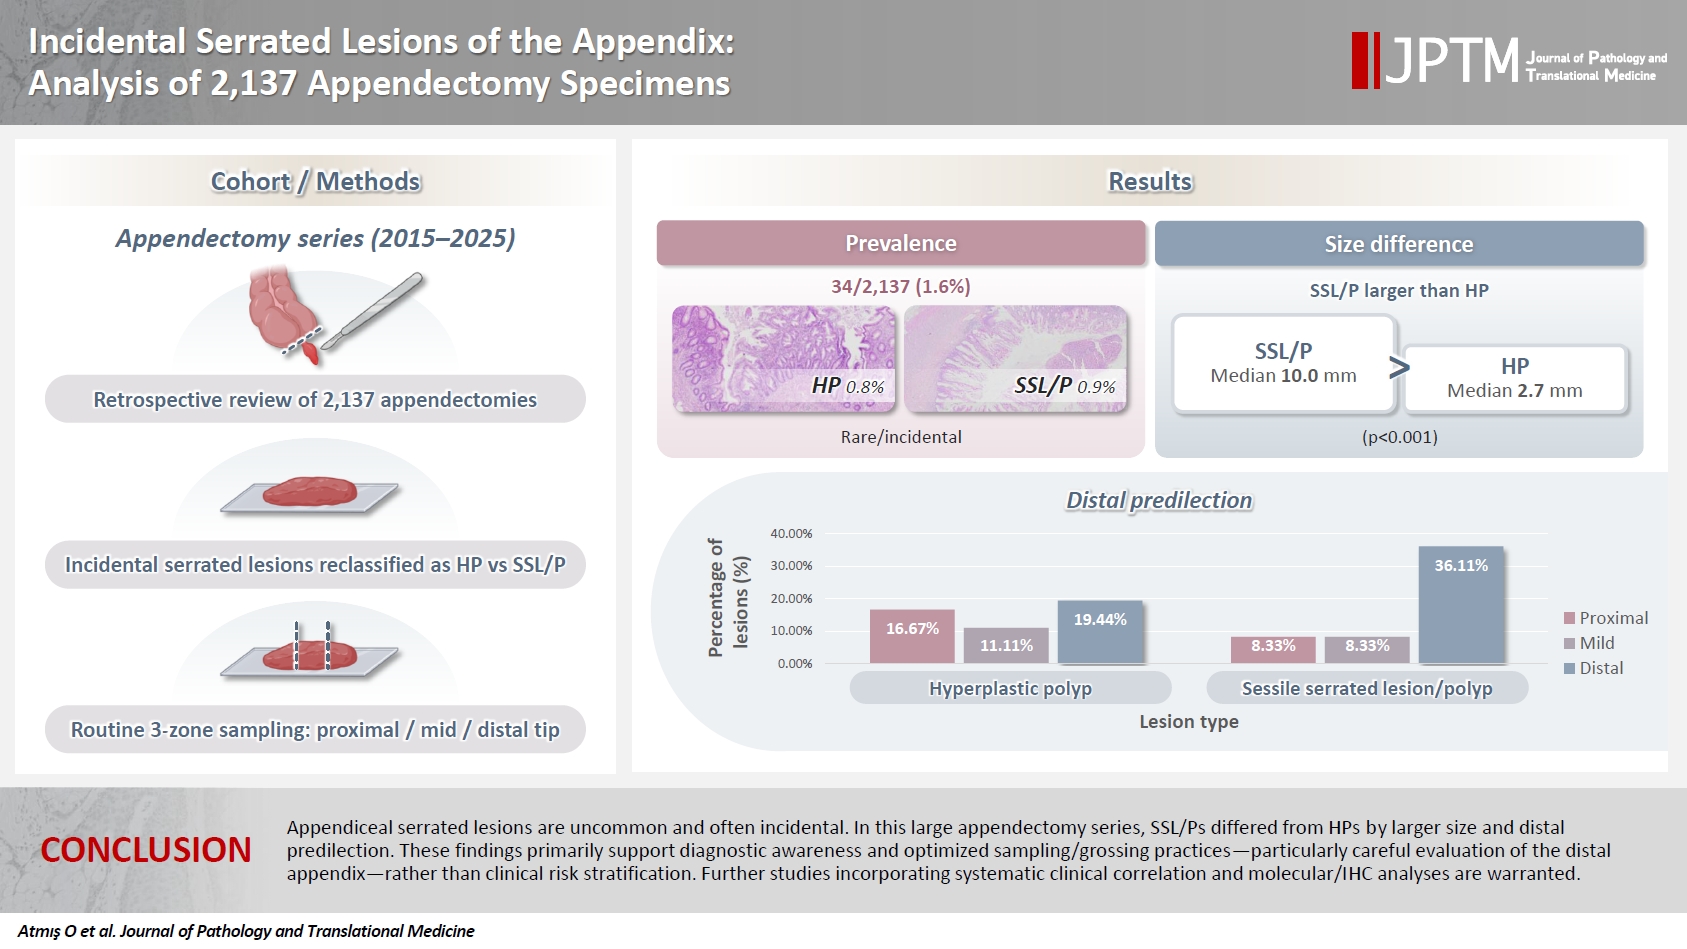
- Background
Serrated lesions of the appendix are rare, often incidental findings in routine appendectomy specimens. Their true frequency, histopathologic spectrum, and anatomic distribution remain incompletely characterized, partly due to variability in sampling practices. Methods: We retrospectively reviewed 2,137 appendectomy specimens (2015–2025) from a single tertiary pathology center. Cases with histologically confirmed serrated lesions were reexamined, classified as hyperplastic polyp (HP) or sessile serrated lesion/polyp (SSL/P), and assessed for clinicopathologic parameters including lesion size, location, and associated pathologies. Nonparametric tests were used, with statistical significance defined as p < .05. Results: Serrated lesions were identified in 34 cases (1.6%) with 36 serrated lesions, comprising 17 HPs (0.8%) and 19 SSL/Ps (0.9%). SSL/Ps were significantly larger than HPs (median 10.0 vs. 2.7 mm, p < .001) and were more frequently located in the distal appendix (68.4% vs. 33.3%, p = .045, one-tailed Fisher’s exact test). No dysplasia or traditional serrated adenoma was detected. Acute appendicitis was present in 88% of cases, and associated neoplasms in 9%. Conclusions: Appendiceal serrated lesions are uncommon and often incidental. In this large appendectomy series, SSL/Ps differed from HPs by larger size and distal predilection. These findings primarily support diagnostic awareness and optimized sampling/grossing practices—particularly careful evaluation of the distal appendix—rather than clinical risk stratification. Further studies incorporating systematic clinical correlation and molecular/immunohistochemistry analyses are warranted.
- Clinicopathological profile of high-grade differentiated thyroid carcinoma in an Indonesian tertiary hospital
- Novita , Agnes Stephanie Harahap, Maria Francisca Ham, Alfianto Widiono, Chan Kwon Jung
- J Pathol Transl Med. 2026;60(3):338-348. Published online April 23, 2026
- DOI: https://doi.org/10.4132/jptm.2026.01.15
- 3,898 View
- 99 Download
-
Abstract
PDFSupplementary Material
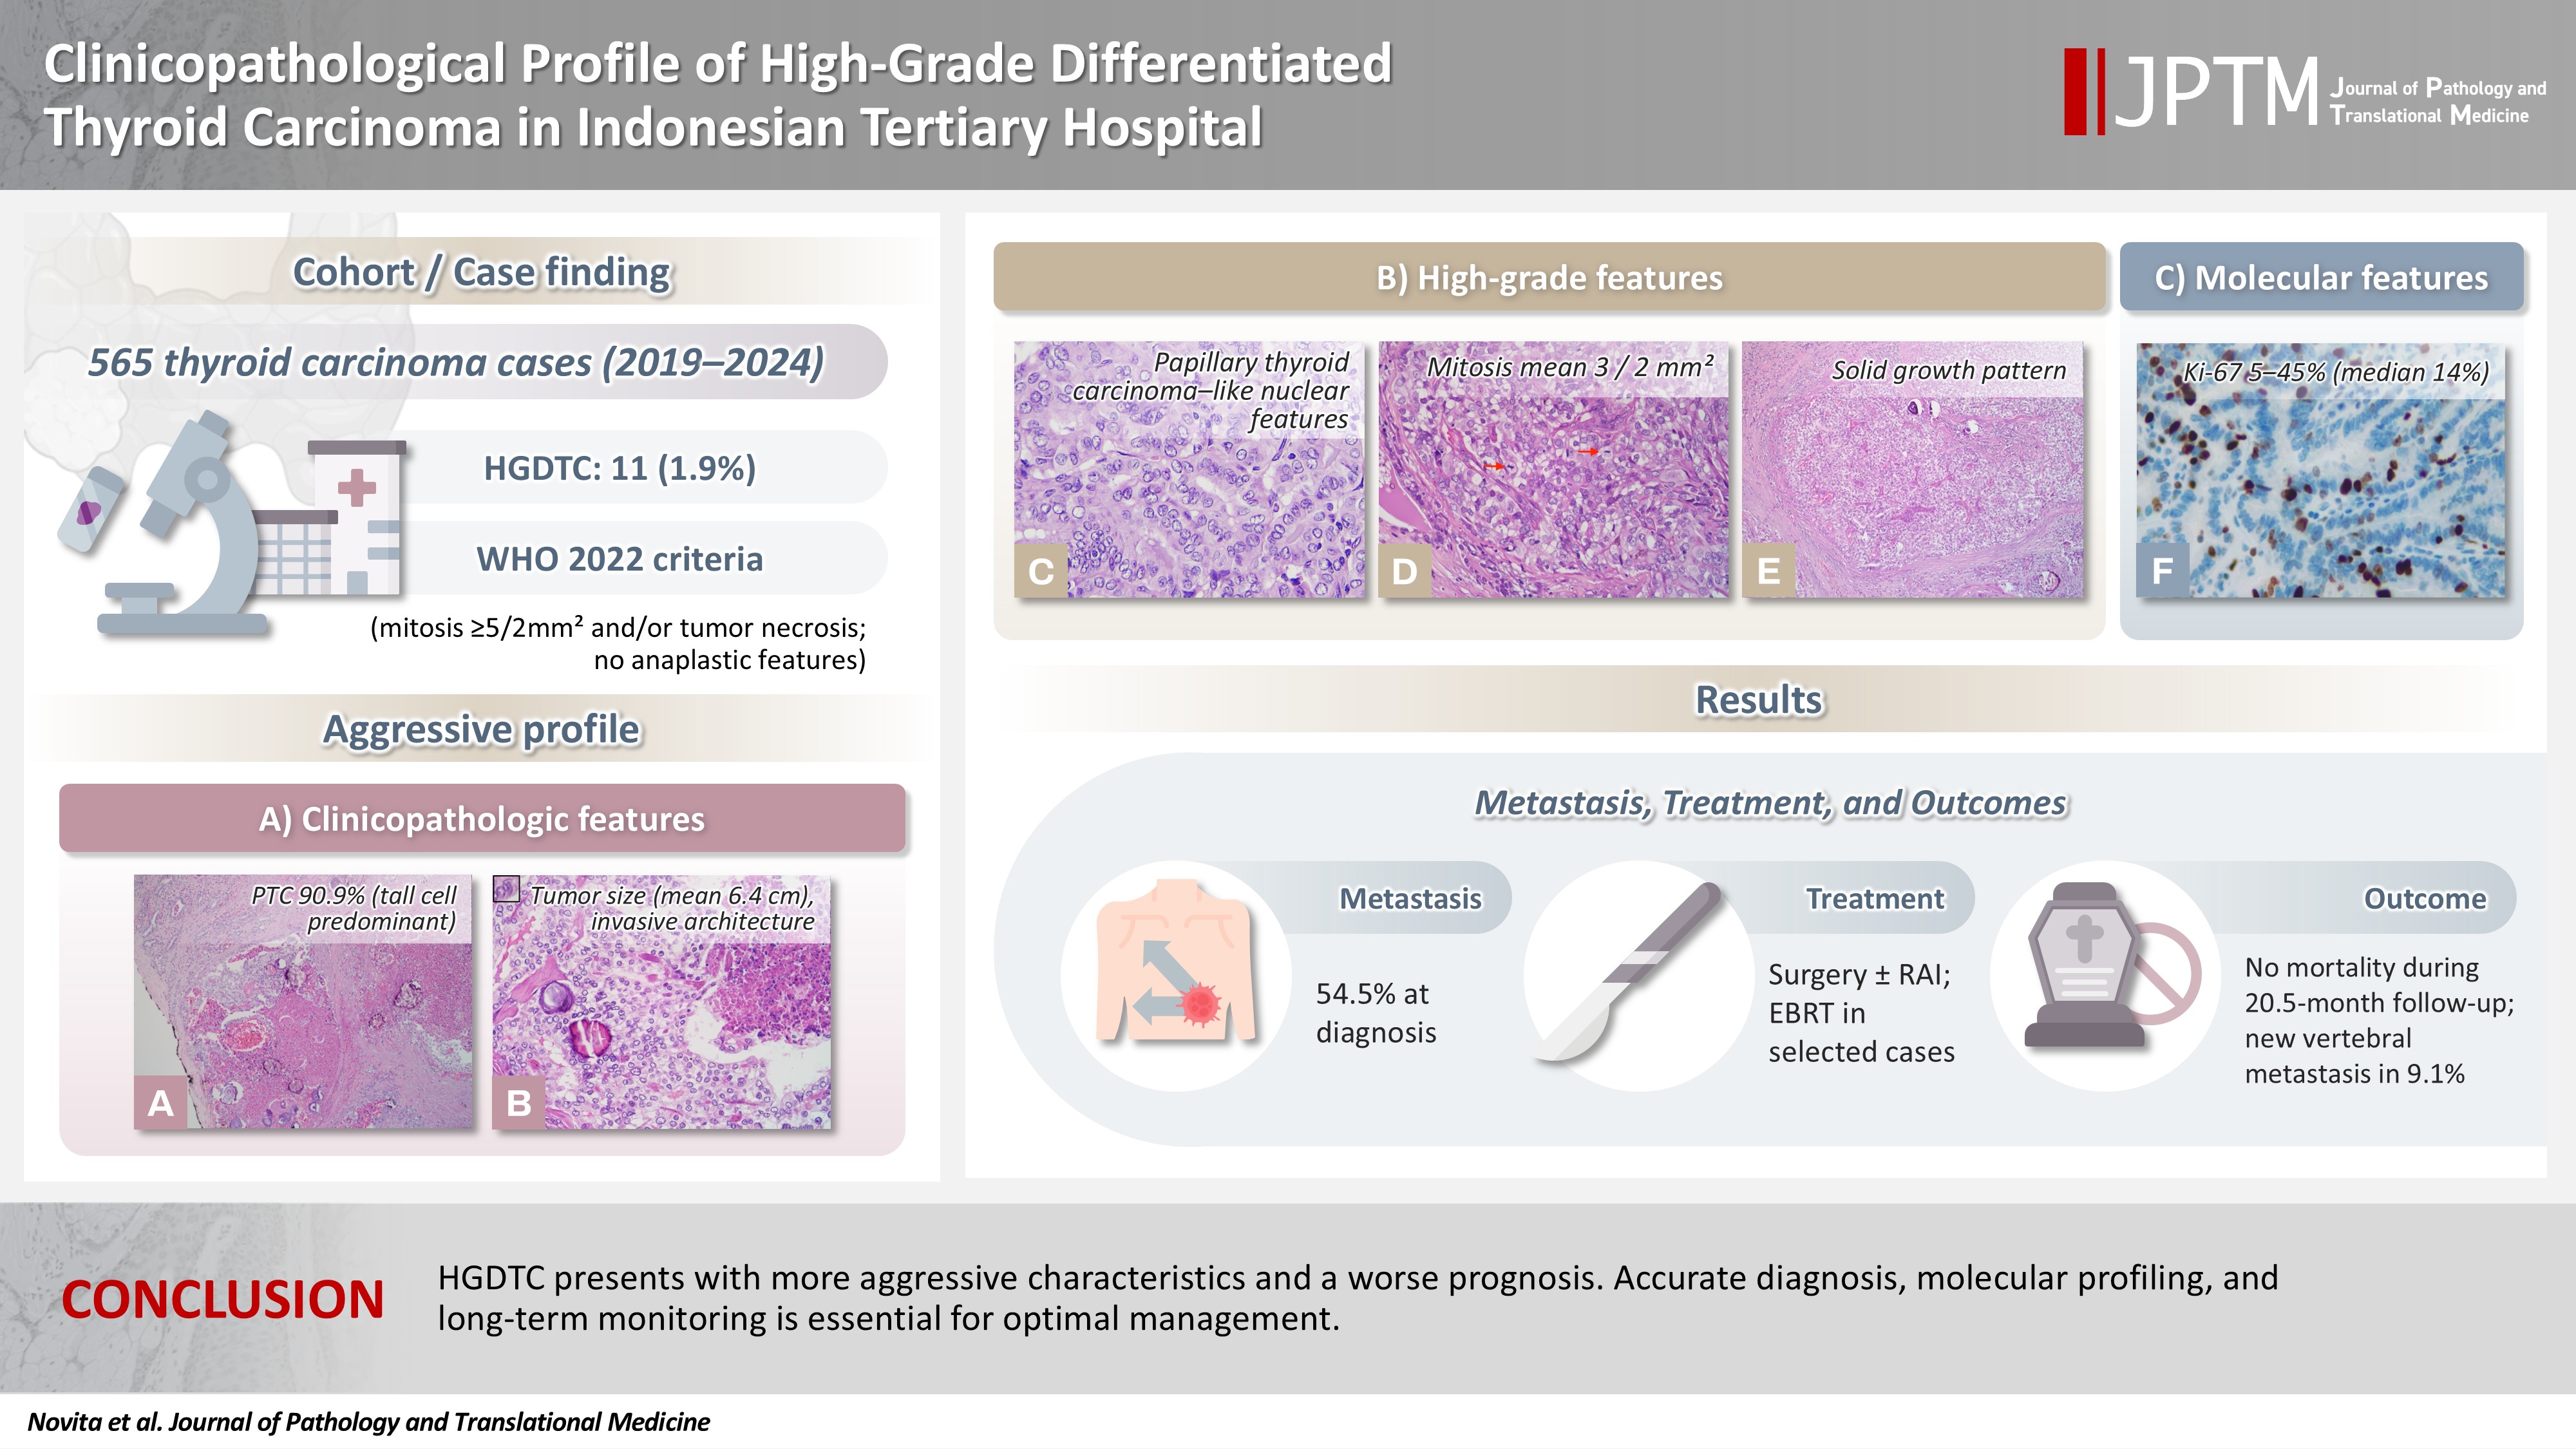
- Background
High-grade differentiated thyroid carcinoma (HGDTC) is a recently recognized entity in the 2022 World Health Organization classification, representing a more aggressive subtype of differentiated thyroid carcinoma. Previously, high-grade features such as increased mitotic activity and tumor necrosis were often overlooked, despite being important independent prognostic factors. Although rare, HGDTC carries significant diagnostic, prognostic, and therapeutic implications. Data remain limited in Indonesia. Methods: This retrospective descriptive study reviewed 565 thyroid carcinoma cases diagnosed at Cipto Mangunkusumo Hospital from 2019 to 2024. Eleven cases (1.9%) met HGDTC criteria. Clinicopathological characteristics, histologic subtypes, Ki-67 proliferation index, molecular alterations, treatment modalities, and clinical outcomes were analyzed. Results: Patients had a mean age of 54.6 years, with a female-to-male ratio of 2.7:1. Papillary thyroid carcinoma was the main type (90.9%), with the tall cell subtype predominating. Mean tumor size was 6.4 cm. Lymphatic invasion, vascular invasion, and extrathyroidal extension were present in 54.5%, 18.2%, and 45.5% of cases, respectively. All tumors showed necrosis. Mean mitotic count was 3 per 2 mm². The Ki-67 index ranged from 5% to 45% (median, 14%). BRAFV600E and TERT promoter mutations were detected in 18.2% and 36.4% of cases, respectively, with co-mutations in 18.2%. Six cases (54.5%) had metastases at time of diagnosis. During a mean follow-up of 20.5 months, one patient (9.1%) developed new vertebral metastases and all patients (100%) remained alive. Conclusions: HGDTC presents with more aggressive characteristics and a worse prognosis. Accurate diagnosis, molecular profiling, and long-term monitoring are essential for optimal management.
Case Study
- Phenotypic plasticity in plasma cell myeloma: a CD138-negative case with a rare BRAF G469R mutation
- Sun-Ju Oh, So-Hak Chung
- J Pathol Transl Med. 2026;60(4):451-455. Published online April 22, 2026
- DOI: https://doi.org/10.4132/jptm.2026.02.02
- 2,908 View
- 93 Download
-
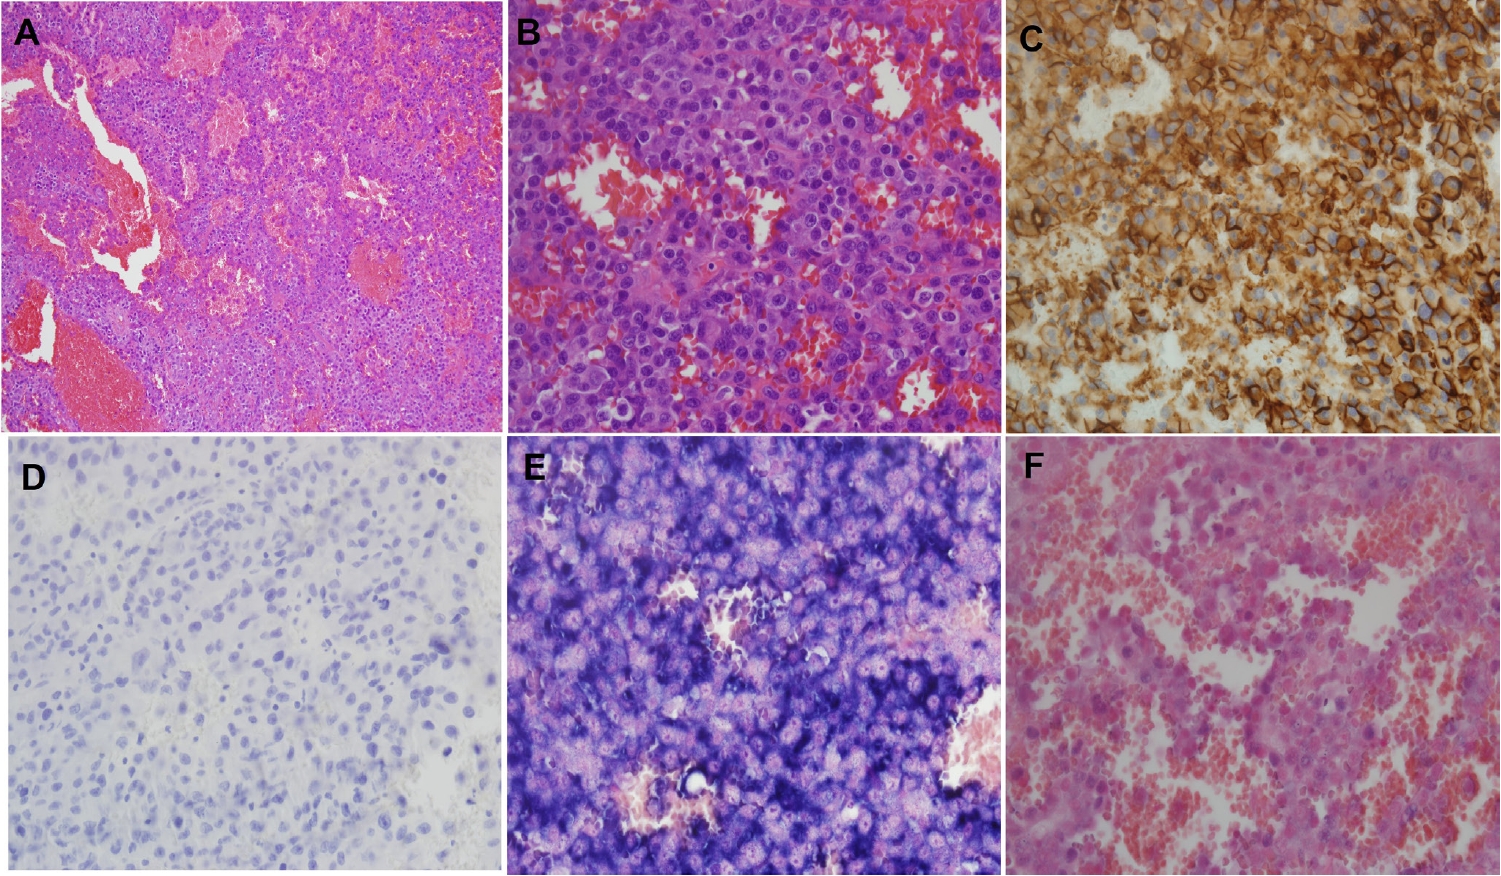
Abstract
PDF
- CD138-negative plasma cell myeloma harboring a BRAF G469R mutation is described in a 76-year-old male presenting with multiple osteolytic lesions. Histologically, the lesion exhibited epithelioid to plasmacytoid morphology with prominent mitotic activity and vascular-like spaces. Immunophenotyping demonstrated strong vimentin and CD31 expression but absence of CD138 and other endothelial markers. Light-chain in situ hybridization confirmed a clonal κ-restricted plasma cell population. Bone marrow examination revealed near-complete replacement by atypical plasma cells, retaining CD138 negativity and demonstrating focal CD20 positivity, indicative of intratumoral heterogeneity. Next-generation sequencing identified a rare BRAF G469R variant. The patient exhibited poor response to bortezomib, lenalidomide, and dexamethasone therapy, necessitating a switch to carfilzomib-based treatment. This case underscores the diagnostic challenges of CD138-negative myeloma and highlights the importance of integrating morphology, immunophenotyping, and molecular profiling to inform accurate diagnosis and guide therapeutic strategies.
Original Article
- Expression of PD-1/PD-L1 pathway molecules in human cardiac allograft according to acute cellular rejection status: insights from a Korean Heart Transplant Cohort
- Jeemin Yim, Yoon Kyung Jeon, Doo Hyun Chung, Jaemoon Koh
- J Pathol Transl Med. 2026;60(3):319-330. Published online March 27, 2026
- DOI: https://doi.org/10.4132/jptm.2026.01.02
- 3,759 View
- 89 Download
- 1 Web of Science
- 1 Crossref
-
Abstract
PDF
- Background
Acute cellular rejection (ACR) following heart transplantation (TPL) compromises graft function and survival. The programmed cell death-1 (PD-1)/PD-1 ligand-1 (PD-L1) pathway represents an immune checkpoint that maintains peripheral immune tolerance, but its expression and significance in human cardiac allografts with ACR remain unclear. Thus, we investigated PD-1/ PD-L1 expression in endomyocardial biopsies from heart TPL recipients to clarify the role of this pathway in the ACR of human cardiac allografts and explore the potential of therapeutic modulation of PD-1/PD-L1 in this setting. Methods: Endomyocardial biopsies of 78 patients with heart TPL were subjected to immunohistochemistry for PD-L1, PD-1, CD4, and CD8. PD-L1 expression and quantities of PD-1+, CD4+, and CD8+ infiltrating lymphocytes were evaluated according to clinicopathological features, ACR presence, and clinical outcomes. Results: Allografts with high-grade ACR (International Society for Heart and Lung Transplantation grades 2R and 3R) demonstrated markedly higher PD-L1 expression than did those without ACR (62.5% vs. 16.1%, p < .001). PD-L1 expression was positively associated with CD4+ lymphocyte infiltration (p = .025), whereas CD8 and PD-1+ lymphocyte counts were higher in PD-L1-positive allografts without reaching statistical significance (p = .059 and p = .390, respectively). Serial biopsies revealed that PD-L1 expression was upregulated in patients with high-grade ACR compared with that in previous non-ACR tissues, and follow-up biopsies were performed after ACR resolution. Conclusions: The PD-1/PD-L1 pathway is involved in ACR regulation in human cardiac allografts. Increased PD-L1 expression during ACR may represent a counteractive mechanism to limit alloimmune-mediated tissue injury, supporting PD-1/PD-L1 as a potential therapeutic target in heart TPL recipients. -
Citations
Citations to this article as recorded by- Immune Responses in Checkpoint Inhibitor–Associated Cardiovascular Immune–Related Adverse Events
Kerry L. Reynolds, Alexandra-Chloé Villani, Zsófia Dora Drobni, Tomas G. Neilan, Han Zhu, Noah S. Wagner, Justin M. Balko, Reilly Fankhauser, Javid J. Moslehi, Nicolas L. Palaskas, Kristen E. Pauken, Bilal A. Siddiqui, Steven M. Blum, Daniel A. Zlotoff
JACC: CardioOncology.2026; 8(5): 463. CrossRef
- Immune Responses in Checkpoint Inhibitor–Associated Cardiovascular Immune–Related Adverse Events
Case Study
- Multidimensional analysis of concurrent proximal bronchiolar adenoma and lung carcinoma
- Lu-Yao Li, Gong-Ming Dong, Yun-Peng Zhang, Ting-Ting Wang, Fu-Quan Jia, Guan-Jun Zhang
- J Pathol Transl Med. 2026;60(3):356-363. Published online March 23, 2026
- DOI: https://doi.org/10.4132/jptm.2025.12.31
- 3,288 View
- 94 Download
-
Abstract
PDFSupplementary Material
- Bronchiolar adenoma (BA) is a rare type of lung tumor characterized by bilayered epithelial cells having a continuous basal layer and a luminal layer. It resembles mucinous adenocarcinoma (MA) on frozen section, with difficulty in distinguishing the basal layer. Immunohistochemistry is the best choice for verifying the diagnosis. This study aimed to comprehensively characterize three cases of BA-combined carcinoma using clinical, histopathological, and genetic features. BA and carcinoma sections were subjected to next-generation sequencing, respectively. It was hypothesized that while different mutation forms matched different regions, BA and lung adenocarcinoma shared the same gene mutation when they co-occurred in the same location. BA with extensive carcinoma is extremely rare and presents diagnostic challenges due to its overlap with conditions such as MA. Because of its distinctive morphological characteristics, BA may be regarded as a low-grade malignancy, particularly during a confusing evaluation. A multifaceted examination of clinical, radiological, immunohistochemical, and genetic data is necessary for an accurate diagnosis.
Original Articles
- HER2-low and ultralow breast cancer: interobserver challenges and lessons from a consensus study
- Jiwon Koh, Yoon Jin Cha, Eun Yoon Cho, Ahwon Lee, Ja Seung Koo, So Yeon Park, Min Hwan Kim, Jae Ho Jeong, Gyungyub Gong
- J Pathol Transl Med. 2026;60(3):331-337. Published online March 20, 2026
- DOI: https://doi.org/10.4132/jptm.2026.01.08
- 5,199 View
- 323 Download
- 2 Web of Science
- 3 Crossref
-
Abstract
PDF
- Background
The recent approval of trastuzumab deruxtecan for human epidermal growth factor receptor 2 (HER2)–low and HER2-ultralow breast cancer mandates an adequate assessment of these categories. Methods: Seven breast pathologists from the Breast Pathology Study Group of the Korean Society of Pathologists held an on-site expert consensus meeting. Fifteen sets of virtual whole slide images (WSI) of hematoxylin and eosin stain and HER2 immunohistochemistry were provided. The pathologists were given 60 minutes to submit their diagnosis of HER2 expression into null, ultralow, 1+, 2+, or 3+. Afterwards, in-depth discussion and consensus diagnoses were made by real-time visualization of the WSI. Results: After the consensus meeting, unanimous 100% agreements were seen only in five (33.3%) of the examined cases, which consisted of three 1+ cases and two 2+ cases. Two cases (13.3%) had mild disagreement, with only one pathologist’s disagreement. Of note, eight cases (53.3%) showed significant disagreement, defined by more than two pathologists’ disagreement. All HER2-null cases were reclassified as ultralow after consensus review, suggesting potential widespread underclassification of ultralow cases in clinical practice. Conclusions: Experts had significant discrepancies in interpreting HER2-low/ultralow status. It is important to assess if the distinction between HER2-low and ultralow is strictly required and if HER2-null breast cancer exists in reality. -
Citations
Citations to this article as recorded by- Comparative analysis of robotic- and endoscopic-assisted minimally invasive nipple–areola complex–sparing mastectomy for breast cancer: a meta-analysis with subgroup analyses
Xiaohan Wang, Hua Tian, Min Zhang, Jiangyong Shen, Yangxu Ding, Yupei Dai, Huijuan Shi
Journal of Robotic Surgery.2026;[Epub] CrossRef - HER2-Low Breast Cancer: A Review of Epidemiology, Diagnostic Challenges, Targeted Therapies, and Clinical Outcomes
Maedeh Mirasheh, Zahra Shahabinia, Mai Abdel Haleem A. Abusalah, Afrooz Mazidimoradi, Leila Allahqoli, Hamid Salehiniya, Do-Youn Lee
Journal of Clinical Medicine.2026; 15(19): 7559. CrossRef - Interobserver Reproducibility of Treatment-Defining HER2-Low and HER2-Ultralow Immunohistochemical Scoring in Breast Carcinoma: A Systematic Review
Vishal Tayade, Gyanendra Singh
Applied Immunohistochemistry & Molecular Morphology.2026;[Epub] CrossRef
- Comparative analysis of robotic- and endoscopic-assisted minimally invasive nipple–areola complex–sparing mastectomy for breast cancer: a meta-analysis with subgroup analyses
- Aquaporin 1 promotes proliferation and migration of tumor by up-regulating claudin-1 expression in colon cancer
- Wei Wei Xie, Lin Xu, Qian Li, Dao Quan Zhang, Yu Bao Zhou
- J Pathol Transl Med. 2026;60(3):307-318. Published online March 20, 2026
- DOI: https://doi.org/10.4132/jptm.2026.01.01
- 3,655 View
- 157 Download
- 1 Web of Science
-
Abstract
PDF
- Background
With the rising incidence of colon cancer, several studies have indicated that aquaporin 1 (AQP1) expression is associated with the development of colon cancer. This study aims to elucidate the potential molecular mechanisms between them. Methods: We screened data from The Cancer Genome Atlas (TCGA) database and retrospectively examined AQP1 protein expression in 127 colon cancer patients to analyze the relationship between AQP1 expression and pathological stages, prognosis. We created stable colon cancer cell lines with differential AQP1 expression, the effect of AQP1 expression on the proliferation and migration of colon cancer cells was assessed by in vitro and in vivo studies, and explored potential molecular mechanisms through Western blotting. Results: High AQP1 expression was associated with poorer survival (overall survival [OS], p = .028) in colon cancer patients from the TCGA database. Similarly, retrospective clinical data indicated that high AQP1 expression was associated with reduced disease-free survival and OS (p = .036 and p = .017, respectively). The low-expressing AQP1 colon cancer cells exhibited a decrease in proliferation and migration ability of colon cancer cells compared to the overexpressing AQP1 group (p < .05) in vitro and in vivo. Immunohistochemistry and western blotting experiments validated heightened expression of N-cadherin, vimentin, and claudin- 1 in the tumor tissues of the overexpressing AQP1 group. Conversely, reduced AQP1 expression resulted in decreased expression of claudin- 1. Conclusions: AQP1 correlates with unfavorable prognosis in colon cancer and potentially enhances the proliferation and migration of colon cancer by up-regulating claudin-1 expression.
Review Article
- Cutaneous soft tissue tumors in the 5th edition of the World Health Organization classification of skin tumors: key updates and new entities
- Joon Hyuk Choi
- J Pathol Transl Med. 2026;60(2):144-183. Published online March 13, 2026
- DOI: https://doi.org/10.4132/jptm.2026.01.09
- 9,153 View
- 395 Download
- 2 Crossref
-
Abstract
PDF
- The 5th edition of the World Health Organization (WHO) classification of skin tumors introduces a dedicated chapter on cutaneous soft tissue tumors, providing a comprehensive, standardized reference with updated diagnostic criteria that directly inform routine dermatopathology practice and molecular diagnostics. This edition incorporates several key changes, including newly recognized entities such as EWSR1::SMAD3-rearranged fibroblastic tumor, neurotrophic tyrosine receptor kinase (NTRK)–rearranged spindle cell neoplasm, superficial CD34-positive fibroblastic tumor, and CRTC1::TRIM11 cutaneous tumor. Diagnostic terminology has also been refined; for example, the term ‘atypical intradermal smooth muscle neoplasm’ replaces ‘cutaneous leiomyosarcoma’ for lesions confined to the dermis, whereas the designation leiomyosarcoma is reserved for tumors with overt subcutaneous infiltration. In addition, epithelioid fibrous histiocytoma has been reassigned to the family of tumors of uncertain differentiation. This review summarizes the key updates and newly recognized entities in the chapter on cutaneous soft tissue tumors in the 5th edition of the WHO classification of skin tumors, emphasizing their clinicopathological and molecular implications.
-
Citations
Citations to this article as recorded by- Leiomyosarcoma Involving the Calcaneum With Delayed Gastric and Sacroiliac Lesions: A Case Report
Asmita Kaur, Rajat Gupta, Harpreet Singh, Gurkirat S Bhatti
Cureus.2026;[Epub] CrossRef - Pleomorphic dermal sarcoma of the head and neck: clinical presentation, pathological features, management, and outcomes – a systematic review
Gianluca Scalia, Giuseppe Emmanuele Umana, Placido Lanza, Antonino Maniaci, Giuseppe Angelo Giovanni Lombardo, Gianluca Ferini
Oncologie.2026;[Epub] CrossRef
- Leiomyosarcoma Involving the Calcaneum With Delayed Gastric and Sacroiliac Lesions: A Case Report
Original Articles
- Deep learning–driven immunohistochemical analysis of renal lymphatics for chronic kidney disease: bioinformatic and histopathological study
- Xin Xu, YanPing Lin, Guangchang Pei, Rui Zeng, Gang Xu
- J Pathol Transl Med. 2026;60(2):220-230. Published online March 13, 2026
- DOI: https://doi.org/10.4132/jptm.2025.12.15
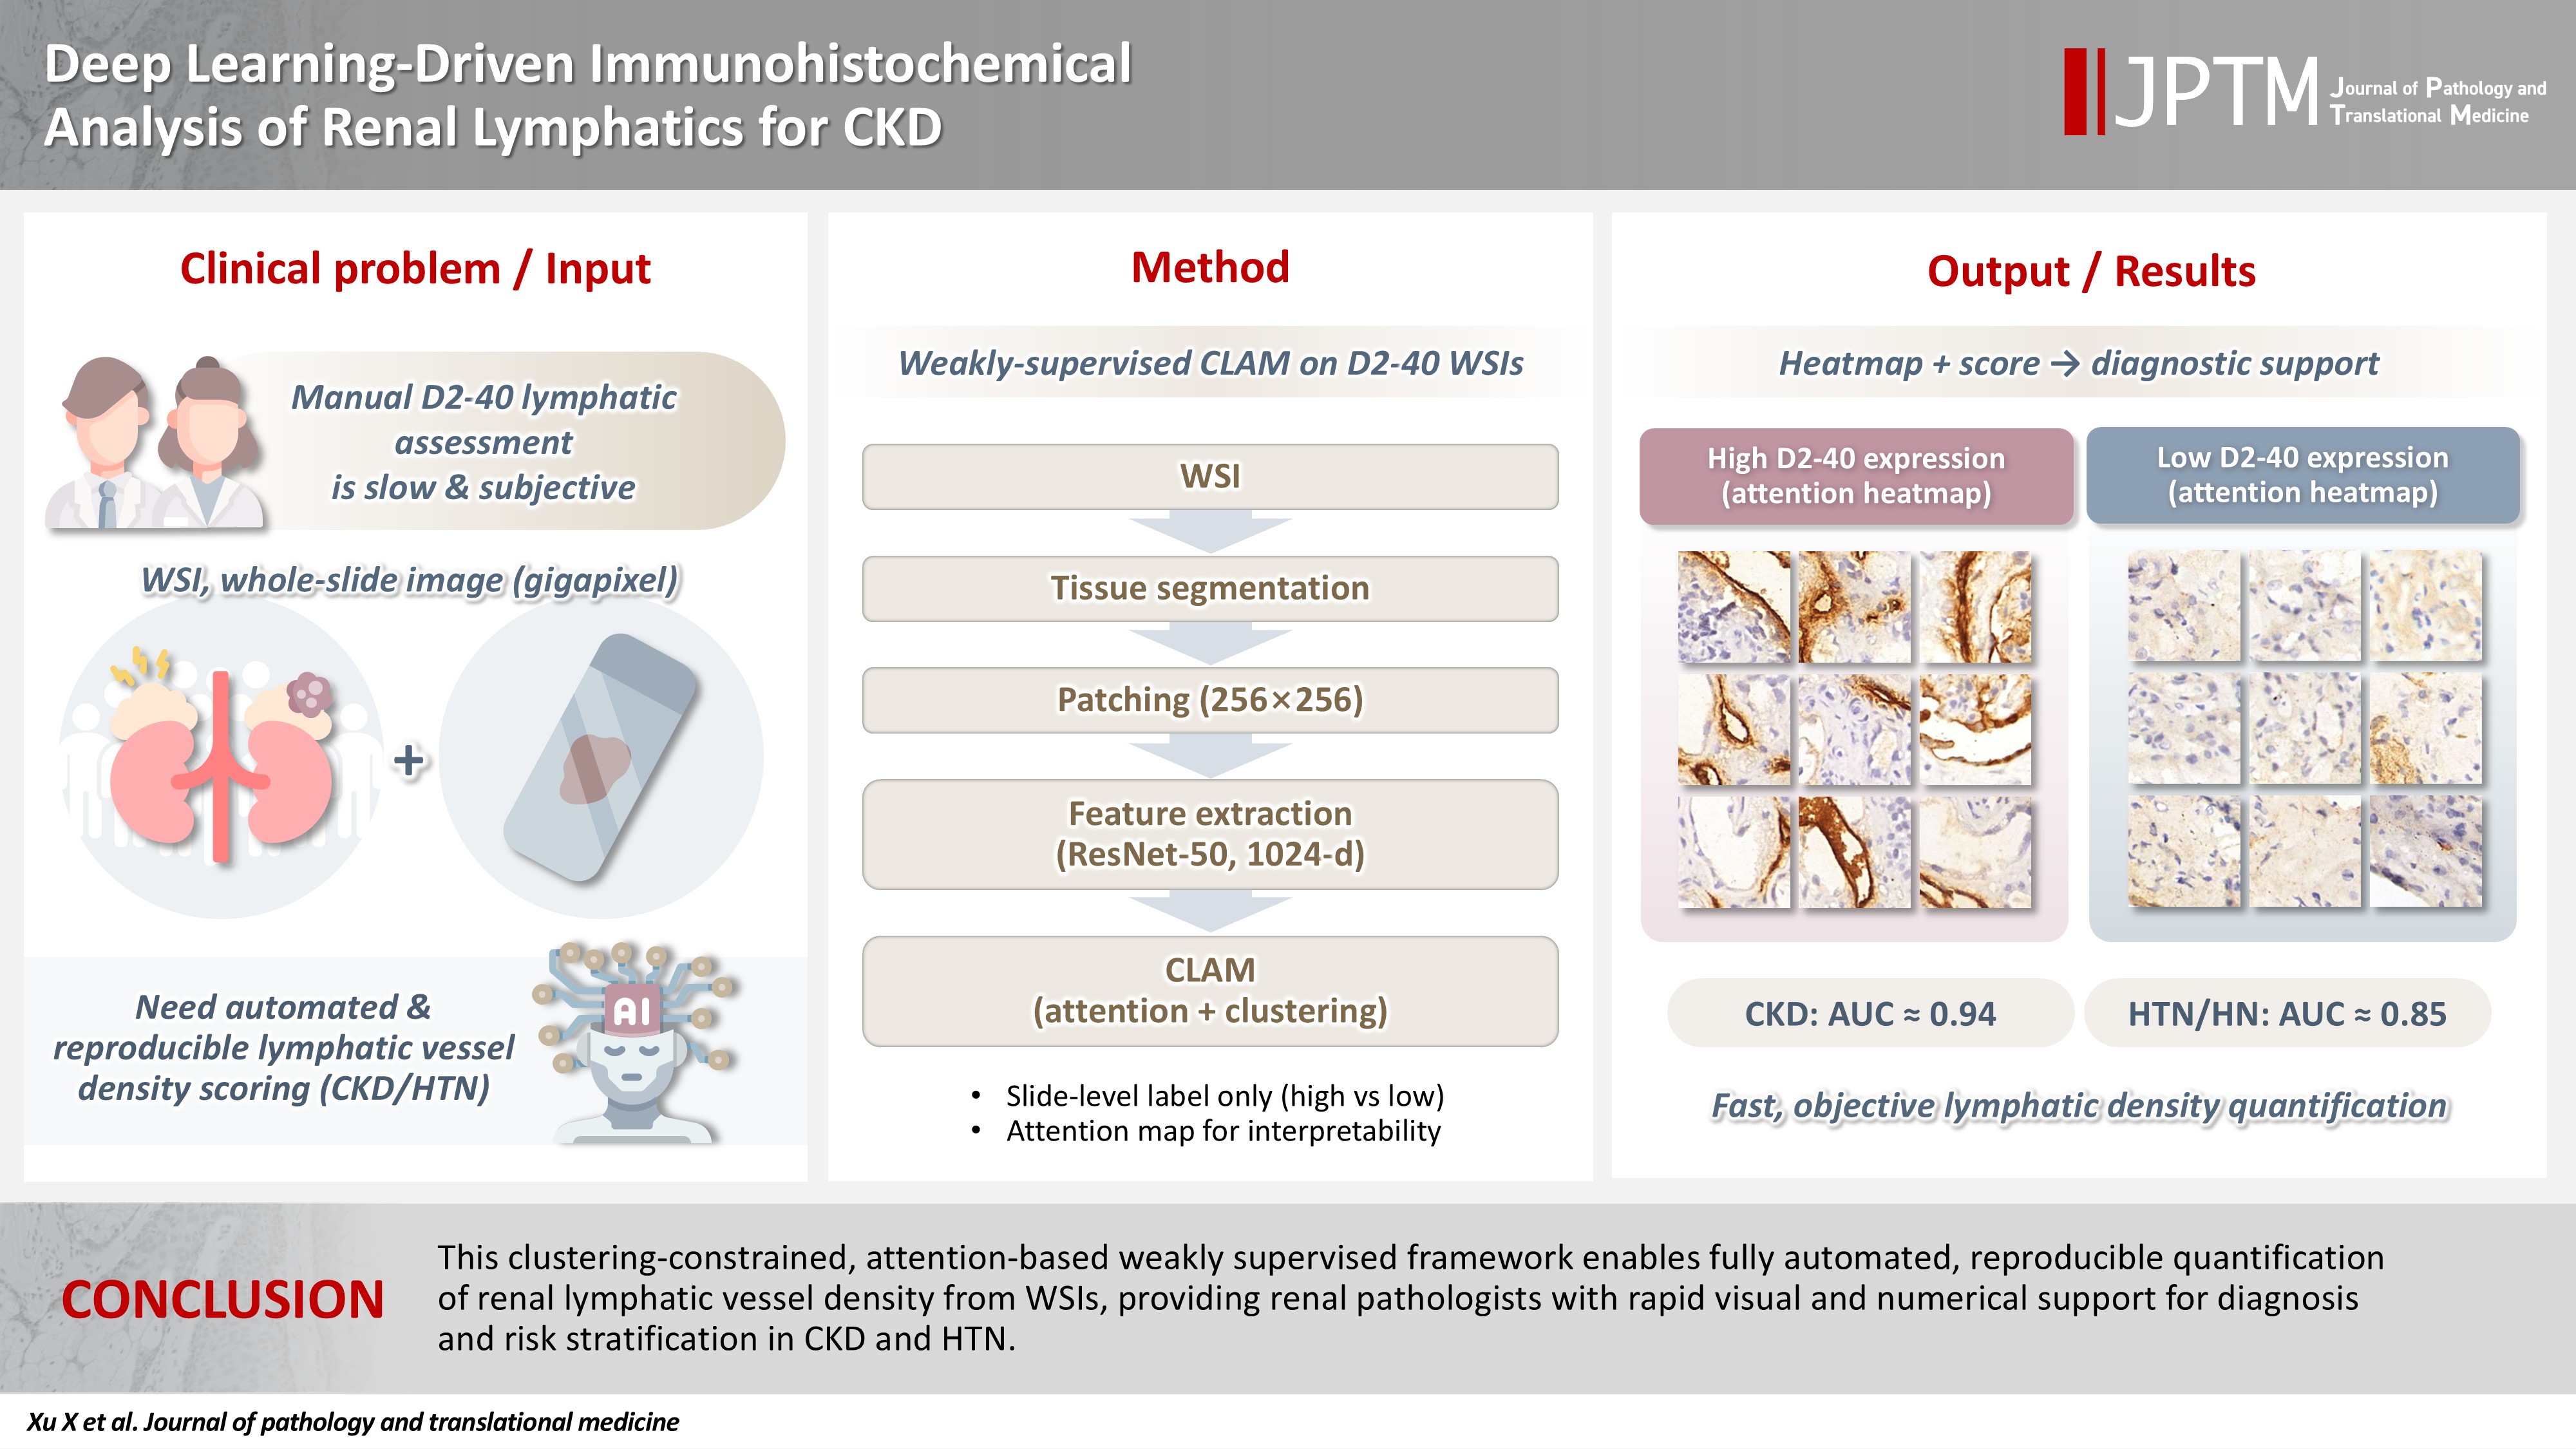
- 3,549 View
- 103 Download
- 1 Crossref
-
Abstract
PDFSupplementary Material
- Background
Renal lymphatic vessel density is clinically relevant in kidney disease but is still assessed by slow, subjective visual estimation. We evaluated a weakly supervised, attention-based multiple-instance learning framework for automated detection and quantification of renal lymphatic vessel density on D2-40-stained whole-slide images (WSIs). Methods: Two independent internal datasets from Tongji Hospital were collected, including 198 cases of chronic kidney disease (CKD) and 50 cases of hypertensive nephropathy (HTN). All biopsies were immunohistochemically stained for D2-40 and digitized as WSIs. Pathologists provided only slide-level labels (D2-40 high vs. D2-40 low). Tissue regions were automatically segmented, tiled into patches, and encoded using a pretrained convolutional neural network. Patch embeddings were then analyzed with a clustering-constrained attention multiple-instance learning (CLAM) model. Unlike conventional multiple-instance learning (MIL) methods that only weight instances, CLAM jointly performs attention-based instance selection and instance-level clustering to distinguish positive from negative evidence within each slide, yielding more discriminative slide-level features and interpretable attention maps. Performance was compared with a classic MIL model trained on the same features. Results: CLAM achieved area under the receiver operating characteristic curves of 0.942 and 0.858 on the CKD and HTN datasets, respectively, outperforming classic MIL (0.866 and 0.801). Attention maps highlighted lymphatic-rich regions consistent with renal pathologists’ assessments. Conclusions: This clustering-constrained, attention-based weakly supervised framework enables fully automated, reproducible quantification of renal lymphatic vessel density from WSIs, providing renal pathologists with rapid visual and numerical support for diagnosis and risk stratification in CKD and HTN. -
Citations
Citations to this article as recorded by- Interpreting interpretable AI in digital pathology
Zhenzhen Wang, Aleksander S. Popel, Jeremias Sulam
Patterns.2026; 7(11): 101664. CrossRef
- Interpreting interpretable AI in digital pathology
- Progastrin, annexin A2, and tumor-associated macrophages in gastric adenocarcinoma
- Konstantinos Christofidis, Rodanthi Fioretzaki, Stylianos Mavropoulos Papoudas, Nikolaos Charalampakis, Nikolaos Kavantzas, Dimitrios Schizas, Stratigoula Sakellariou
- J Pathol Transl Med. 2026;60(2):263-279. Published online March 10, 2026
- DOI: https://doi.org/10.4132/jptm.2025.12.20
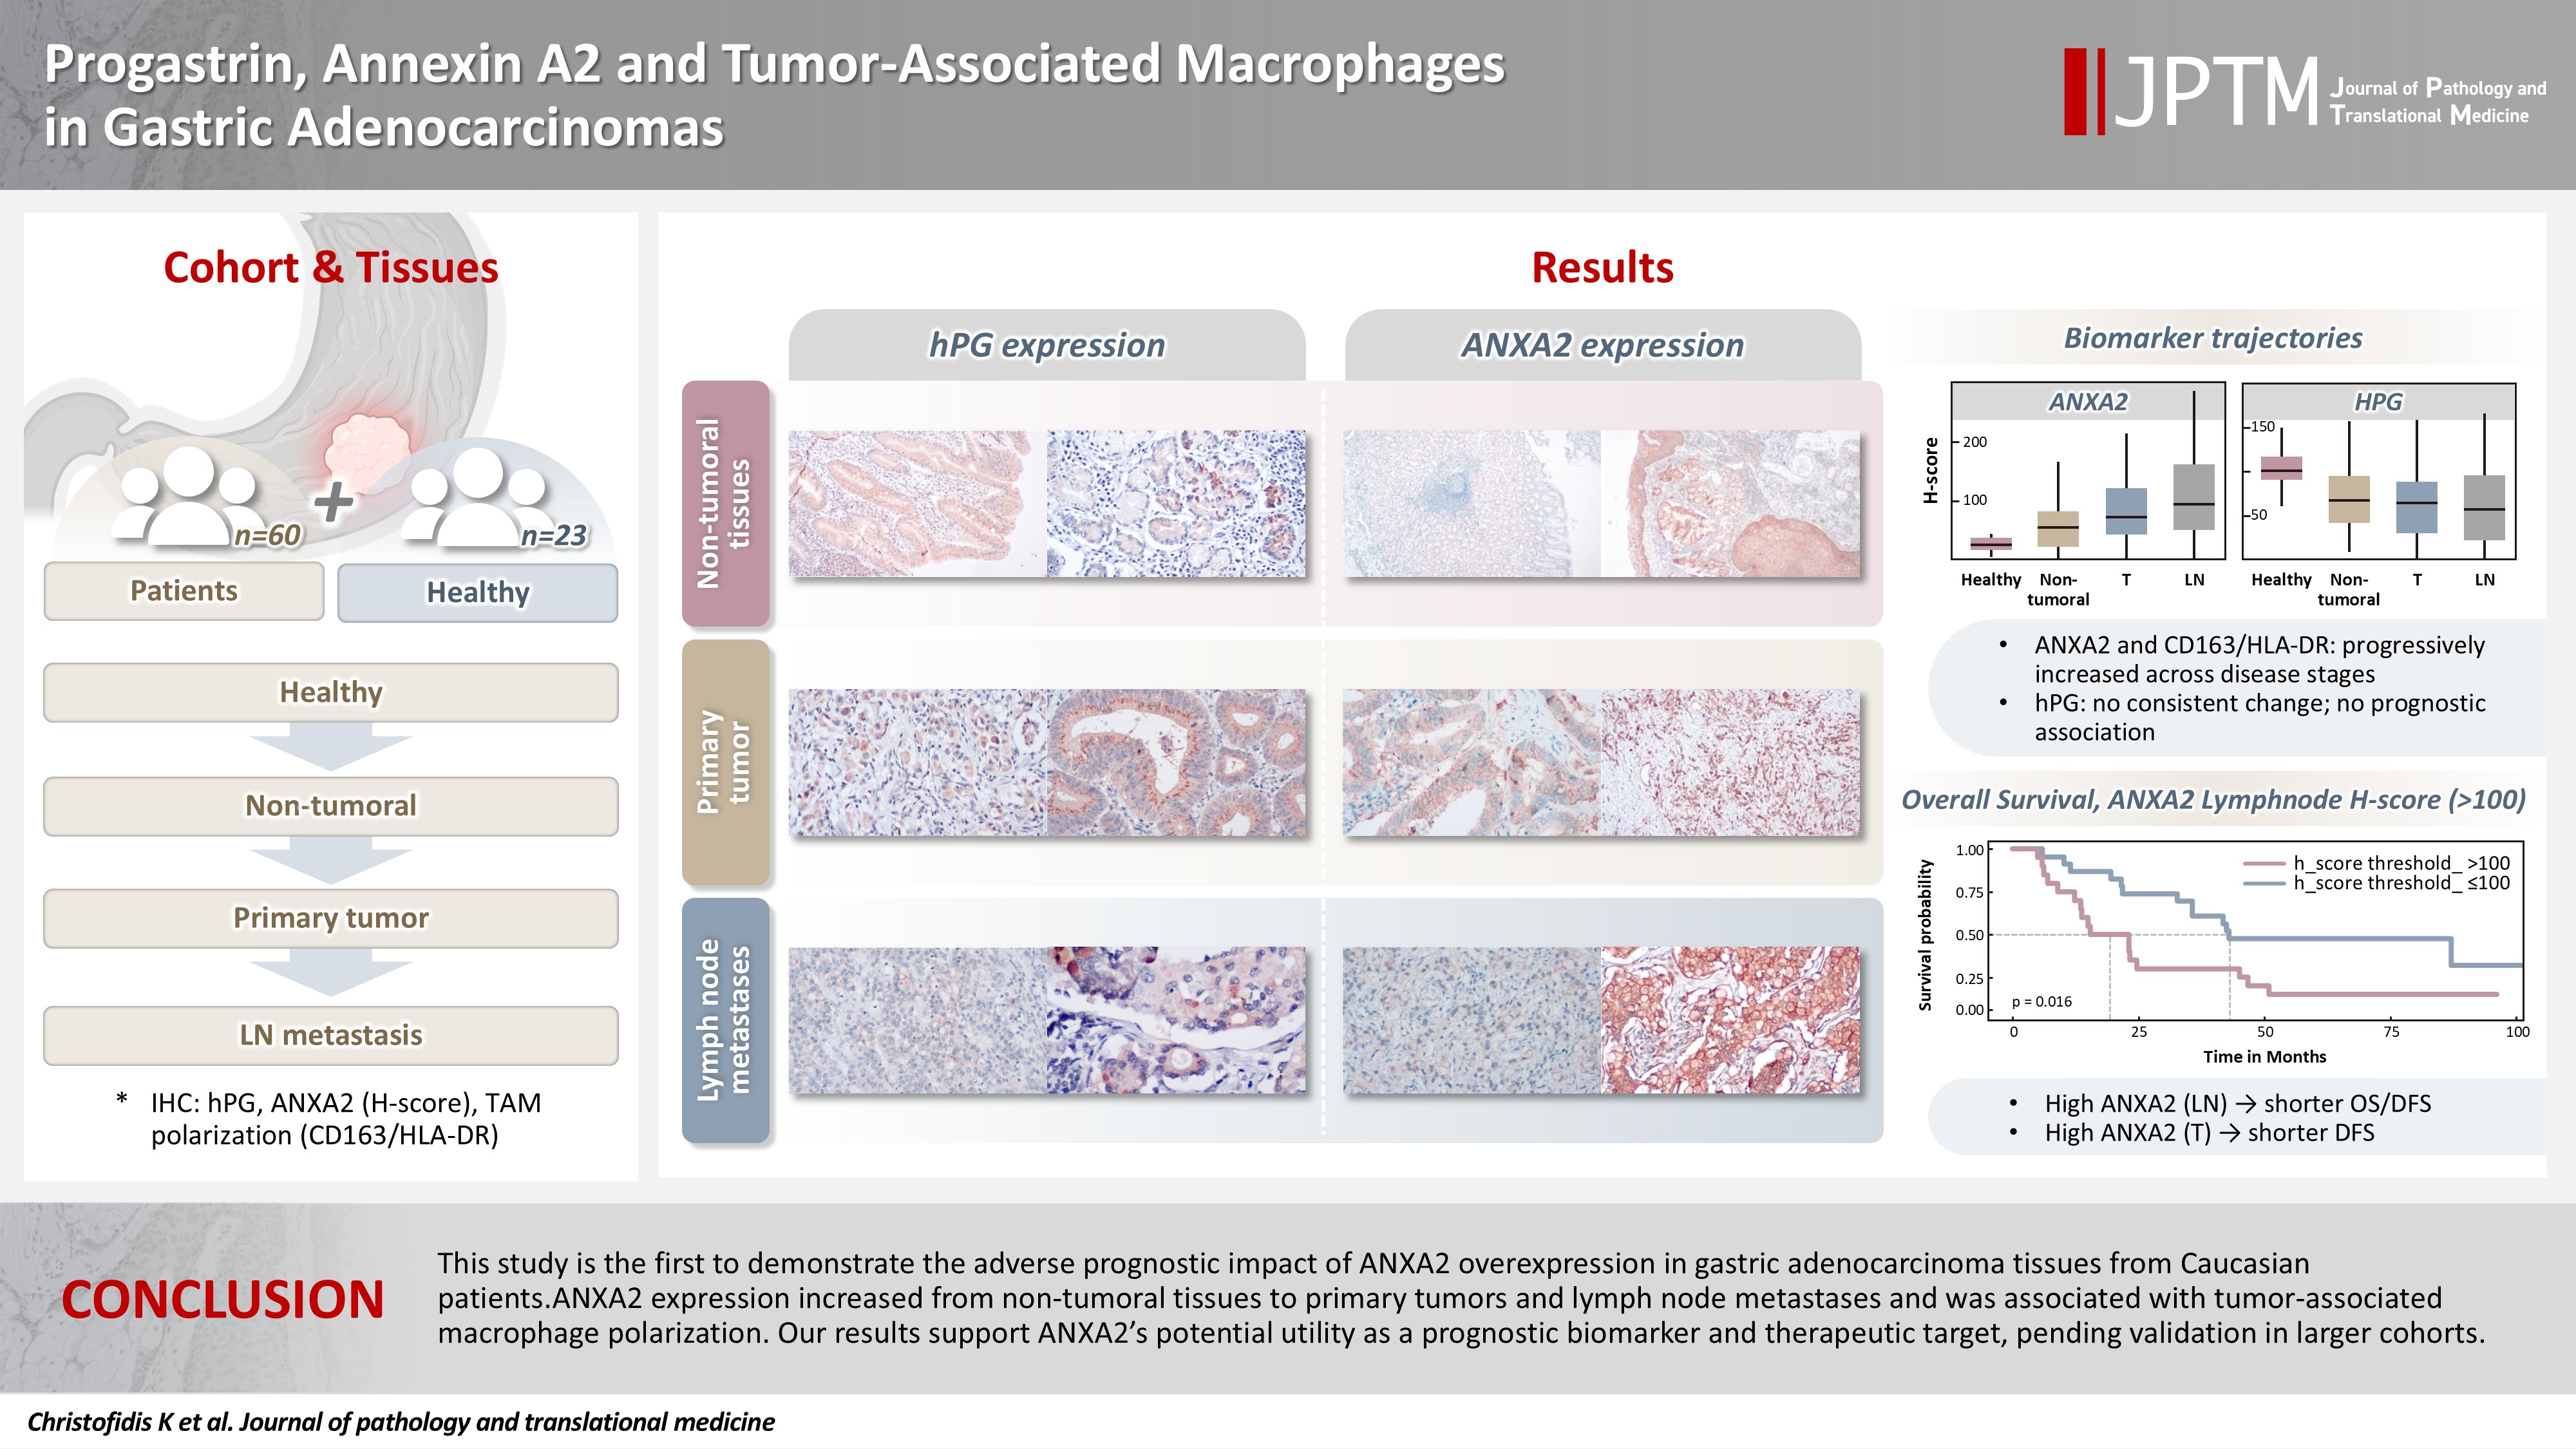
- 3,320 View
- 186 Download
-
Abstract
PDFSupplementary Material
- Background
Gastric adenocarcinoma is a major cause of cancer mortality worldwide, and reliable biomarkers remain insufficient. This study investigates the immunohistochemical expression of progastrin (hPG) and annexin A2 (ANXA2) and the polarization of tumor-associated macrophages in gastric adenocarcinoma to explore their potential prognostic and biological significance. Methods: A retrospective analysis was conducted on formalin-fixed, paraffin-embedded tissue samples from 60 patients with gastric adenocarcinoma (primary tumors, lymph node metastases, and non-tumoral gastric mucosa) and gastric biopsies from 23 healthy controls. The expression of hPG and ANXA2 was quantified using the H-score, and the CD163/human leukocyte antigen–DR (HLA-DR) ratio was used to represent macrophage polarization (M2/M1). Statistical analyses included non-parametric tests, Spearman correlations, Kaplan-Meier survival curves, and Cox proportional-hazards models. Results: ANXA2 expression was significantly elevated in cancer cells from primary tumors and lymph node metastases, compared with the non-tumoral gastric mucosa tissues and gastric mucosa tissues from healthy controls. ANXA2 expression increased with the tumor grade. High ANXA2 levels were associated with shorter overall and disease-free survival, but they did not have independent prognostic value. Although hPG expression correlated positively with ANXA2, it showed no significant prognostic association. The CD163/HLA-DR ratio increased with tumor progression and negatively correlated with ANXA2, but it did not influence survival outcomes. Conclusions: This study is the first to demonstrate the adverse prognostic impact of ANXA2 overexpression in gastric adenocarcinoma tissues from Caucasian patients. Our results suggest that ANXA2 might have utility as a prognostic biomarker and therapeutic target, if further large-scale studies validate and expand our findings.
- 3-Dimensional reconstruction reveals frequent intraluminal growth of submucosal veins in surgically resected pT1 colorectal cancers
- Jihyun Park, Mi-Ju Kim, Yeon Wook Kim, Byong-Wook Lee, Junyoung Shin, Jinho Shin, Chan-Gi Pack, Dong-Hoon Yang, Jihun Kim, In Ja Park, Ralph H. Hruban, Seung-Mo Hong
- J Pathol Transl Med. 2026;60(2):246-262. Published online March 10, 2026
- DOI: https://doi.org/10.4132/jptm.2025.12.19
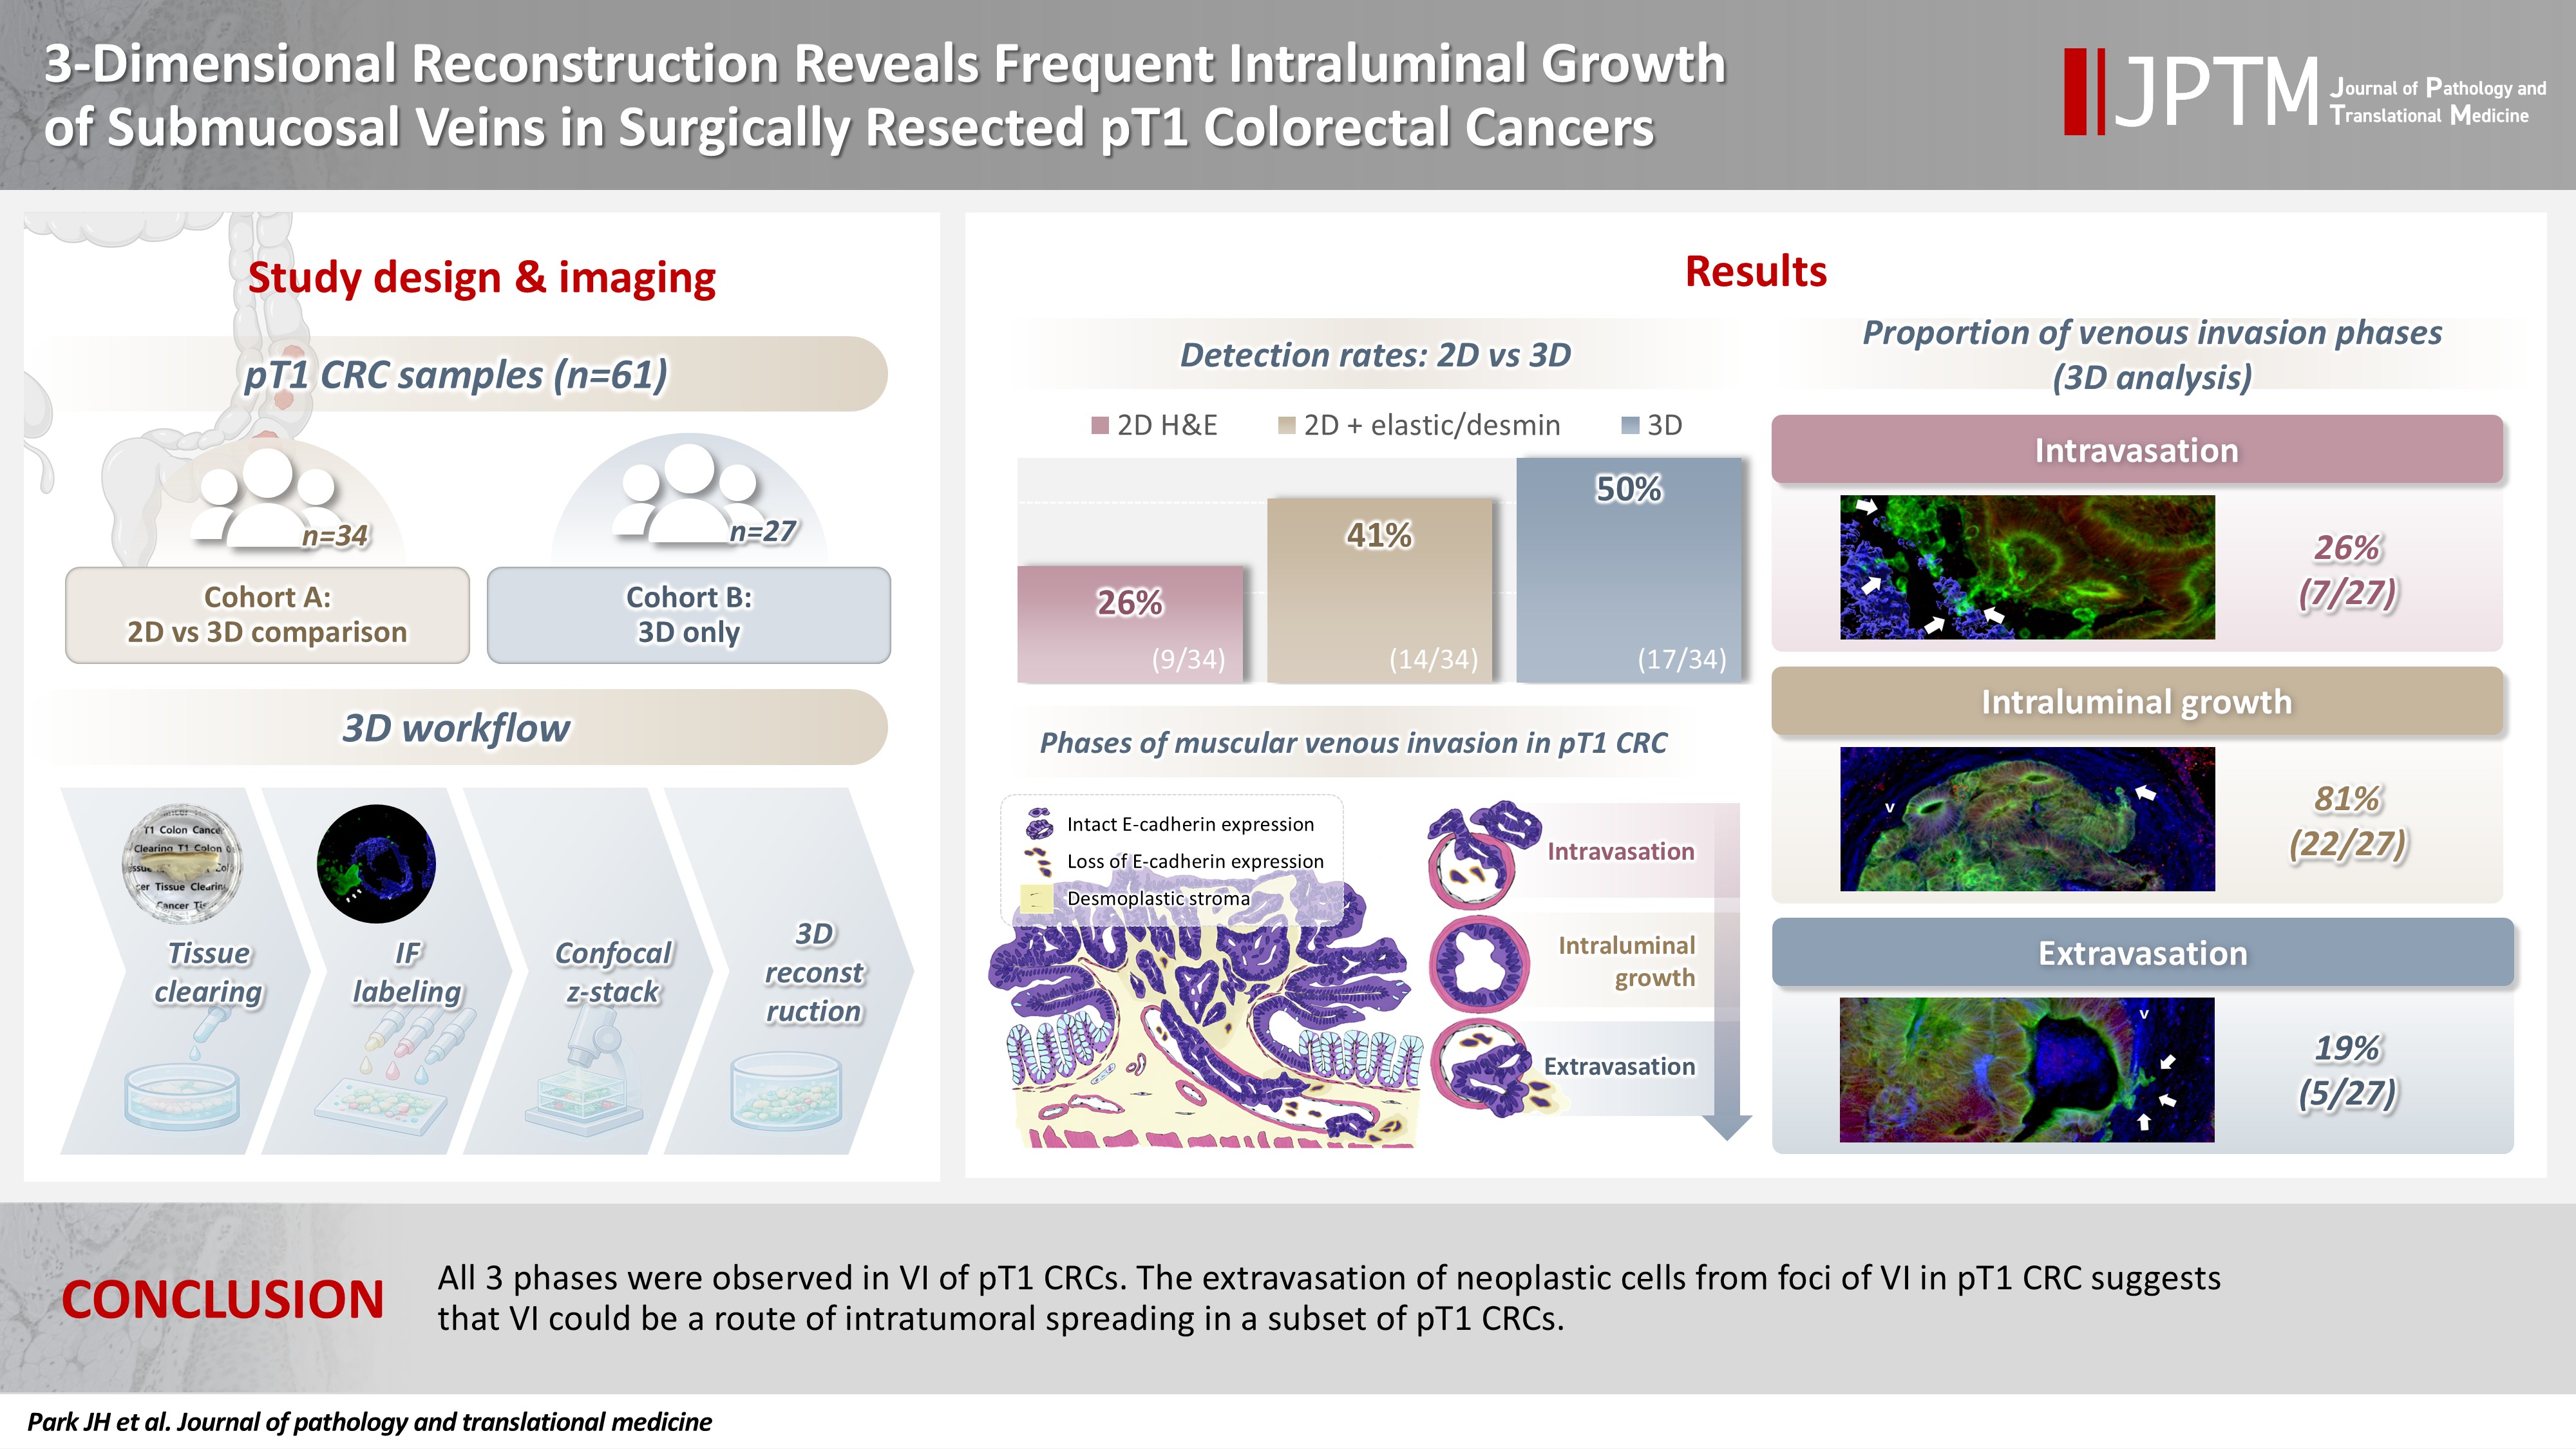
- 2,776 View
- 114 Download
-
Abstract
PDF
- Background
Although venous invasion (VI) is associated with distant metastasis and observed in >50% of pT2–4 colorectal cancers (CRCs), the role of VI in pT1 CRCs is not well-defined. Methods: Thirty-four surgically resected pT1 CRCs were reevaluated for 2-dimensional (2D) VI using hematoxylin and eosin (H&E)–stained slides with additional elastic and desmin immunohistochemical staining (cohort A). Additionally, 27 pT1 CRCs without knowing VI status were selected for 3-dimensional (3D) VI evaluation only (cohort B). All 61 cases (cohorts A and B) were studied in 3D using tissue clearing. Results: VI was detected more commonly in 3D (17/34, 50.0%) than in 2D H&E slide evaluation (9/34, 26.5%, p = .047). When VI was identified in 3D (27/61, 44.3%), the most common phase was that of intraluminal growth (22/27, 81.5%), followed by intravasation (7/27, 25.9%) and extravasation (5/27, 18.5%). E-cadherin expression was characterized in 3D in foci of VI and varied in each phase of invasion. Conclusions: All three phases were observed in VI of pT1 CRCs. The extravasation of neoplastic cells from foci of VI in pT1 CRC suggests that VI could be a route of intratumoral spreading in a subset of pT1 CRCs.
- Can micro-CT distinguish between solid lung tumors? A comparative evaluation including solid adenocarcinoma, non-keratinizing squamous cell carcinoma, and carcinoid tumor
- Selim Sevim, Serpil Dizbay Sak, Kaan Orhan, Arda Buyuksungur, Duru Karasoy, Hilal Ozakinci, Ayten Kayi Cangir
- J Pathol Transl Med. 2026;60(2):231-245. Published online March 10, 2026
- DOI: https://doi.org/10.4132/jptm.2025.12.16
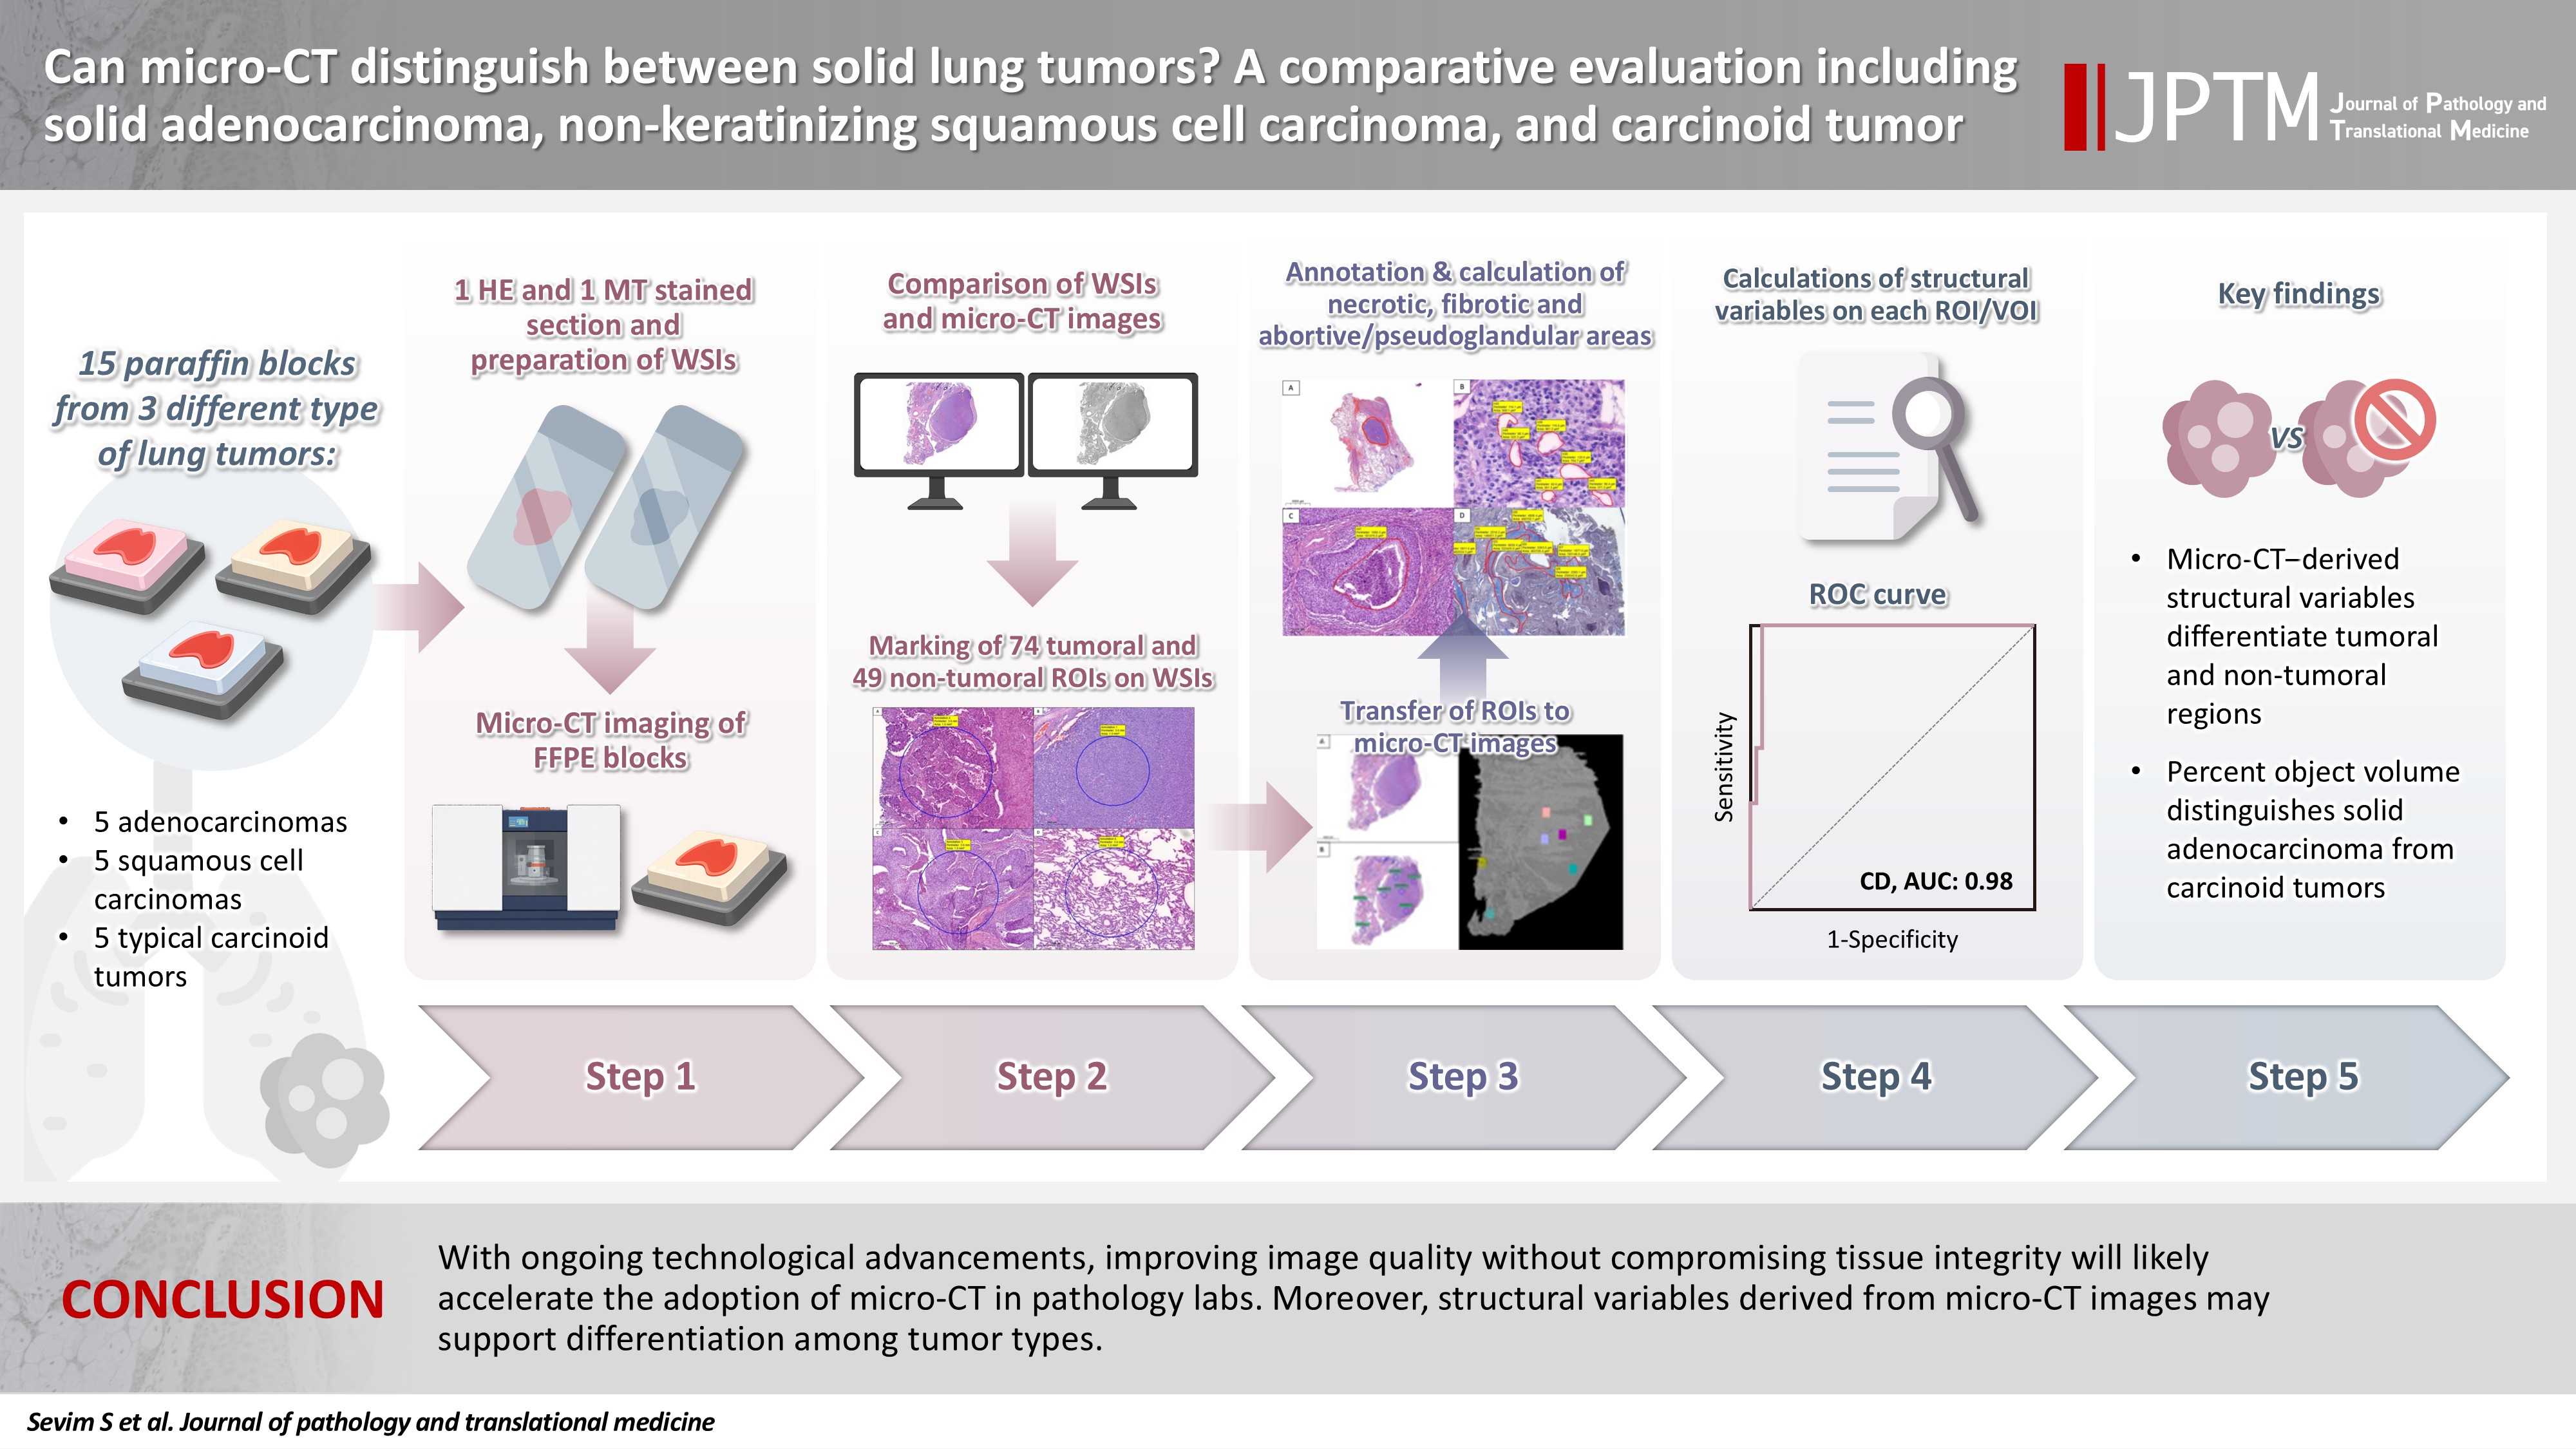
- 2,849 View
- 133 Download
-
Abstract
PDFSupplementary Material
- Background
Some pulmonary carcinomas display a solid pattern, and immunohistochemistry is commonly used for tumor differentiation. Micro–computed tomography (micro-CT), with its ability to produce detailed three-dimensional images using small voxel sizes, may offer additional insights. This study investigates whether three solid tumor types, solid adenocarcinoma (sAC), non-keratinizing squamous cell carcinoma, and carcinoid tumor (CaT), can be differentiated using micro-CT. Methods: Fifteen paraffin blocks, five for each type, were scanned with micro-CT (Skyscan 1275, Bruker). These images were compared to whole slide images (WSIs) of the same tumors. Consequently, tumoral (n = 74) and non-tumoral (n = 49) regions of interest (tumor ROIs [tROIs] and non-tumor ROIs [ntROIs]) were selected on the micro-CT images and evaluated in terms of certain structural variables (percent object volume, structure model index, structure thickness, structure linear density, connectivity, connectivity density, open porosity, closed porosity) to investigate whether tumors can be differentiated from normal parenchyma and from each other. Results: Although detailed images comparable to WSIs could not be obtained, it was considered an important advantage to be able to examine the entire depth of the paraffin blocks. tROIs and ntROIs could be distinguished based on all variables (p < .001). Additionally, sAC showed a notable difference from CaT in “percent object volume” (p = .011). Conclusions: With ongoing technological advancements, improving image quality without compromising tissue integrity will likely accelerate the adoption of micro-CT in pathology labs. Moreover, structural variables derived from micro-CT images may support differentiation among tumor types.
- Correlation between HER2 gene copy number and immunohistochemistry categories in HER2-negative breast cancer: diagnostic utility for differentiating HER2-null, ultralow, and low tumors
- Min Chong Kim, Young Kyung Bae
- J Pathol Transl Med. 2026;60(2):193-201. Published online February 25, 2026
- DOI: https://doi.org/10.4132/jptm.2025.11.07

- 4,063 View
- 229 Download
- 1 Web of Science
- 1 Crossref
-
Abstract
PDF
- Background
The recent recognition of human epidermal growth factor receptor 2 (HER2)–low and HER2-ultralow breast cancers (BCs) has expanded the therapeutic relevance of HER2 testing in the antibody-drug conjugate era. However, the biological continuum of HER2 expression measured by immunohistochemistry (IHC) and its relationship with the HER2 gene copy number remain unclear. Methods: We retrospectively analyzed 135 HER2-negative invasive BCs and reclassified them as HER2-null (IHC 0), HER2-ultralow (0+), or HER2-low (1+ or 2+ without amplification). HER2 gene copy number was determined using silver-enhanced in situ hybridization. Statistical analyses were performed to compare HER2 copy number among IHC categories and evaluate the discriminatory value of HER2 copy number for distinguishing IHC subgroups. Results: The mean HER2 copy number increased stepwise across IHC categories: 1.95 ± 0.54 (null), 2.03 ± 0.43 (ultralow), 2.25 ± 0.65 (low, 1+), and 3.29 ± 1.05 (low, 2+). Significant differences were observed between the ultralow and low groups (p = .003) and between the null and low groups (p < .001), but not between the null and ultralow groups or between the ultralow and 1+ groups. Conclusions: HER2 gene copy number was positively correlated with protein expression as reflected by IHC categories. Although HER2 gene copy number was statistically higher in HER2-low than in HER2-null tumors, the substantial overlap in copy number ranges likely limits its utility in distinguishing HER2-low from HER2- null BCs. -
Citations
Citations to this article as recorded by- HER2-Low Breast Cancer: A Review of Epidemiology, Diagnostic Challenges, Targeted Therapies, and Clinical Outcomes
Maedeh Mirasheh, Zahra Shahabinia, Mai Abdel Haleem A. Abusalah, Afrooz Mazidimoradi, Leila Allahqoli, Hamid Salehiniya, Do-Youn Lee
Journal of Clinical Medicine.2026; 15(19): 7559. CrossRef
- HER2-Low Breast Cancer: A Review of Epidemiology, Diagnostic Challenges, Targeted Therapies, and Clinical Outcomes
- Mutational status of non-invasive follicular thyroid neoplasm with papillary-like nuclear features (NIFTP): molecular analysis should be performed for NIFTPs with nuclear score 3
- Ayaka Sako, Mitsuyoshi Hirokawa, Michiko Matsuse, Miyoko Higuchi, Akira Miyauchi, Takashi Akamizu, Atsushi Kawakami, Norisato Mitsutake
- J Pathol Transl Med. 2026;60(2):214-219. Published online February 23, 2026
- DOI: https://doi.org/10.4132/jptm.2025.12.06
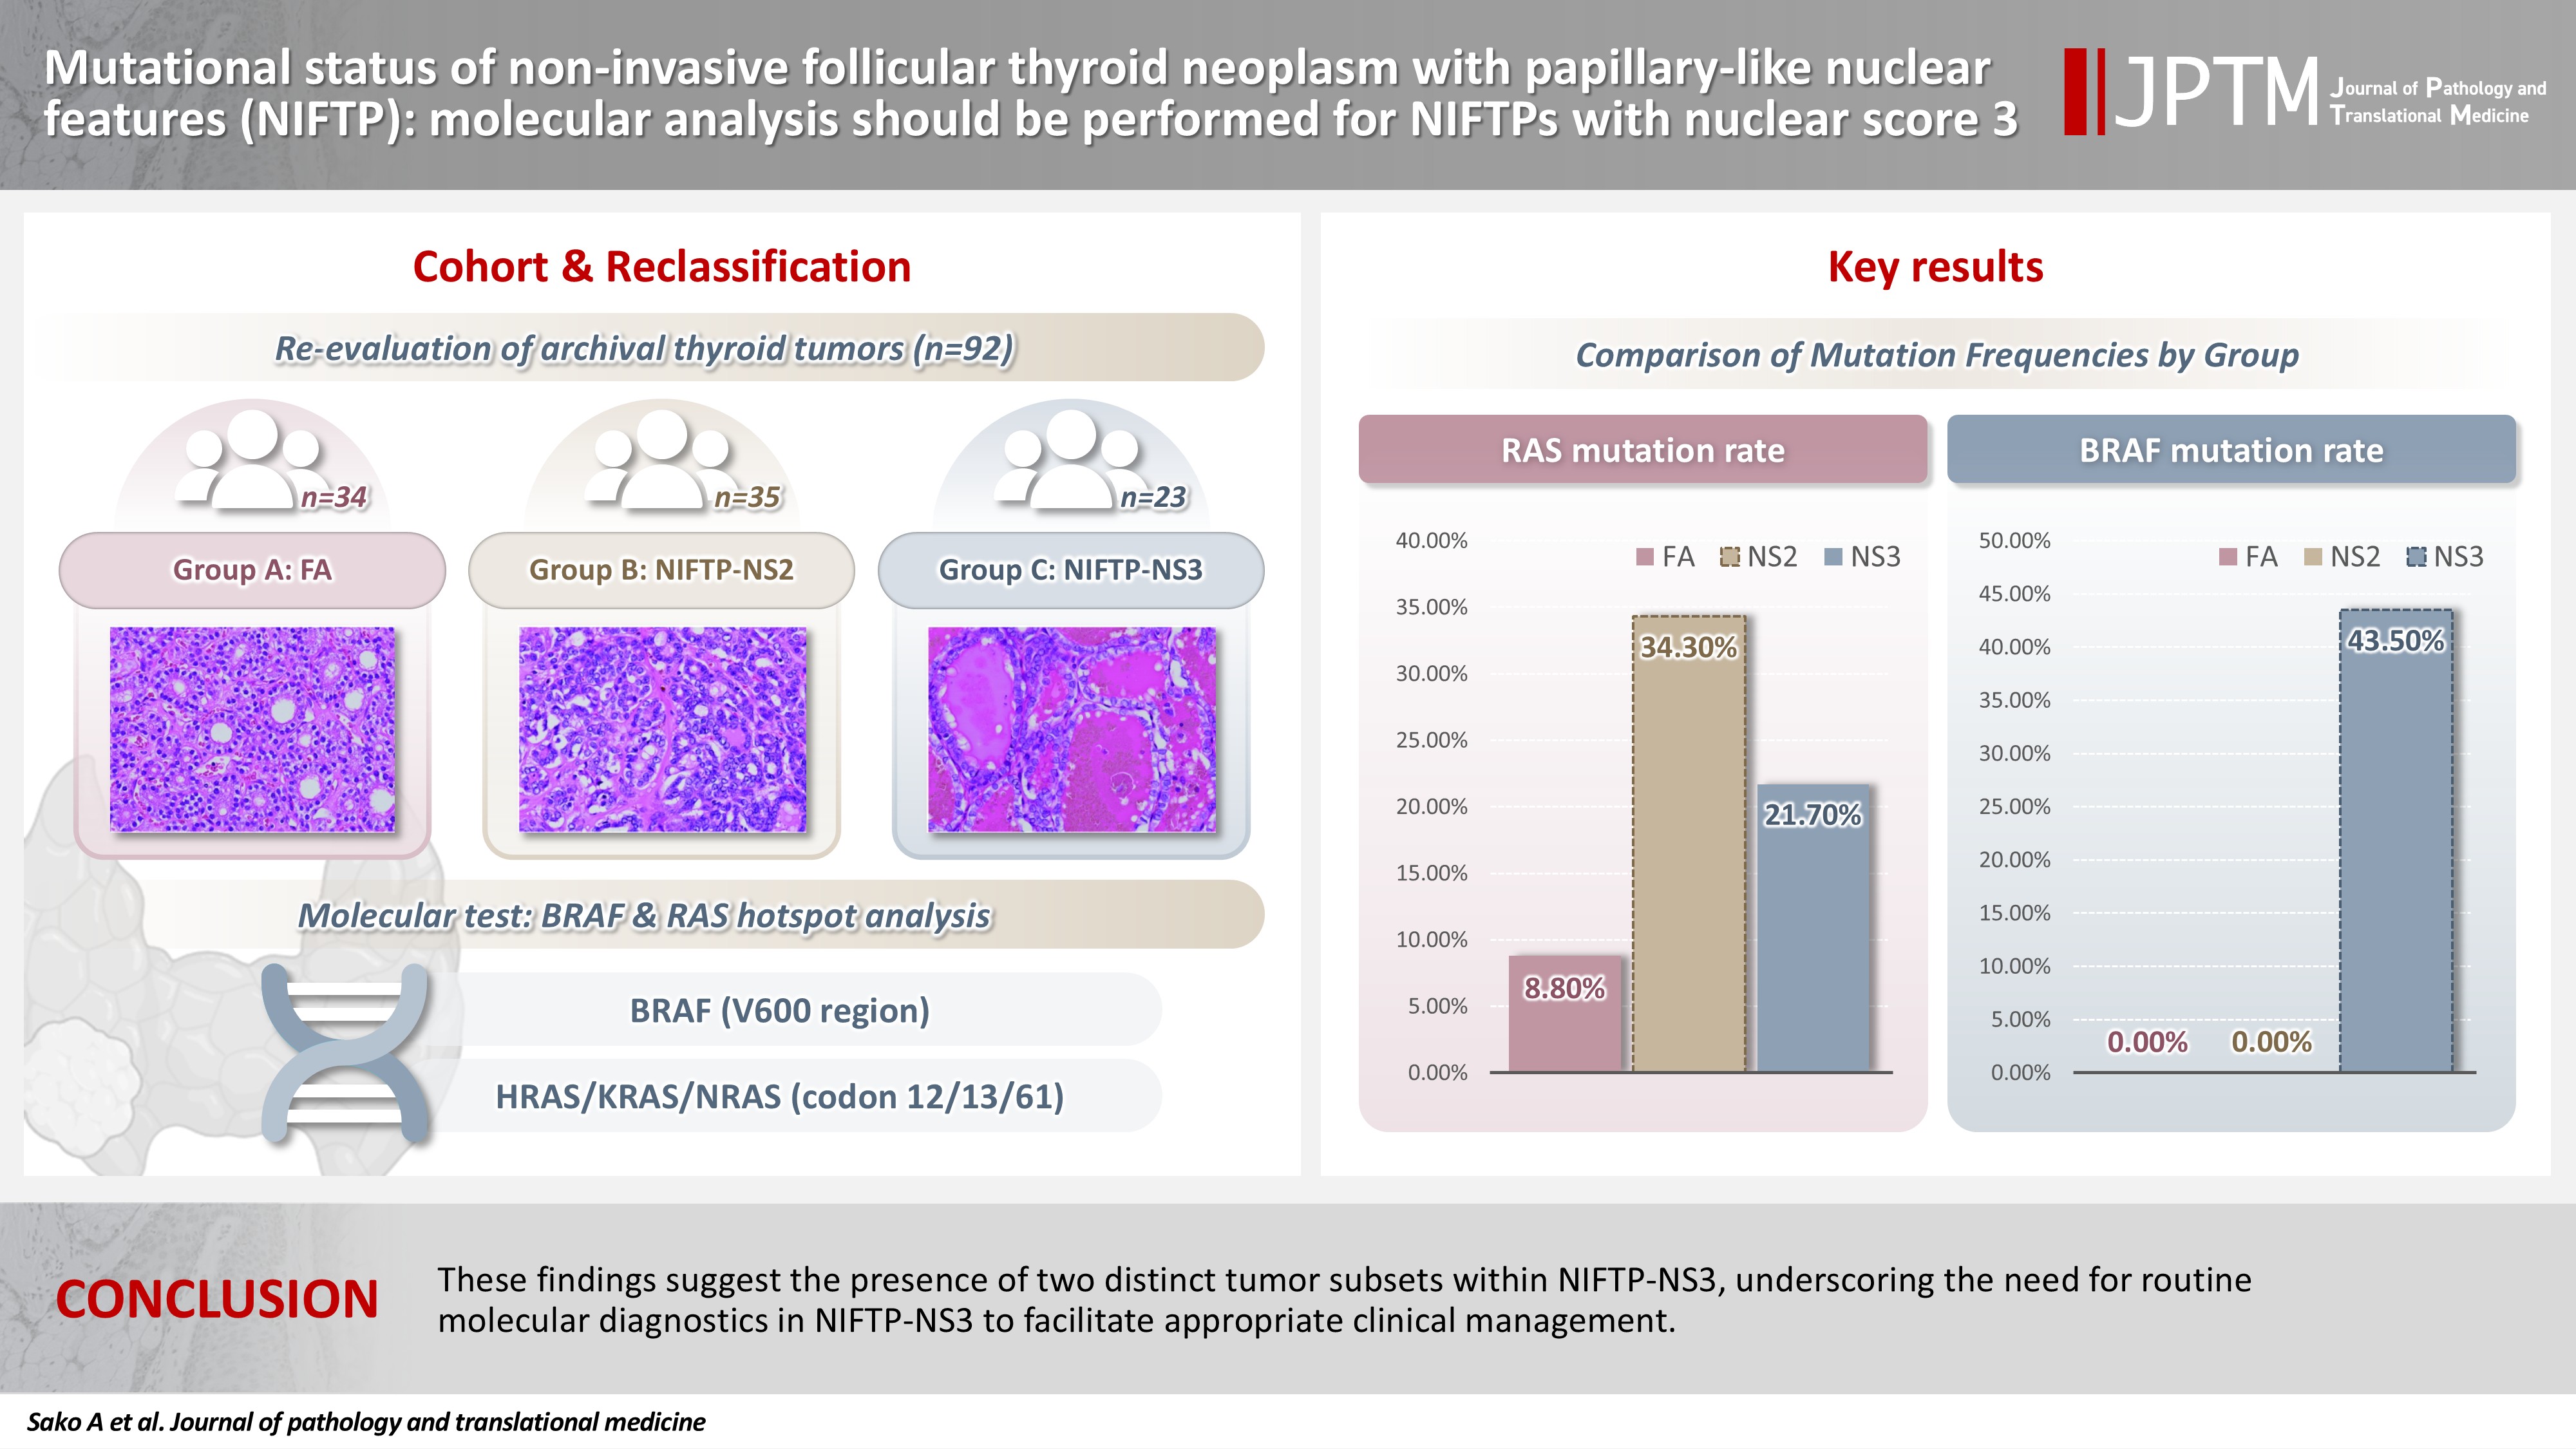
- 3,500 View
- 274 Download
- 1 Crossref
-
Abstract
PDF
- Background
The classification of non-invasive follicular thyroid neoplasm with papillary-like nuclear features (NIFTP) was introduced to prevent the overtreatment of indolent tumors that were formerly diagnosed as non-invasive encapsulated follicular variant papillary thyroid carcinomas (NIEFV-PTCs). Although NIFTP was initially estimated to account for 10%–20% of papillary thyroid carcinomas in Western populations, its incidence is substantially lower in Asian cohorts. However, a multi-institutional Japanese study revealed that 31.0% of tumors previously diagnosed as follicular adenomas (FAs) were reclassified as NIFTPs. NIFTP diagnosis requires a nuclear score (NS) of 2–3, and according to the recent World Health Organization criteria, molecular analysis is recommended, but not mandatory, to exclude high-risk subtypes, namely cases with the BRAFV600E mutation, particularly for NS3 tumors. Methods: We performed genetic analysis on 92 archival thyroid tumor samples, including 69 previously diagnosed as FA, of which 34 remained as FA upon re-evaluation (group A) and 35 were reclassified as NIFTP with NS2 (group B). Additional 23 tumors previously diagnosed as NIEFV-PTC were reclassified as NIFTP with NS3 (group C). Results: RAS mutations were detected in 8.8%, 34.3%, and 21.7% of the tumor samples in groups A, B, and C, respectively, whereas BRAF mutations were present in 43.5% of the tumor samples in group C only. Conclusions: These findings suggest the presence of two distinct tumor subsets within NIFTP-NS3, underscoring the need for routine molecular diagnostics in NIFTP-NS3 to facilitate appropriate clinical management. -
Citations
Citations to this article as recorded by- Synchronous Differentiated Thyroid Carcinoma in Non-Invasive Follicular Thyroid Neoplasm with Papillary-like Nuclear Features (NIFTP): Prevalence, Pathological Profile, and Limits of Pre-Operative Risk Prediction in a Multicentre Cohort
Chiara Dobrinja, Manuela Mastronardi, Stella Bernardi, Elena Bonati, Marco Bononi, Pietro Giorgio Calò, Gian Luigi Canu, Federico Cappellacci, Maria Grazia Chiofalo, Loredana De Pasquale, Carmela De Crea, Marco Stefano Demarchi, Paolo Del Rio, Giacomo Di
Cancers.2026; 18(21): 3505. CrossRef
- Synchronous Differentiated Thyroid Carcinoma in Non-Invasive Follicular Thyroid Neoplasm with Papillary-like Nuclear Features (NIFTP): Prevalence, Pathological Profile, and Limits of Pre-Operative Risk Prediction in a Multicentre Cohort
 First
 Prev




