
 E-submission

Articles
- Page Path
- HOME > J Pathol Transl Med > Forthcoming articles > Article
-
Case Study
Meningioma harboring IDH1 R132H mutation: a case report -
Soyeon Ahn1
 , Chung Lee1, Jong-Pil Park2, Se Hoon Kim1
-
DOI: https://doi.org/10.4132/jptm.2026.08.19
Published online: November 3, 2026
1Department of Pathology, Yonsei University College of Medicine, Seoul, Korea
2Department of Forensic Medicine, Yonsei University College of Medicine, Seoul, Korea
- Corresponding Author: Se Hoon Kim, MD, PhD Department of Pathology, Yonsei University College of Medicine, 50-1 Yonsei-ro, Seodaemun-gu, Seoul 03722, Korea Tel: +82-2-2228-1769, Fax: +82-2-362-0860, E-mail: paxco@yuhs.ac
© The Korean Society of Pathologists/The Korean Society for Cytopathology
This is an Open Access article distributed under the terms of the Creative Commons Attribution Non-Commercial License (https://creativecommons.org/licenses/by-nc/4.0) which permits unrestricted non-commercial use, distribution, and reproduction in any medium, provided the original work is properly cited.
- 76 Views
- 3 Download


Abstract
- Meningiomas are the most common primary central nervous system tumors. Monosomy of chromosome 22 is the most frequently reported genetic abnormality in meningioma and the occurrence of IDH1 mutations in meningioma is exceedingly rare. We report an uncommon case of IDH1 R132H-mutant meningioma. A 69-year-old man presented with two intracranial masses, one of which was identified as an IDH1 R132H-mutant meningioma by next-generation sequencing and further confirmed by pyrosequencing and immunohistochemistry. The rarity of this molecular finding and the potentially favorable prognosis observed in previously reported cases highlight the need for its recognition as a distinct molecular subset. Isocitrate dehydrogenase–targeted therapy may represent a future therapeutic option, pending validation through prospective studies and larger case series.
- Meningiomas are the most common primary central nervous system tumors with an incidence rate of 8.58 per 100,000 [1]. Monosomy of chromosome 22 is the most frequently reported genetic abnormality in meningioma and roughly 50% of meningiomas have allelic losses in 22q12.2, a region encoding the NF2 gene [2]. A second, NF2-wildtype subset is instead characterized by a recurrent oncogenic AKT1 mutation (p.E17K), along with alterations in TRAF7, KLF4, SMO [3], and PIK3CA [4]. Higher-grade meningiomas exhibit more complex genetic changes, with losses on 1p, 6p/q, 10q, 14q, and 18p/q—and, less frequently, on 2p/q, 3p, 4p/q, 7p, and 8p/q—as well as heterozygous or homozygous deletion of CDKN2A and/or CDKN2B [5]. In contrast, IDH1/2 mutations, which are hallmark drivers of diffuse gliomas, are exceedingly rare in meningiomas. A case of meningioma with IDH1 R132H mutation and further discuss its clinicopathologic and molecular implications in the context of the existing literature.
INTRODUCTION
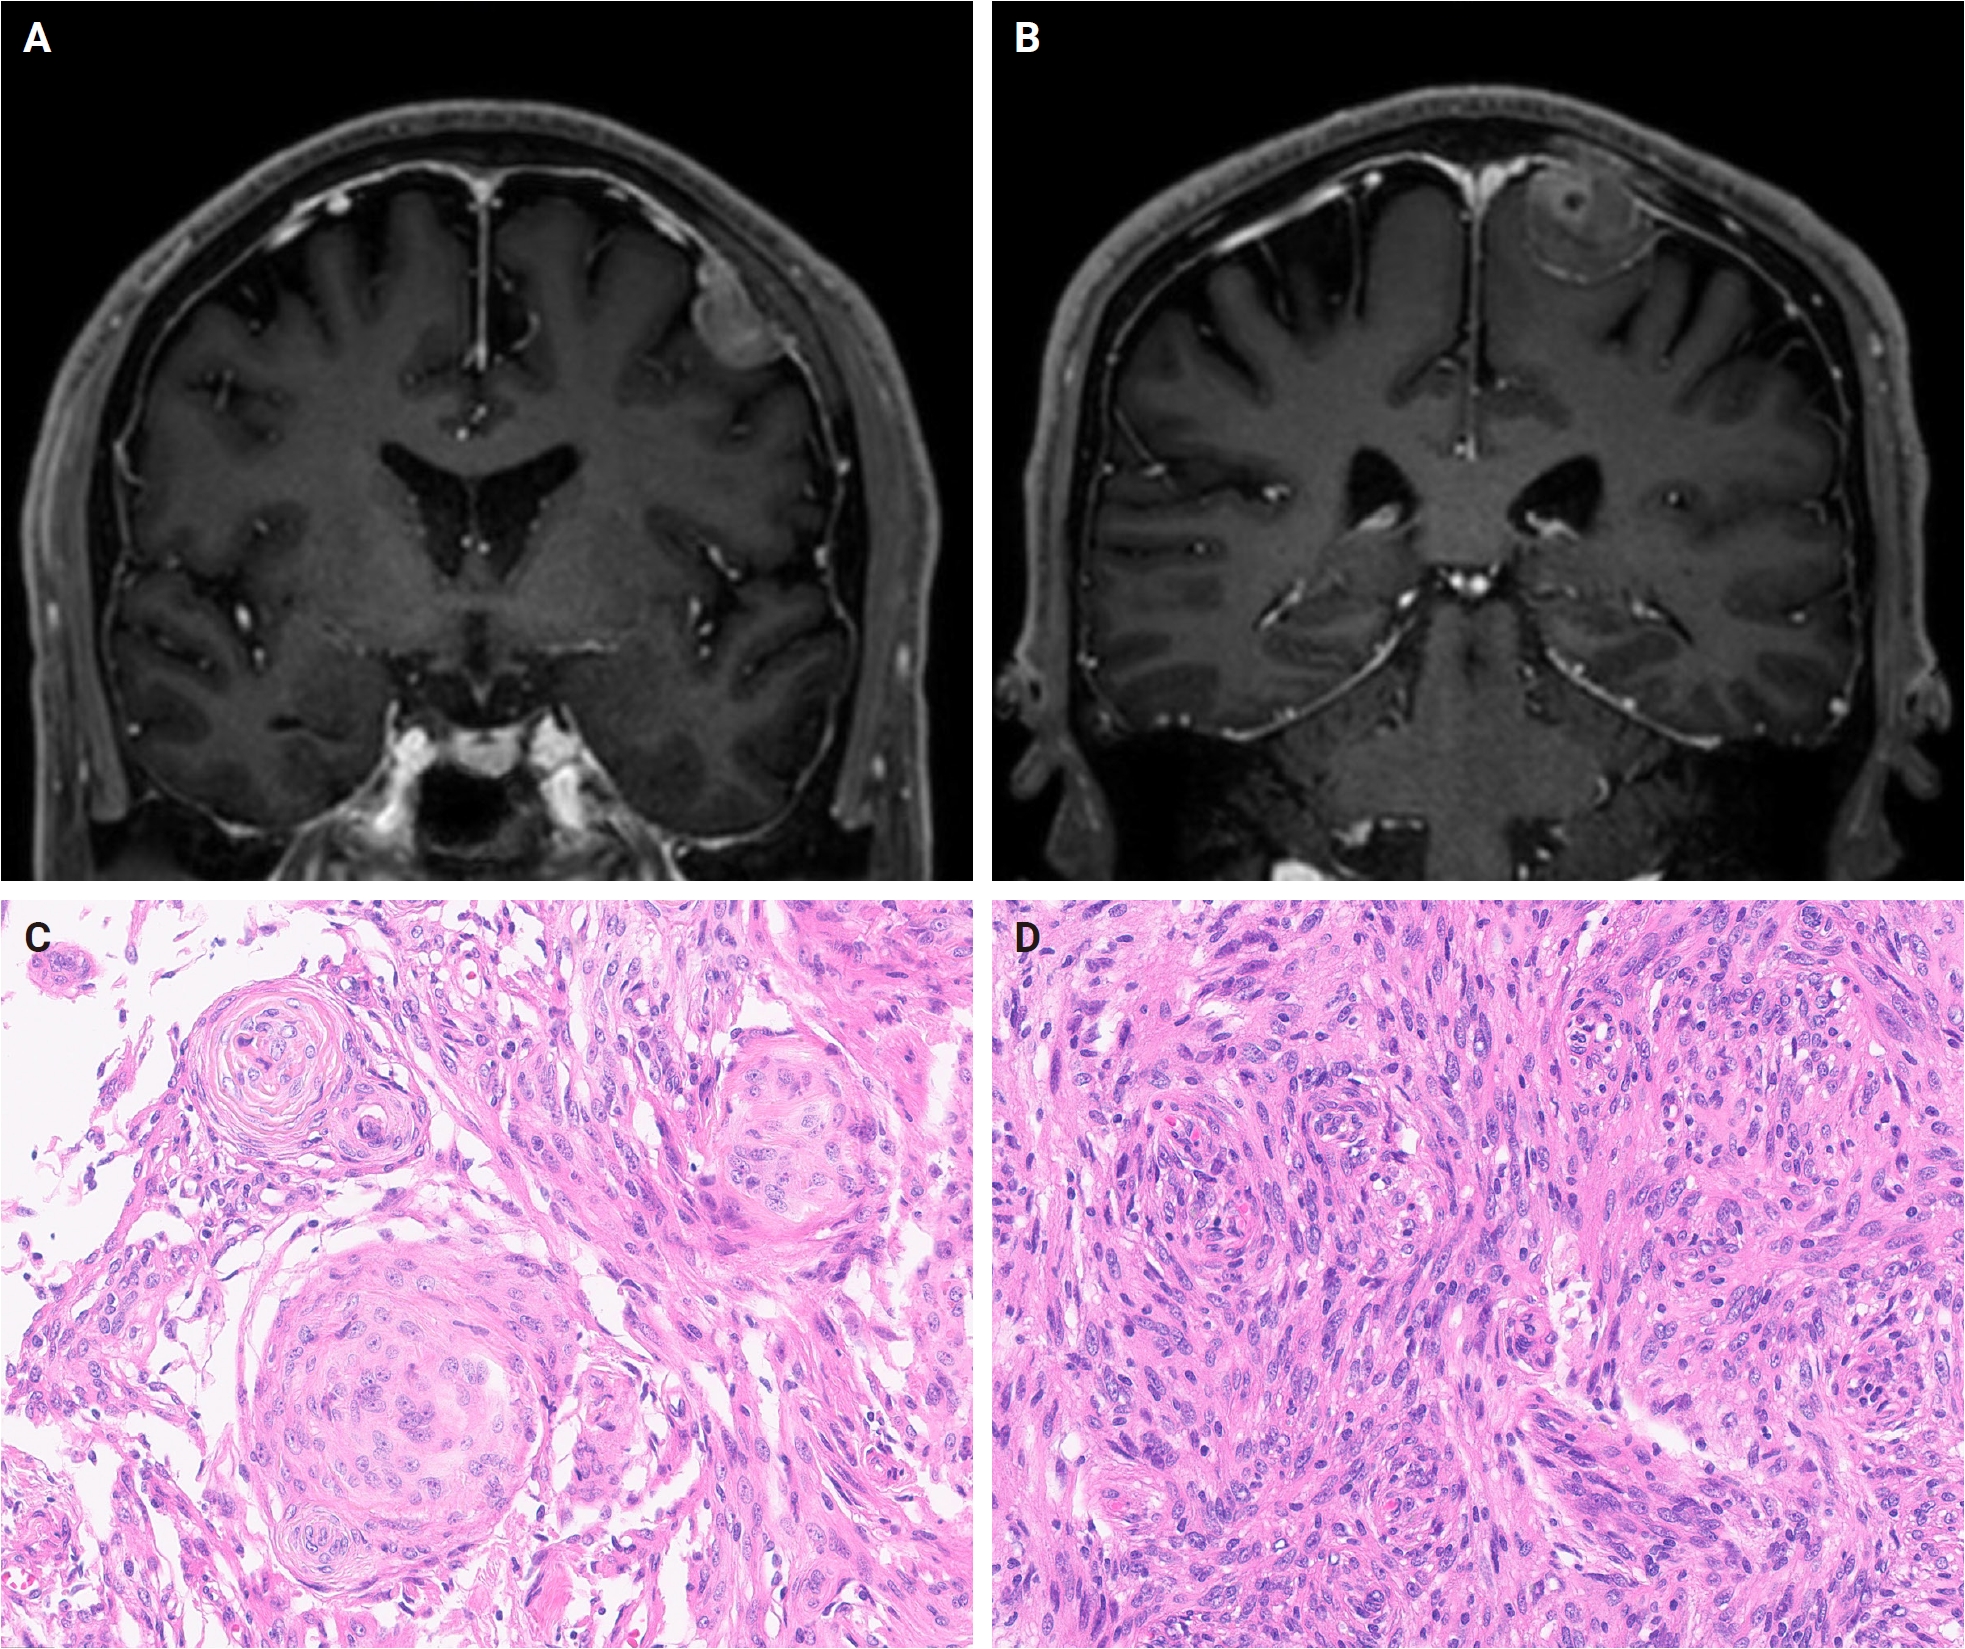
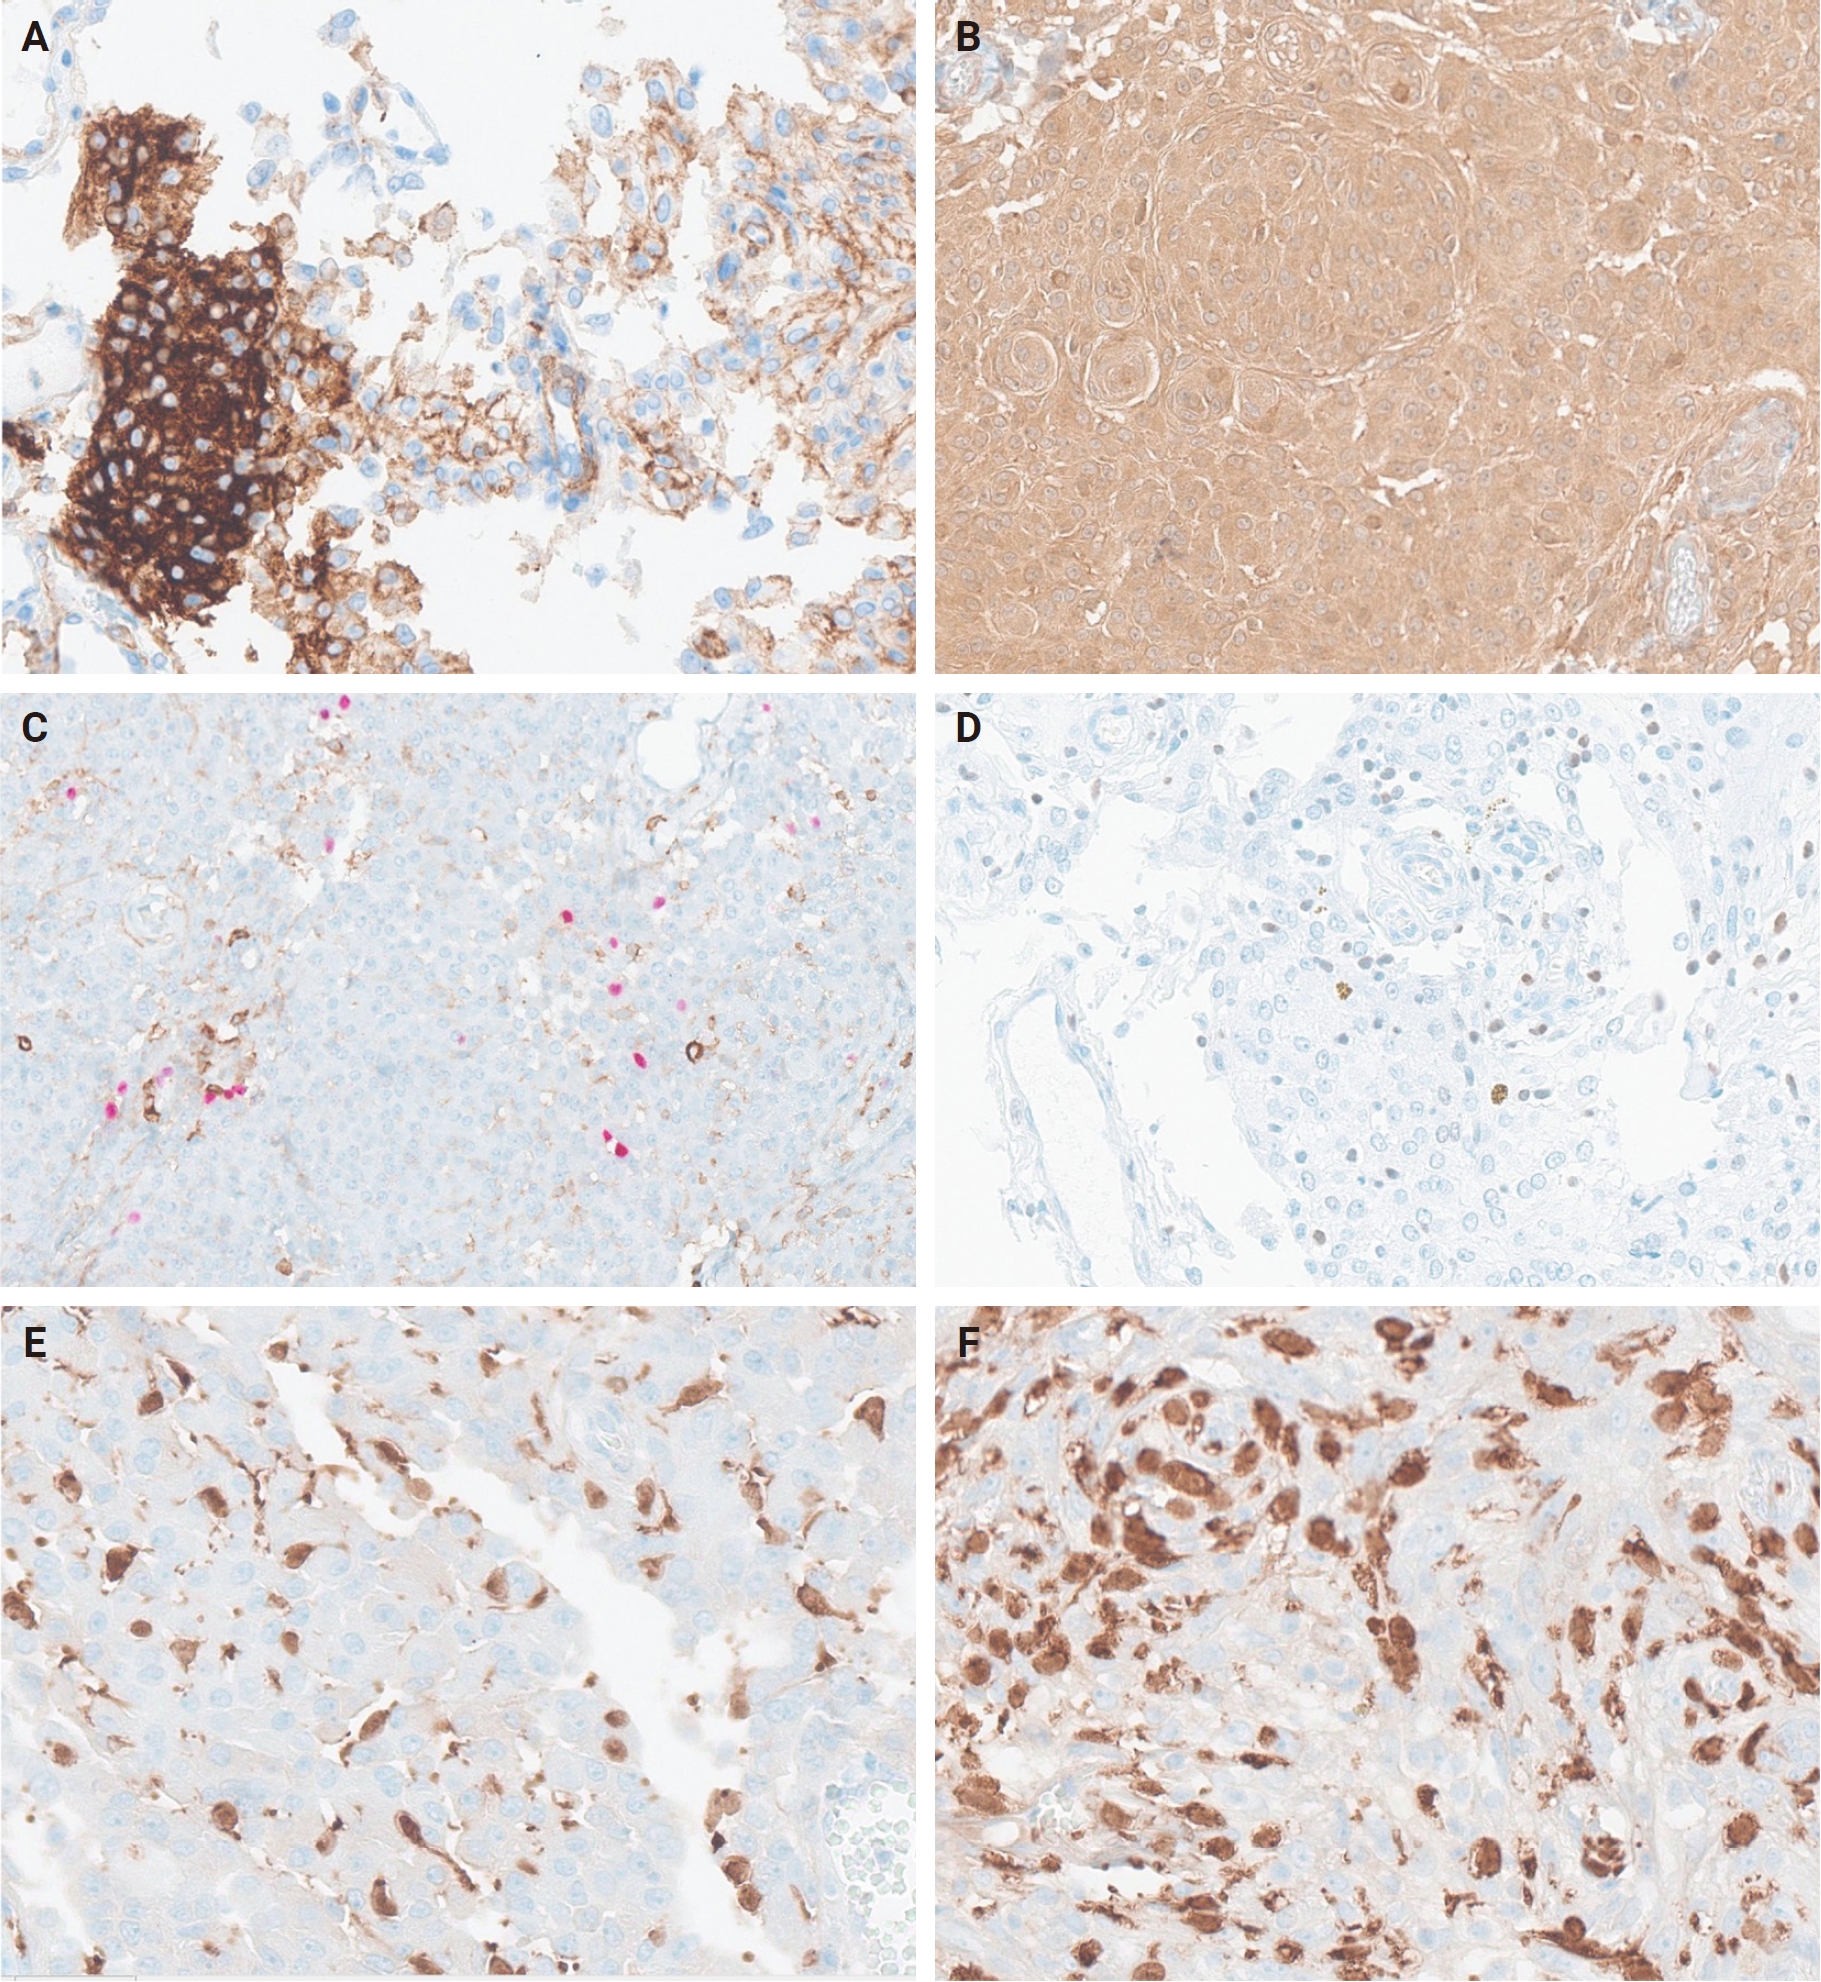
- A 69-year-old man presented with two intracranial masses identified on magnetic resonance imaging: a lateral convexity mass measuring 2.4 cm (Fig. 1A) and a medial convexity mass measuring 2.6 cm (Fig. 1B). He underwent craniotomy and tumor removal, and the following histopathologic findings were observed in the meningeal specimen. The lateral convexity mass exhibited syncytia-like lobules (Fig. 1C), while the medial convexity mass showed a similar pattern along with a spindle cell pattern (Fig. 1D). These findings were consistent with meningothelial meningioma and fibrous meningioma, respectively. By immunohistochemistry, both tumors showed concordant findings; representative images from the lateral convexity mass are shown (Fig. 2A–D). Both tumors were positive for somatostatin receptor 2-alpha (SSTR2A) (clone UMB1, ab134152, 1:400, Abcam, Cambridge, UK) (Fig. 2A) and methylthioadenosine phosphorylase (MTAP) (clone 2G4, H00004507-M01, 1:100, Abnova, Taipei, Taiwan) (Fig. 2B). The monoclonal antibody for SSTR2A is a highly sensitive and specific marker for meningioma [6]. Because homozygous deletion of CDKN2A and/or CDKN2B upgrades a meningioma to central nervous system World Health Organization (WHO) grade 3, we used MTAP immunohistochemistry as a surrogate marker for CDKN2A loss [7]. Double immunostaining for Ki-67 (clone MIB-1, M7240, 1:150, Dako, Glostrup, Denmark) and CD45 (clone 2B11+PD7/26, M0701, 1:200, Dako) was performed to distinguish proliferating tumor cells from infiltrating lymphocytes. The Ki-67 proliferation index was less than 2% (Fig. 2C), and phosphohistone H3 staining (rabbit polyclonal, 760-4591, RTU, Cell Marque, Rocklin, CA, USA) revealed only 1 per 10 high-power fields (HPFs) (Fig. 2D). Taken together, both masses were classified as WHO grade 1 meningioma.
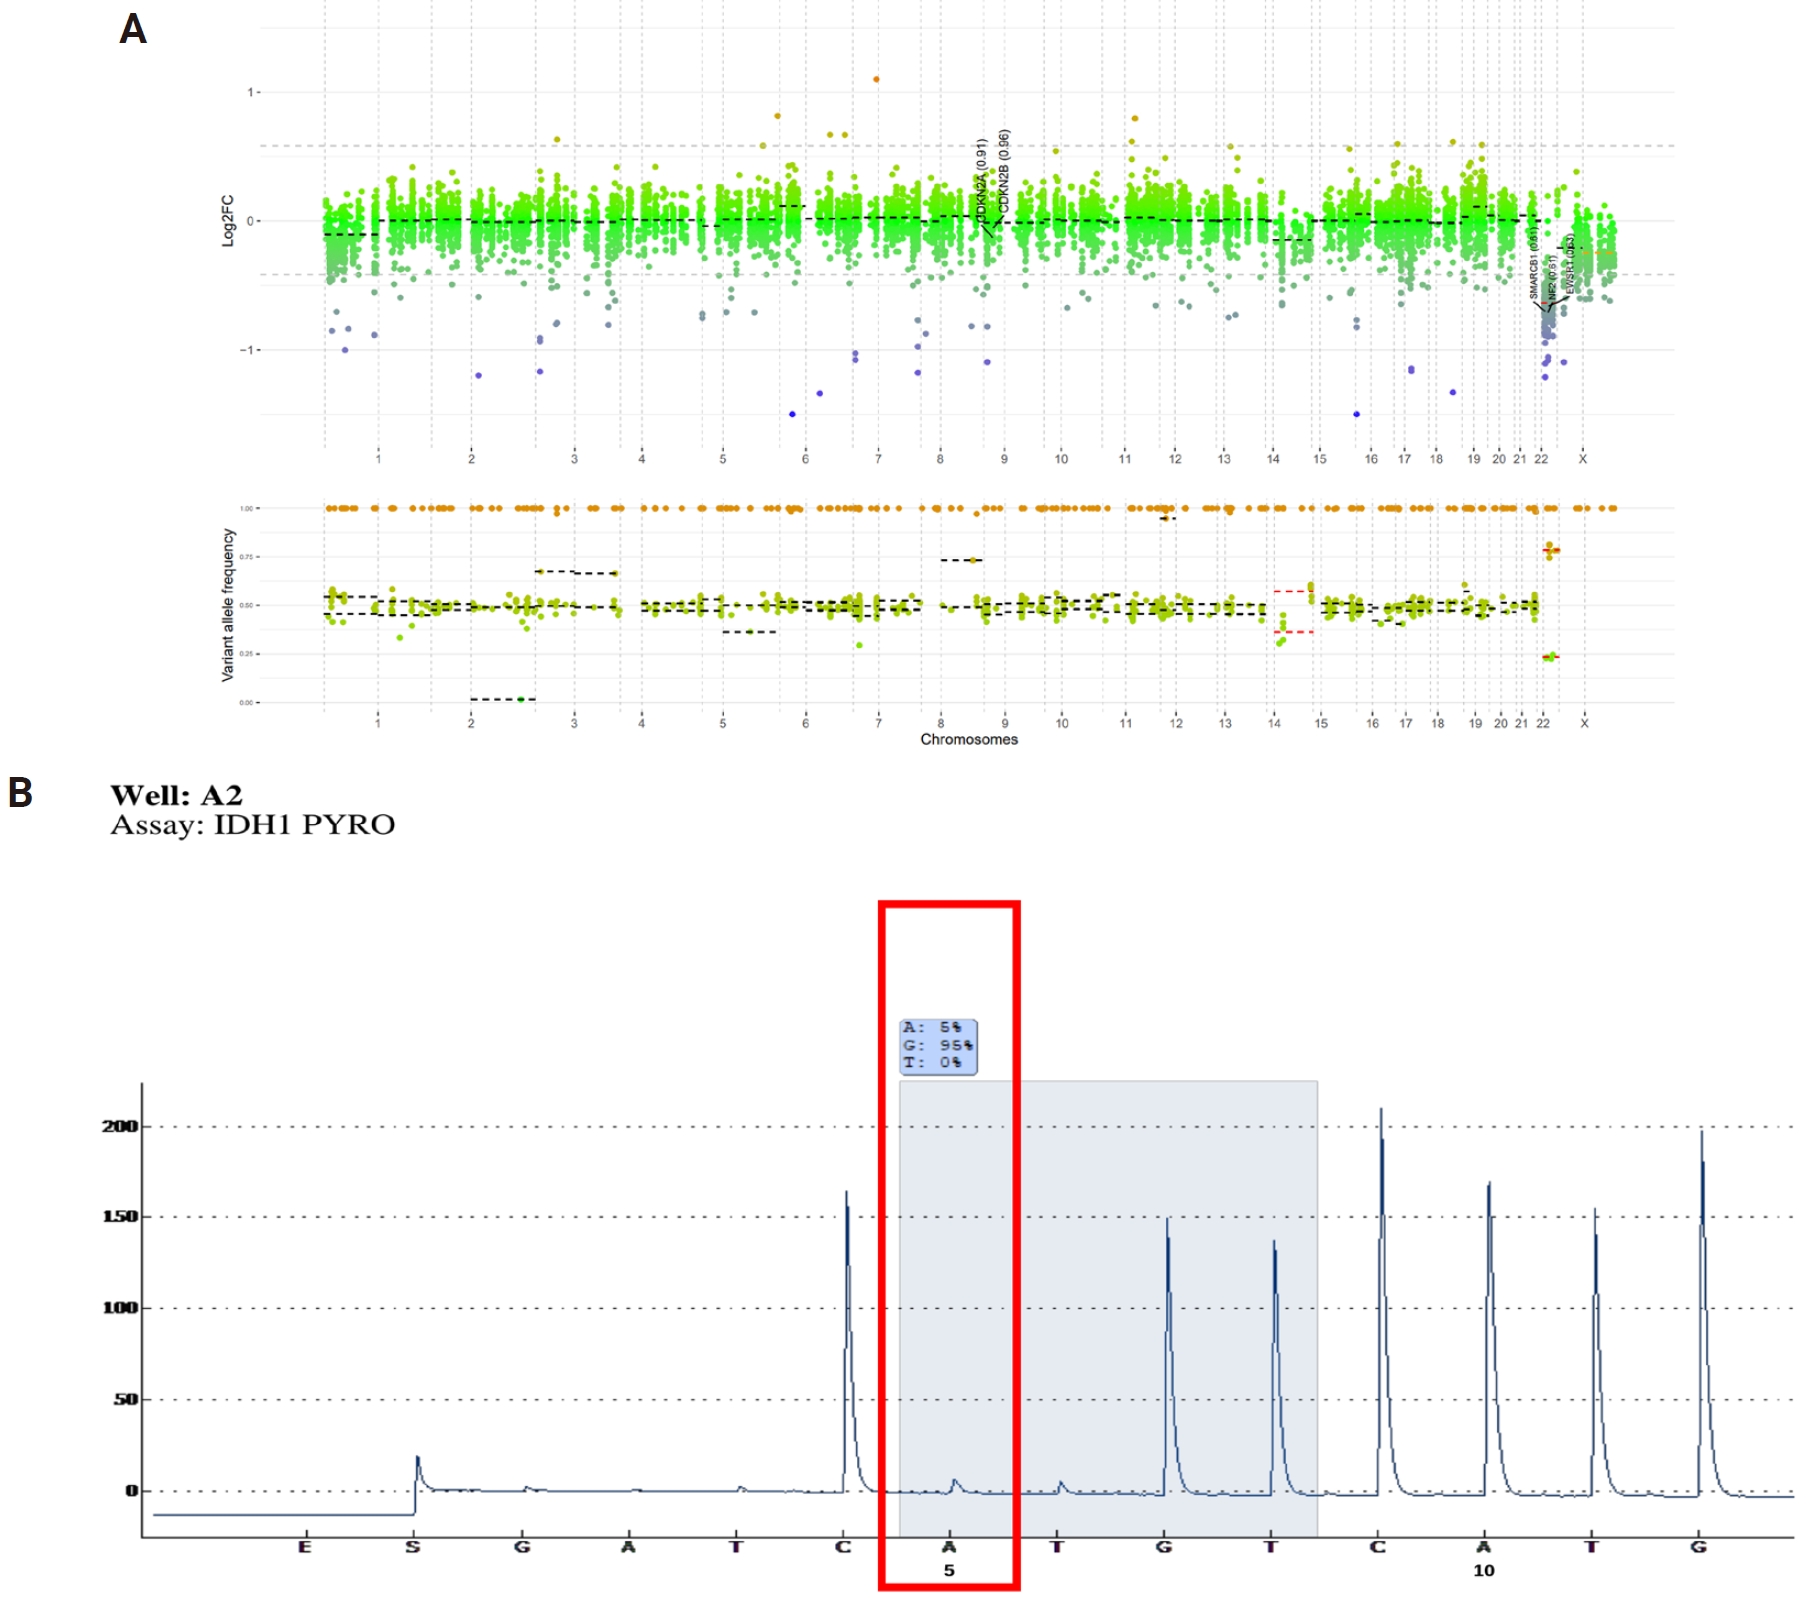
- DNA was extracted from formalin-fixed paraffin-embedded (FFPE) tumor tissue using the AllPrep DNA/RNA FFPE Kit (Qiagen, Hilden, Germany). Next-generation sequencing (NGS) was performed using the TruSight Oncology 500 panel (Illumina, San Diego, CA, USA) on a NovaSeq 6000Dx sequencer (Illumina). NGS library preparation was carried out using an automated system (Zephyr G3 NGS iQ Workstation, Revvity, Waltham, MA, USA). Sequencing data analysis, including detection of copy number variations and gene fusions, was performed using the DRAGEN TSO500 pipeline v2.6.2 (Illumina). NGS was performed on the lateral convexity mass. We identified an IDH1 p.R132H missense mutation (variant allele frequency [VAF], 1.5%; depth, 400×), an NF1 p.L1865* nonsense mutation, loss of chromosome 22q, and loss of NF2. The copy number plot showed focal deletion on chromosome 22q, and subtle deviations in VAF were observed in portions of chromosome 2, without clear corresponding copy number loss (Fig. 3A).
- To provide orthogonal validation for the IDH1 R132H missense mutation, we performed pyrosequencing. Pyrosequencing was conducted using the PyroMark PCR Kit and PyroMark Gold Q24 Reagents (Qiagen) on a PyroMark Q24 platform (Qiagen). Data analysis was performed using PyroMark Q24 software version 2.0.8 (Qiagen), with an analytical sensitivity (limit of detection) of 5%. The result identified an IDH1 mutation with a mutant allele frequency of approximately 5% (Fig. 3B).
- Furthermore, immunohistochemistry for IDH1 R132H (clone H09, DIA-H09, 1:80, Dianova, Hamburg, Germany) was positive in both masses, supporting the molecular findings (Fig. 2E, F). The staining was heterogeneous and patchy, with intermingled focal positive tumor cells.
- The patient is currently under regular follow-up in the outpatient clinic.
CASE REPORT
- A distinctive feature of this case was the low VAF (1.5%) of the IDH1 R132H mutation on NGS, which raised the question of whether it represented a genuine, biologically meaningful alteration or a sequencing artifact. To address this, we sought orthogonal validation at both the DNA and protein levels. Pyrosequencing, an independent DNA-based assay, confirmed the IDH1 mutation at a mutant allele frequency of approximately 5% (Fig. 3B), and immunohistochemistry demonstrated IDH1 R132H protein expression in both masses. The convergence of these independent methods makes a technical artifact highly unlikely and establishes the variant as a true, biologically expressed event.
- Across all three assays, however, the mutation-positive fraction was consistently minor. On immunohistochemistry, the staining was heterogeneous and patchy, with intermingled positive and negative tumor cells rather than the diffuse, uniform cytoplasmic positivity characteristic of isocitrate dehydrogenase (IDH)-mutant gliomas. Assuming a heterozygous, diploid state, a VAF of approximately 1.5% corresponds to the mutation being present in only a small subset of tumor cells (on the order of a few percent), paralleling the limited proportion of immunopositive cells. Although the pyrosequencing estimate (~5%) was modestly higher than the NGS VAF, both DNA-based assays concordantly indicated a low mutant fraction. Because meningiomas are generally cellular tumors with high tumor purity, this low mutant fraction is unlikely to be attributable to tumor cell dilution and instead favors a genuinely subclonal IDH1 R132H alteration confined to a minor tumor cell population. The biological and clinical significance of this subclonal IDH1 R132H alteration in meningioma, however, remains to be determined. Although technical factors such as fixation variability and staining-intensity thresholds may contribute to the apparent heterogeneity, the concordance across NGS, pyrosequencing, and immunohistochemistry supports true biological (subclonal) heterogeneity as the most likely explanation.
- IDH1 mutations are well-established molecular hallmarks of diffuse gliomas, where their prevalence has been extensively characterized. However, their occurrence in meningiomas is exceedingly rare. A prior large-scale study investigating the prevalence of IDH1/2 mutations across tumors [8] did not identify such alterations in meningiomas, highlighting the rarity of this molecular finding. Among 541 patients with meningioma who had available NGS data at our institution between 2017 and May 2026, only the present case harbored an IDH1 R132H mutation, reflecting the rarity of this alteration in meningioma.
- Nevertheless, sporadic cases of IDH1/2-mutant meningioma have been reported in the literature [9] (Table 1). In these previously described cases, patients demonstrated survival exceeding 10 years, suggesting a potentially favorable prognosis associated with this mutation. However, given the limited number of reported cases, a robust survival analysis and definitive prognostic conclusions remain premature.
- IDH inhibitors, such as vorasidenib, have been successfully incorporated into the treatment landscape for IDH-mutant gliomas [10] and may represent a rational therapeutic strategy for IDH-mutant meningiomas. Whether this therapeutic strategy can be extrapolated to IDH1/2-mutant meningiomas remains an open question, and further investigations—including prospective studies and larger case series—are warranted to evaluate the clinical utility of IDH-targeted therapy in this rare molecular subset of meningioma.
- In summary, we report an exceedingly rare case of IDH1 R132H-mutant meningioma, confirmed by NGS, pyrosequencing, and immunohistochemistry.
DISCUSSION
Ethics Statement
All procedures performed in the current study were approved by Institutional Review Board (IRB) (IRB approval no. 4-2026-0506; approved on June 8, 2026) in accordance with the 1964 Helsinki Declaration and its later amendments. Informed consent for publication of this case was obtained from the patient and his legal guardian.
Availability of Data and Material
The datasets generated or analyzed during the study are available from the corresponding author on reasonable request.
Code Availability
Not applicable.
Author Contributions
Conceptualization: SHK. Data curation: CL. Formal analysis: SA, SHK. Investigation: SA, CL, SHK. Methodology: CL, SHK. Project administration: JPP, SHK. Resources: CL, SHK. Software: CL. Supervision: SHK. Validation: CL, SHK. Visualization: SA, CL, SHK. Writing—original draft: SA, SHK. Writing—review & editing: SA, CL, JPP, SHK. Approval of final manuscript: all authors.
Conflicts of Interest
Se Hoon Kim, a contributing editor of the Journal of Pathology and Translational Medicine, was not involved in the editorial evaluation or decision to publish this article. All remaining authors have declared no conflicts of interest.
Funding Statement
No funding to declare.
| Case No. | Age (yr)/Sex | Radiology (location) | Grade | Mutation | Follow-up/survival (yr) |
|---|---|---|---|---|---|
| 1 | 53/F | CT: heterogeneously enhancing, partially calcified extra-axial right frontal mass (4.1 × 3.6 × 4.1 cm) | Grade II; focal brain invasion | IDH1 p.R132H (VAF, 10.5%; depth, 334×); IDH1 R132H IHC (−)a | 10.1 |
| 2 | 37/F | MRI: left frontal mass (5.4 × 7.5 × 6.9 cm) | Recurrent grade III (papillary); focal brain invasion | IDH1 p.R132G (VAF, 6.9%; depth, 2,000×); NF2 p.Ile126fs | 13.3 |
| 3 | 67/F | Parietal convexity | Recurrent grade II; focal necrosis | IDH2 p.R140Q (VAF, 5.0%; depth, 2,000×) | 10.9 |
| Present | 69/M | MRI: medial (2.6 cm) and lateral (2.4 cm) convexity masses | Grade 1 | IDH1 p.R132H (VAF, 1.5%; depth, 400×); IDH1 R132H IHC (+) | NAb |
IDH, isocitrate dehydrogenase; F, female; CT, computed tomography; VAF, variant allele frequency; IHC, immunohistochemistry; MRI, magnetic resonance imaging; NF2, neurofibromin 2; M, male; NA, not available.
aAlthough molecular testing detected the IDH1 p.R132H variant, immunohistochemistry for IDH1 R132H was negative;
bSurvival data were not available for the present case at the time of reporting.
- 1. Ostrom QT, Cioffi G, Gittleman H, et al. CBTRUS statistical report: primary brain and other central nervous system tumors diagnosed in the United States in 2012-2016. Neuro Oncol 2019; 21(Suppl 5): v1-100. ArticlePubMedPMCPDF
- 2. Choy W, Kim W, Nagasawa D, et al. The molecular genetics and tumor pathogenesis of meningiomas and the future directions of meningioma treatments. Neurosurg Focus 2011; 30: E6.Article
- 3. Clark VE, Erson-Omay EZ, Serin A, et al. Genomic analysis of non-NF2 meningiomas reveals mutations in TRAF7, KLF4, AKT1, and SMO. Science 2013; 339: 1077-80. ArticlePubMedPMC
- 4. El-Habr EA, Levidou G, Trigka EA, et al. Complex interactions between the components of the PI3K/AKT/mTOR pathway, and with components of MAPK, JAK/STAT and Notch-1 pathways, indicate their involvement in meningioma development. Virchows Arch 2014; 465: 473-85. ArticlePubMedPDF
- 5. Sahm F, Aldape KD, Brastianos PK, et al. cIMPACT-NOW update 8: clarifications on molecular risk parameters and recommendations for WHO grading of meningiomas. Neuro Oncol 2025; 27: 319-30. ArticlePubMedPMCPDF
- 6. Menke JR, Raleigh DR, Gown AM, Thomas S, Perry A, Tihan T. Somatostatin receptor 2a is a more sensitive diagnostic marker of meningioma than epithelial membrane antigen. Acta Neuropathol 2015; 130: 441-3. ArticlePubMedPDF
- 7. Dono A, Pichardo-Rojas D, Mendoza Mora L, et al. MTAP immunohistochemistry as a surrogate marker of CDKN2A loss in brain tumors: a meta-analysis and literature review. J Neuropathol Exp Neurol 2025; 84: 600-10. ArticlePubMedPMCPDF
- 8. Murugan AK, Alzahrani AS. Isocitrate dehydrogenase IDH1 and IDH2 mutations in human cancer: prognostic implications for gliomas. Br J Biomed Sci 2022; 79: 10208.ArticlePubMedPMC
- 9. Gill CM, Loewenstern J, Rutland JW, et al. Recurrent IDH mutations in high-grade meningioma. Neuro Oncol 2020; 22: 1044-5. ArticlePubMedPMCPDF
- 10. Mellinghoff IK, van den Bent MJ, Blumenthal DT, et al. Vorasidenib in IDH1- or IDH2-mutant low-grade glioma. N Engl J Med 2023; 389: 589-601. ArticlePubMedPMC
REFERENCES
Figure & Data
References
Citations

 PubReader
 ePub Link
-
 Cite this Article
- Cite this Article
-
- Close
- Download Citation
- Close
 XML Download
- Figure
-
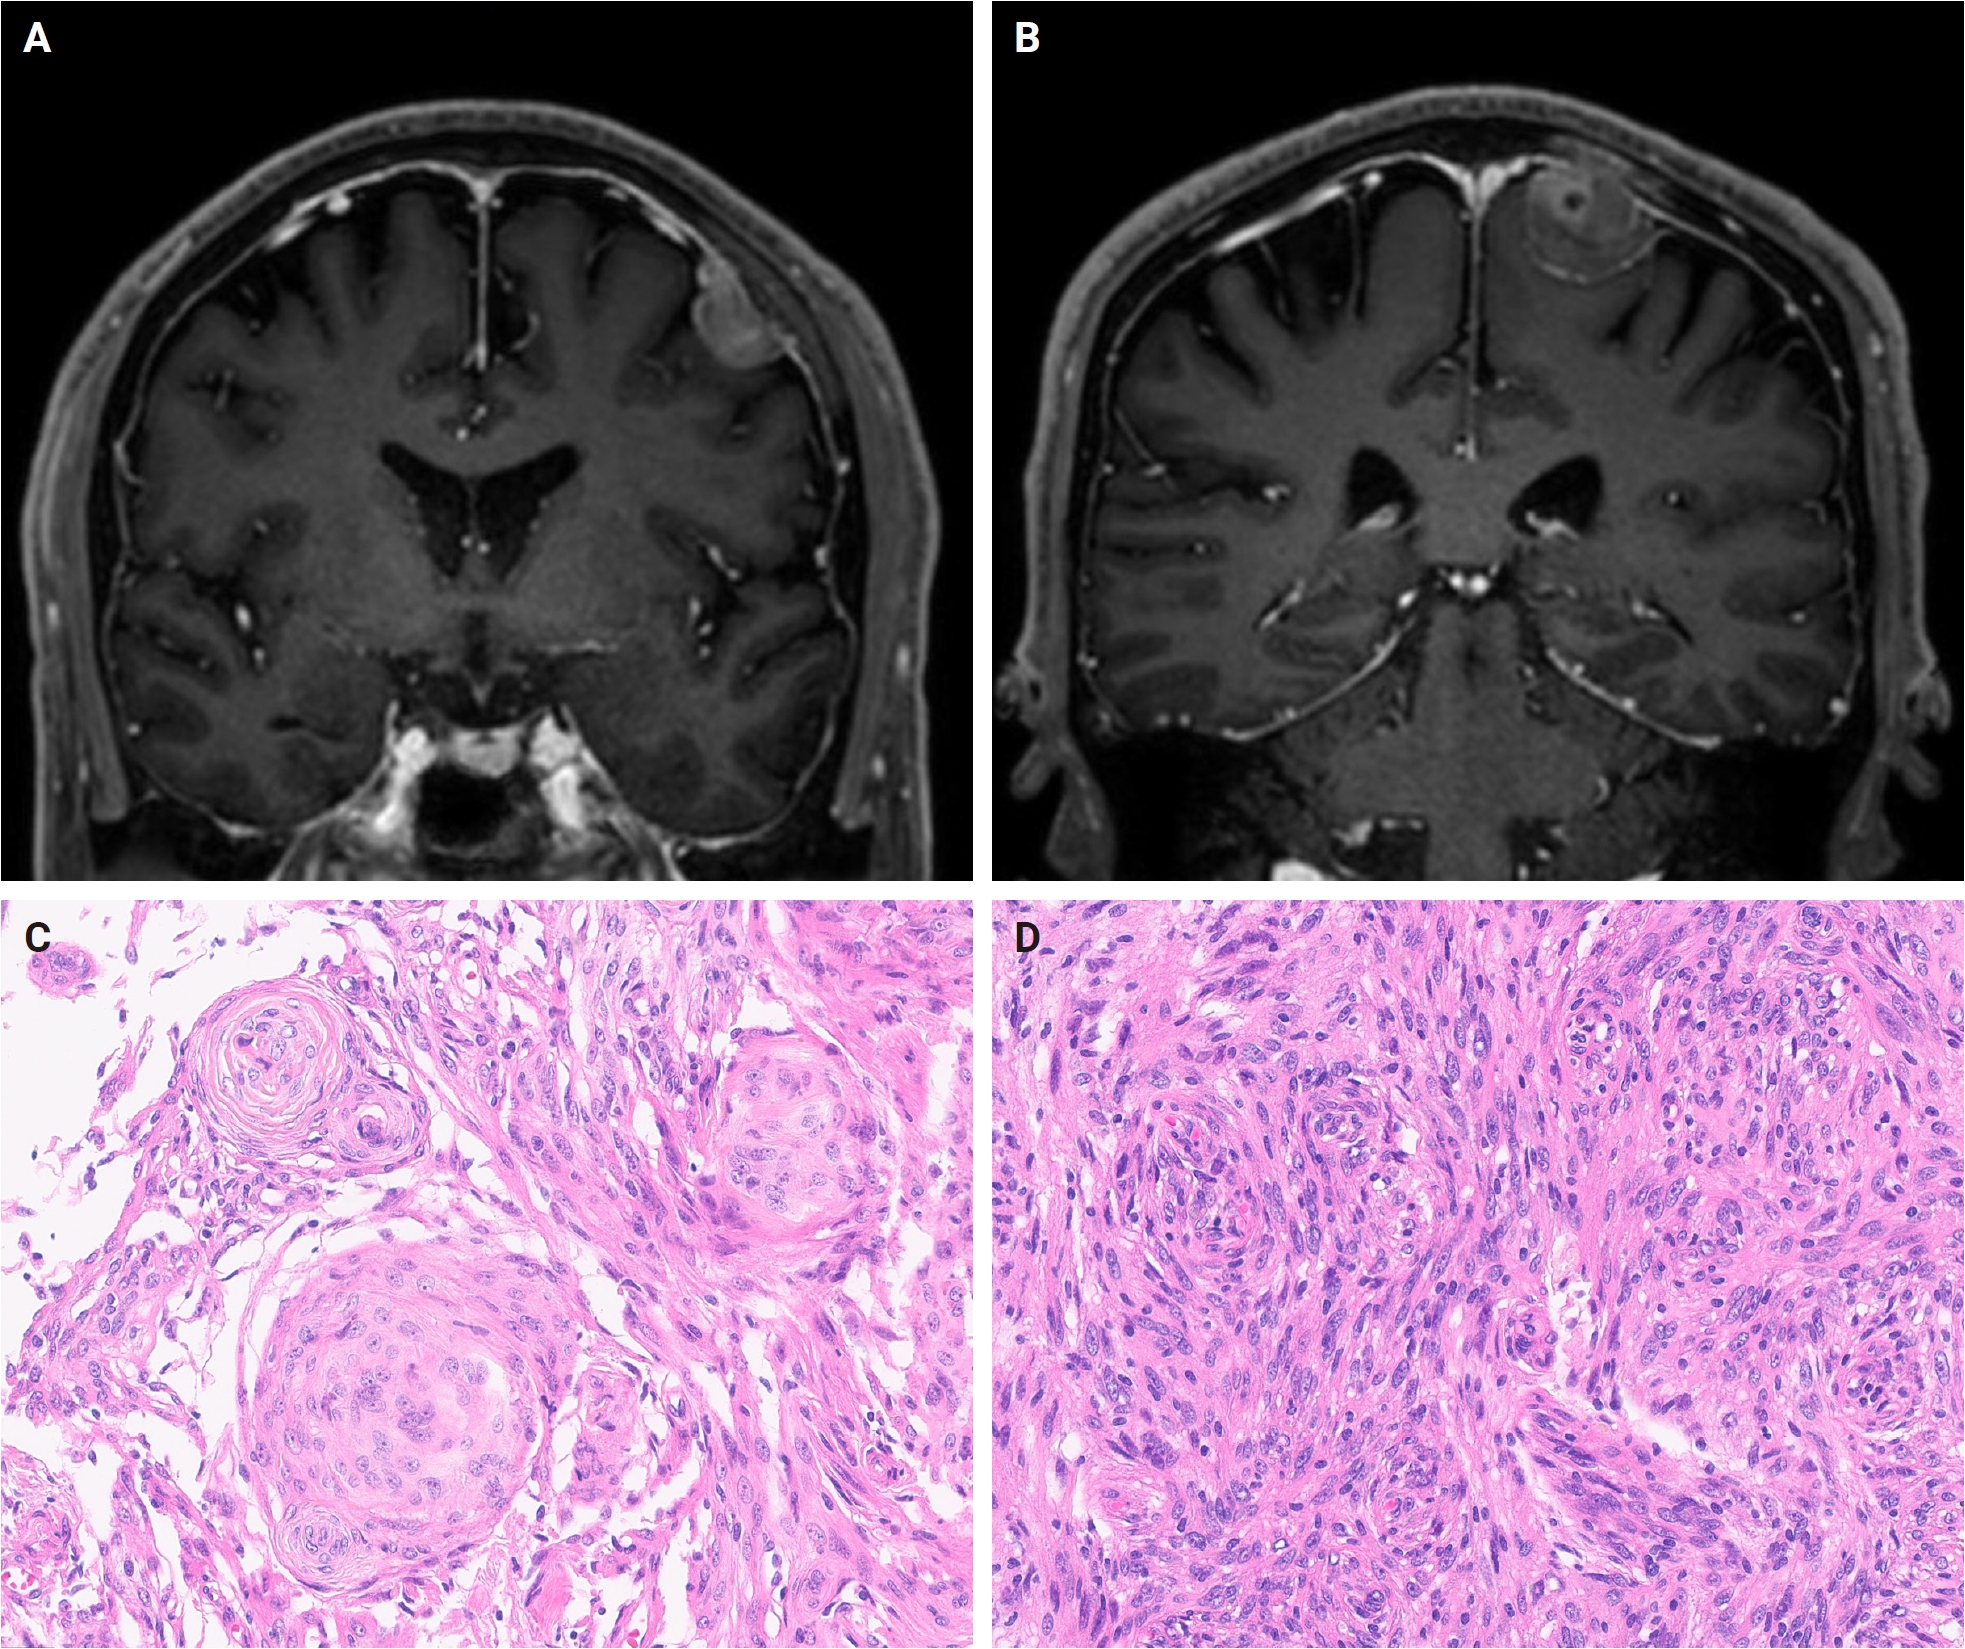
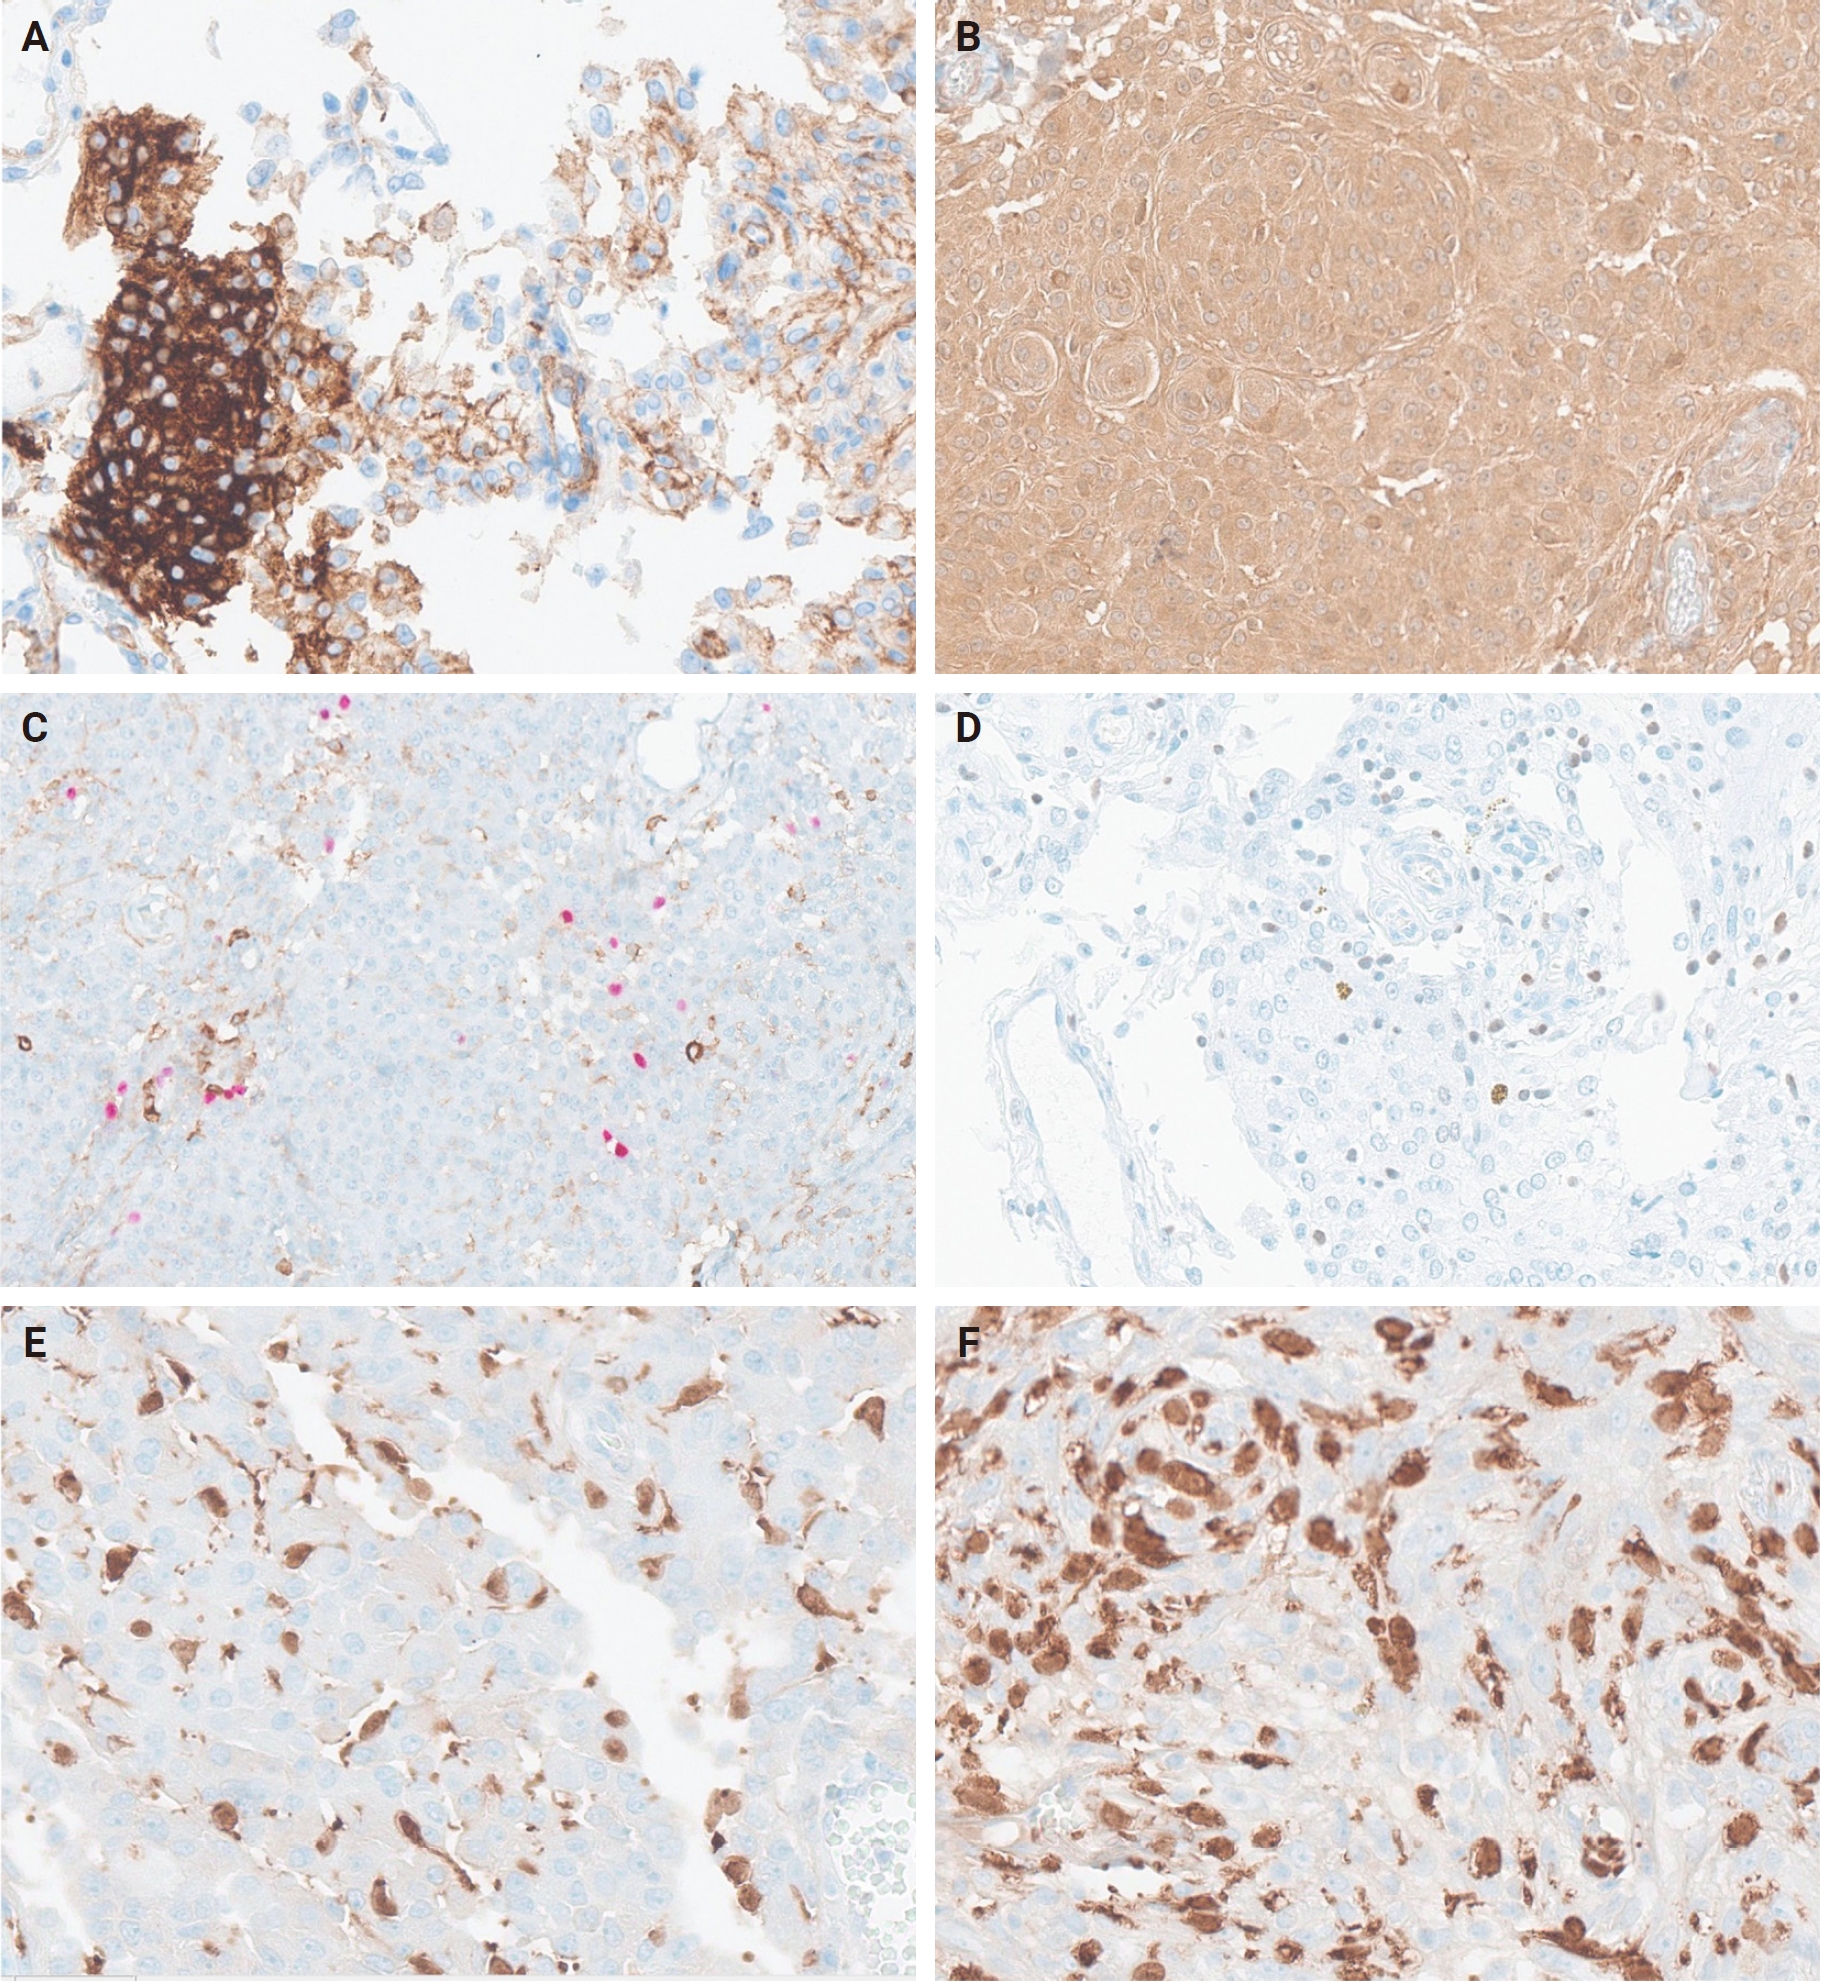
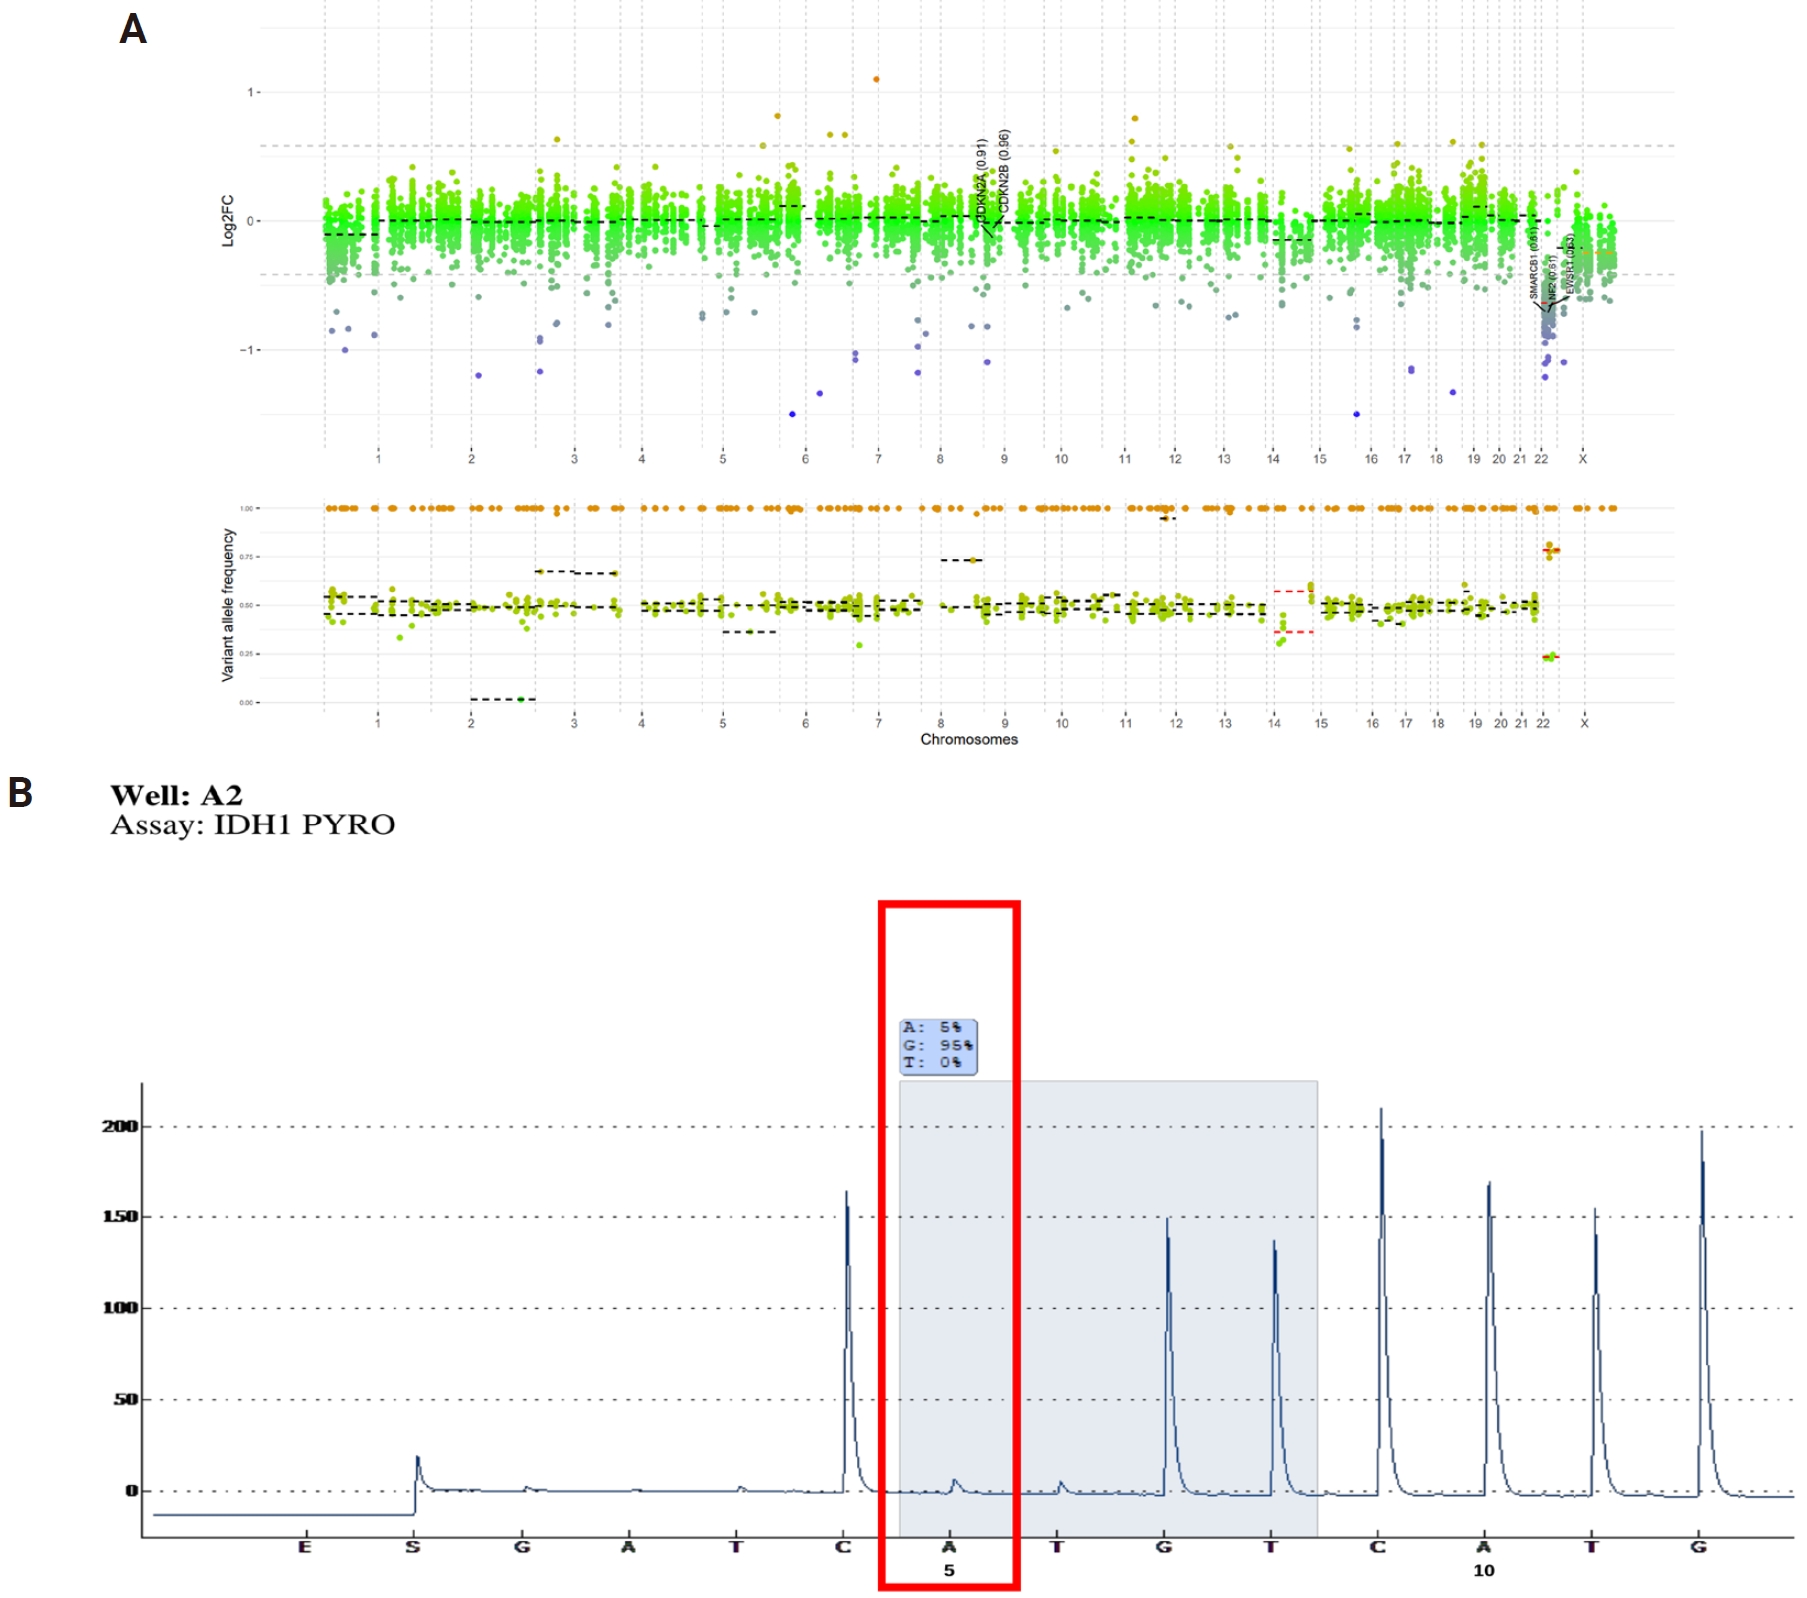



Fig. 1.
Fig. 2.
Fig. 3.
| Case No. | Age (yr)/Sex | Radiology (location) | Grade | Mutation | Follow-up/survival (yr) |
|---|---|---|---|---|---|
| 1 | 53/F | CT: heterogeneously enhancing, partially calcified extra-axial right frontal mass (4.1 × 3.6 × 4.1 cm) | Grade II; focal brain invasion | IDH1 p.R132H (VAF, 10.5%; depth, 334×); IDH1 R132H IHC (−) |
10.1 |
| 2 | 37/F | MRI: left frontal mass (5.4 × 7.5 × 6.9 cm) | Recurrent grade III (papillary); focal brain invasion | IDH1 p.R132G (VAF, 6.9%; depth, 2,000×); NF2 p.Ile126fs | 13.3 |
| 3 | 67/F | Parietal convexity | Recurrent grade II; focal necrosis | IDH2 p.R140Q (VAF, 5.0%; depth, 2,000×) | 10.9 |
| Present | 69/M | MRI: medial (2.6 cm) and lateral (2.4 cm) convexity masses | Grade 1 | IDH1 p.R132H (VAF, 1.5%; depth, 400×); IDH1 R132H IHC (+) | NA |
IDH, isocitrate dehydrogenase; F, female; CT, computed tomography; VAF, variant allele frequency; IHC, immunohistochemistry; MRI, magnetic resonance imaging; Although molecular testing detected the Survival data were not available for the present case at the time of reporting.


